









Dental implants and bone surgery: who they are for, and the pathway
In periodontics, keeping the teeth comes first. When a tooth can no longer be saved, an implant is one way of replacing it, on three conditions: enough bone, healthy gums and periodontal disease that is under control. This page explains when an implant is indicated, how the pathway unfolds at Dr Hazout’s practice in Levallois-Perret, what can make it fail, and why the health of the gums decides how long it lasts.
Contents9 sections
- Why is a tooth lost, and when does an implant become indicated?
- Replacing a tooth: what an implant really is
- What becomes of a tooth that is not replaced?
- Three requirements before placing an implant
- The pathway, step by step
- For anxious patients: conscious sedation with nitrous oxide (MEOPA)
- Which page should you read?
- Limitations, relative contraindications and possible failures
- Lifespan and follow-up: the gums decide
Pages in this section
Placing an implant: the steps, and what guided surgery brings
An implant is placed long before the day of surgery. 3D imaging decides where it should go; the surgical guide carries that decision into the mouth. This page follows…
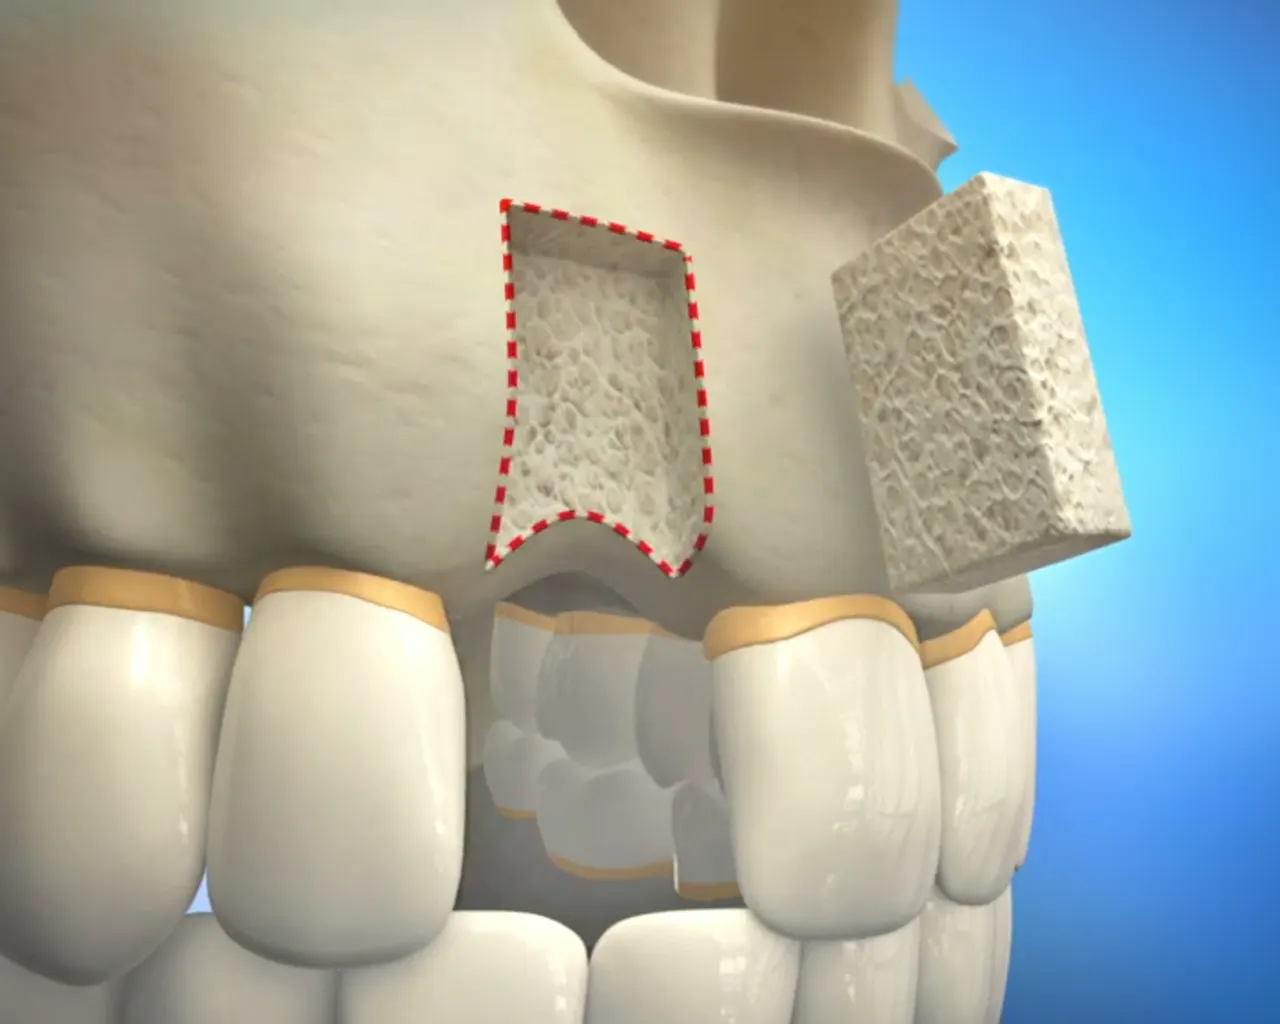
Bone grafting before an implant: when it is needed, and which techniques
An implant only holds in bone, along its whole length. When that bone is missing, it can be rebuilt, and several techniques achieve this, each suited to a particular…
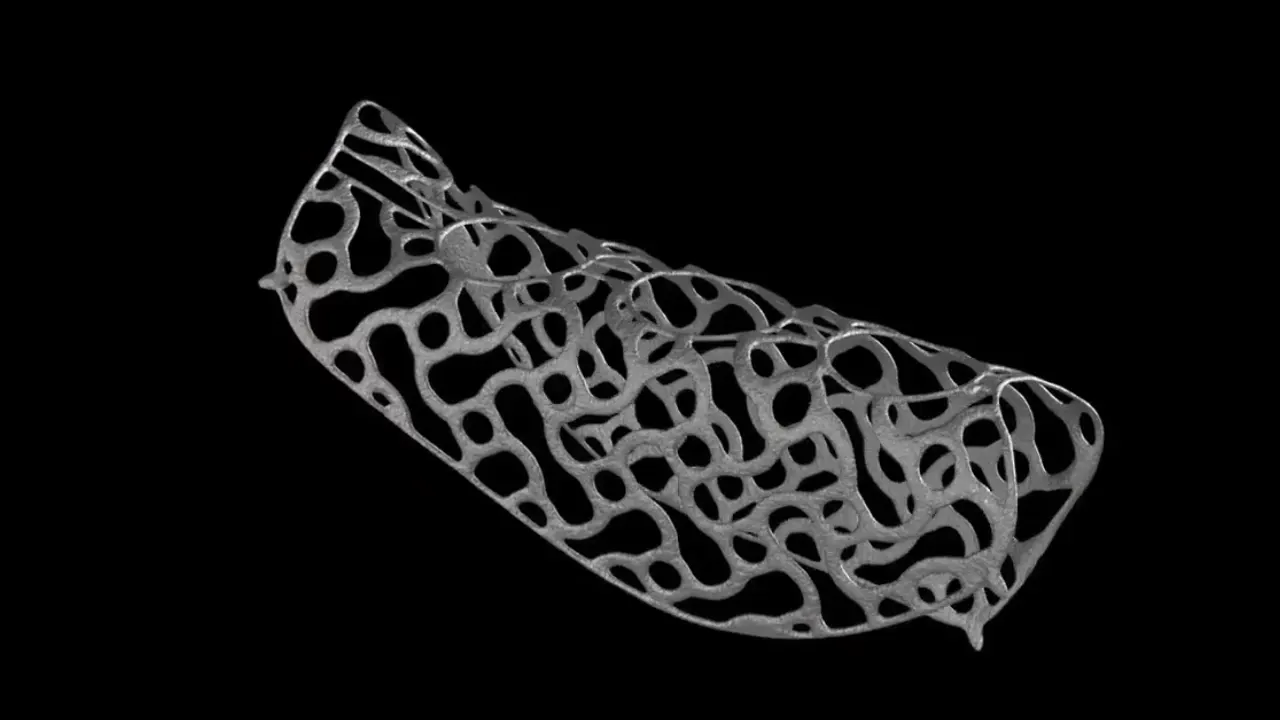
Custom titanium mesh: what it is for, and the principle of treatment
When bone is missing in height as well as width, the graft material needs to be held in shape while it heals. A custom titanium mesh does this job, like formwork: drawn…
Why is a tooth lost, and when does an implant become indicated?
In adults, the causes of tooth loss can be counted on one hand. Periodontitis, a chronic infection of the tissues that hold the tooth, gradually erodes bone and ligament: the tooth loosens, becomes mobile and eventually cannot be kept. A root fracture, deep decay that has taken too much of the tooth, a failed root canal treatment or trauma also lead to extraction. More rarely, a tooth has been missing since birth.
Extraction is never a light decision. A tooth with weakened support can often be treated, stabilised and kept for years: periodontitis treatment, periodontal regeneration or splinting are considered before an implant is even mentioned. An implant becomes an indication when the tooth is already missing, or when its prognosis is too poor to justify keeping it, and a replacement is wanted for chewing, for appearance or for the stability of the neighbouring teeth.
Replacing a tooth: what an implant really is
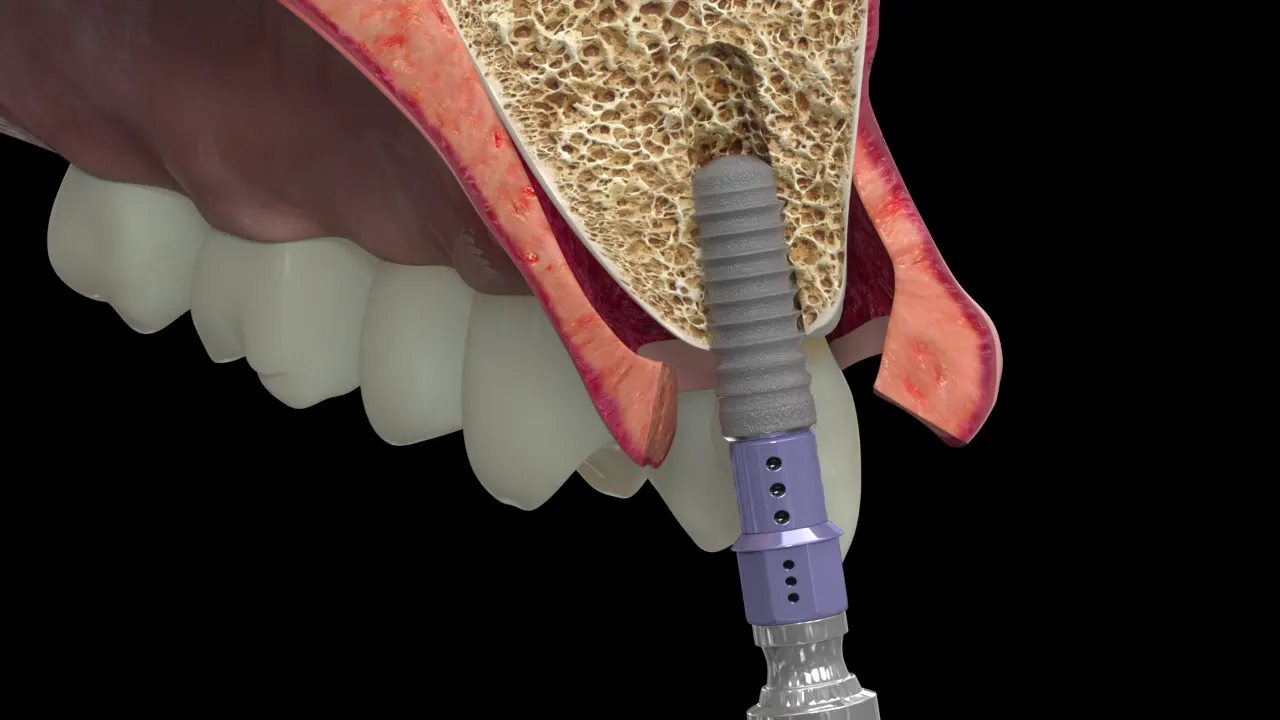
A dental implant is an artificial root, usually made of titanium, inserted into the jawbone. During healing, the bone fuses to its surface: this is osseointegration. The implant can then support a crown or a bridge, or hold a removable denture firmly in place.
An implant is not the only answer. A bridge bonded or cemented to the neighbouring teeth, a removable denture, or sometimes leaving the gap, are also discussed. The choice depends on the condition of the adjacent teeth, the amount of bone, your general health and what you expect.
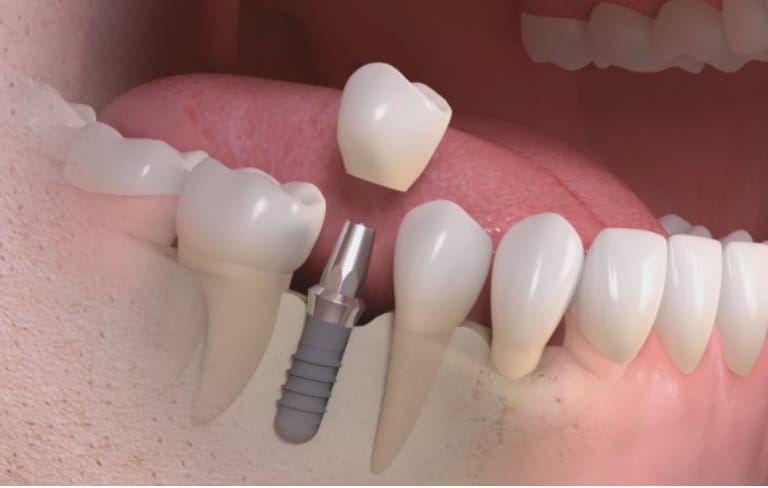
What becomes of a tooth that is not replaced?
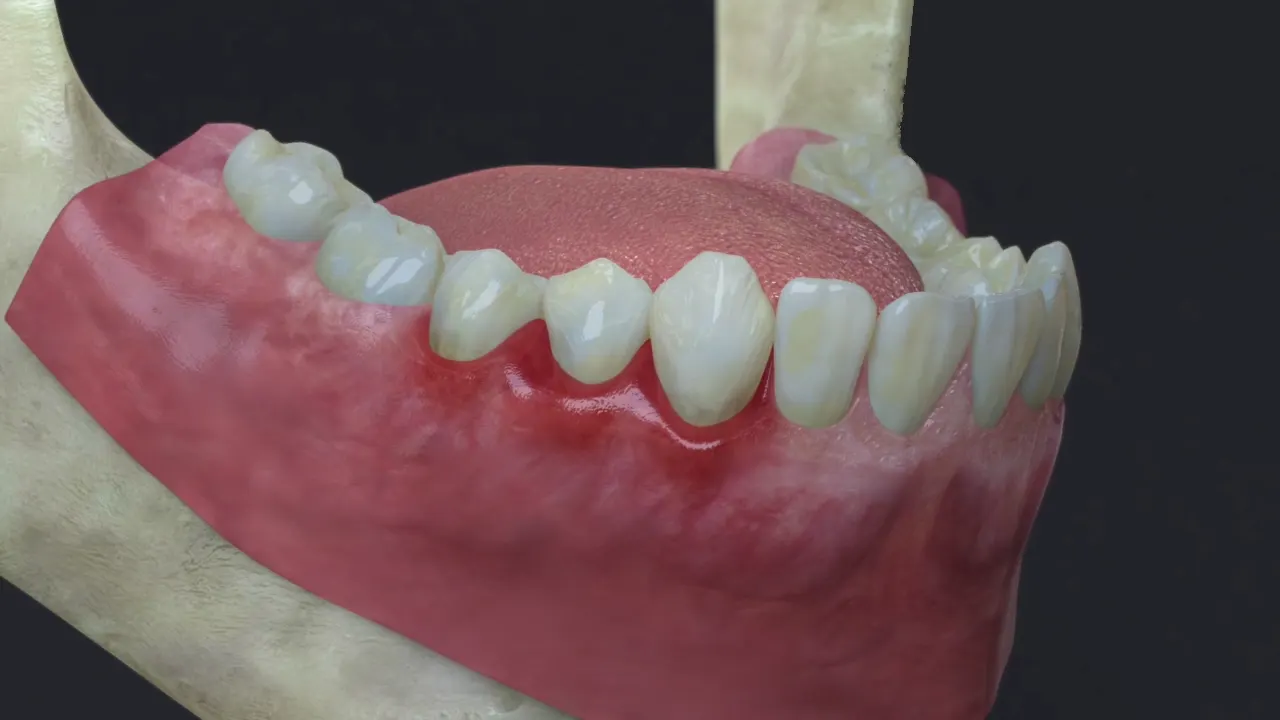
After an extraction, the bone that once held the root resorbs. A systematic review of human studies reports, six months after extraction, an average loss of about 3.8 mm in width and 1.2 mm in height, most of it happening in the first three to six months [1].
The opposing tooth may also drift into the gap, a movement called supra-eruption. In a retrospective study of 65 patients, it was measured in 78% of them, averaging 0.9 mm over about seven months [2]. These movements are usually modest, but they can complicate the future restoration. They are no reason to rush; they are every reason to plan.
Three requirements before placing an implant
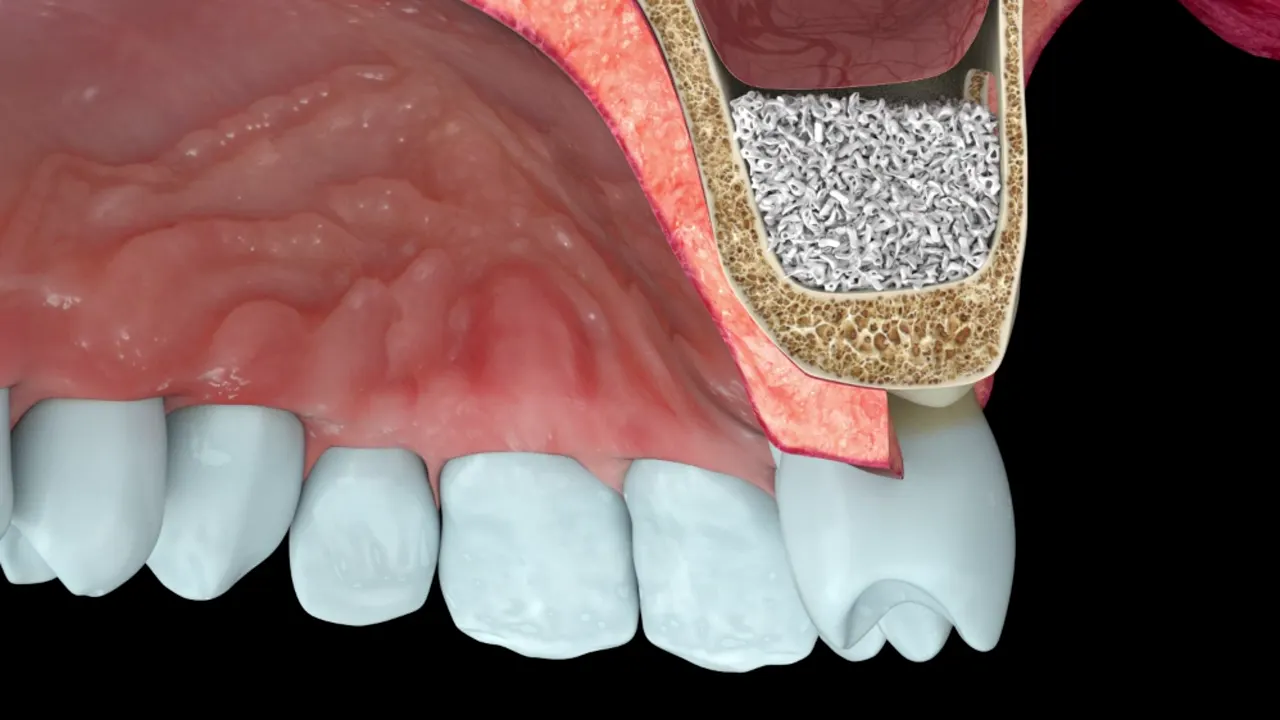
- Enough bone in height and in width, measured in three dimensions with a cone beam CT (a dental scanner using a cone-shaped X-ray beam). If bone is lacking, a bone graft may be offered before placement or at the same time.
- Healthy gums around the future implant and the neighbouring teeth, with daily cleaning that you can realistically manage.
- Stable periodontal tissues. The periodontium brings together the tissues that hold the tooth: gum, bone and ligament. Active periodontitis must be treated before an implant is placed.
This last point is the very heart of a periodontist’s approach. A 2024 meta-analysis shows that patients with a history of periodontitis, even when treated, have more peri-implantitis (inflammation with bone loss around the implant) and slightly lower implant survival than those who have never had it [3]. These are observational studies: they establish an association, not an inevitability. The authors conclude that an implant remains possible as long as the disease is controlled and stable.
The European (EFP) guideline for stage IV periodontitis places tooth replacement, with tooth- or implant-supported prostheses, within an overall treatment plan, once the phase that treats the infection is complete [4]. The 2023 EFP guideline on peri-implant diseases is explicit: prevention begins when the implant is planned and continues through regular follow-up [5].
The pathway, step by step
- Full periodontal assessment and examination of the area to be restored.
- Treatment of periodontitis where needed, followed by re-evaluation.
- 3D imaging (cone beam CT) and software planning, starting from the future tooth.
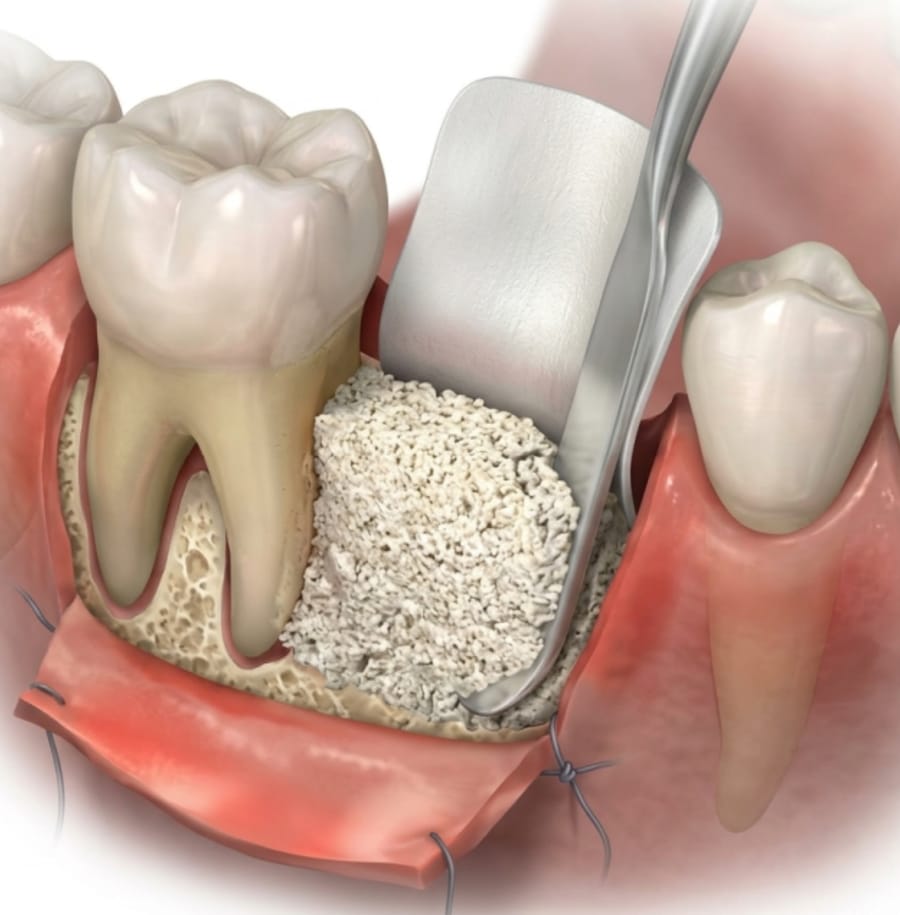
- Bone grafting if the bone volume is insufficient (sometimes at the same time as the implant).
- Implant placement, with a surgical guide where useful.
- Healing, then fitting of the crown.
- Lifelong periodontal and peri-implant maintenance.
The surgical procedures (graft, implant placement) take place under local anaesthetic in the practice’s operating room. The crown is then made in coordination with your own dentist when they provide the prosthetic part. The principle of placement is described in detail on the page Placing an implant and guided surgery.
For anxious patients: conscious sedation with nitrous oxide (MEOPA)
Dreading surgery is common, especially after a bad experience at the dentist. In the practice’s operating room, Dr Hazout can offer conscious sedation with MEOPA in addition to local anaesthetic: for implant placement, a bone or gum graft, or another oral surgery procedure.
MEOPA is an equal mixture of two gases, oxygen and nitrous oxide, breathed through a small mask placed over the nose. It works within a few minutes: anxiety eases and sensations feel less sharp, without putting you to sleep. You stay conscious, breathe on your own and can answer at any time. The effect wears off quickly once the mask is removed.
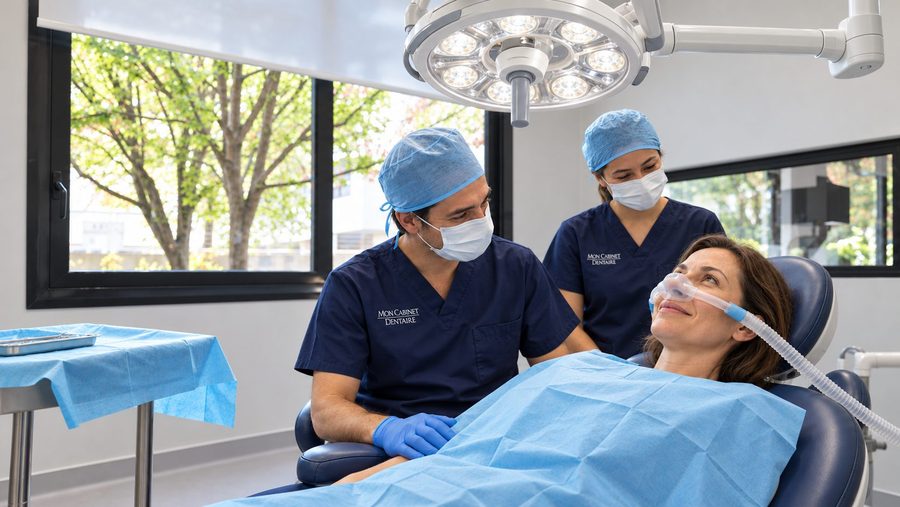
MEOPA does not replace local anaesthetic: it is added to it. It is not suitable for every medical situation; whether it is useful for you, and any contraindication, is reviewed at the consultation before the procedure.
Dr Hazout completed the course “Nitrous Oxide/Oxygen Sedation in the Dental Office for Anxiety and Pain” (Air Liquide Healthcare, accredited course, 2019), listed on his background page.
Which page should you read?
| Your question | Page to read |
|---|---|
| How is an implant placed? What does guided surgery change? | Implants and guided surgery |
| I have been told there is not enough bone: what techniques exist? | Bone grafts and regeneration |
| I have been told I need a sinus lift (graft below the sinus, upper back jaw) | The sinus lift, on the bone grafts page |
| I have been offered a custom titanium mesh | Custom titanium mesh |
| I have periodontitis, or gums that bleed | Periodontitis treatment |
| How do I look after my implants day to day? | Gum care around implants |
Limitations, relative contraindications and possible failures
Absolute contraindications to implants are rare; several situations, however, raise the risk of failure and are discussed before any decision. Smoking is associated with more failures and more bone loss around implants. Poorly controlled diabetes goes hand in hand with more peri-implantitis, whereas well-controlled diabetes gives results comparable to those of people without diabetes. Unstable periodontitis means placement is postponed. Certain treatments (high-dose antiresorptive bone medication, head and neck radiotherapy) and an unstable general condition call for a joint opinion with your doctor. These factors, and the studies that document them, are developed on the page devoted to implant placement.
An implant can fail in two ways. Early failure occurs in the first months: the bone does not fuse, the implant becomes mobile and has to be removed; a new placement is often possible after healing. Late failure appears years later, most often through peri-implantitis: an infection of the tissues surrounding the implant, comparable to periodontitis, which destroys the supporting bone. It strikes more readily in people who have had periodontitis, in smokers, and in those who slip out of regular follow-up. It often advances quietly: an implant can lose bone without the slightest pain, which is why check-ups matter.
Lifespan and follow-up: the gums decide
A meta-analysis of 18 studies estimates ten-year implant survival at 96.4%; a more cautious sensitivity analysis puts it at 93.2%, with lower survival in people aged 65 and over [6]. Surviving is not the same as being untouched: an implant still in the mouth can develop peri-implantitis. That is why follow-up carries as much weight as the surgery.
This follow-up takes the form of periodontal maintenance visits whose frequency depends on your level of risk: checking the gums around teeth and implants, professional cleaning, and X-rays at regular intervals to monitor the bone. Between visits, daily cleaning around the implants (interdental brushes, attentive brushing at the neck of the crown) remains the first line of protection. The article Gum care around implants details these habits and explains mucositis and peri-implantitis.
Related articles

How is a titanium mesh made by 3D printing?
A custom titanium mesh exists in a single copy: one patient, one bone defect. Between the scan image and the sterile part used in theatre lie a digital workflow and an…
Why plan in 3D before a bone graft and an implant?
A conventional X-ray shows bone from the front, like a cast shadow, and says nothing about its width. Yet width is often what decides: will the implant hold on its own,…
Gum care around implants: preventing peri-implant mucositis and peri-implantitis
An implant cannot decay. But the gum and bone around it can become inflamed and break down, sometimes faster than around a tooth. The two diseases involved, peri-implant…
Frequently asked questions
Can I have an implant if I have had periodontitis?
Usually yes, provided the periodontitis has been treated and is stable before placement, and you then keep up regular maintenance. The risk of peri-implantitis remains higher than in people without such a history; that is precisely what makes this follow-up worthwhile.
Is a bone graft always needed?
No. A graft is only worthwhile when there is not enough bone to place the implant in the right position, which the cone beam CT can measure. In some cases a short implant or another type of prosthesis is an alternative worth discussing.
Can an implant get gum disease?
Yes. Mucositis, and then peri-implantitis, are inflammations of the tissues surrounding the implant, linked in particular to dental plaque. Appropriate cleaning and regular check-ups are the first line of prevention.
What happens if an implant fails?
An implant that does not integrate, or that loses its supporting bone, is removed. After healing, and sometimes after a graft, a new placement is often possible. The causes of the failure (infection, smoking, overload, hygiene) are looked for so that they are not repeated.
How much does an implant cost?
Fees depend on the number of implants, whether a graft is needed and the type of prosthesis. The ranges charged at the practice are given on the Fees page; a detailed estimate is given to you after the assessment.
Scientific sources (6)
- Tan WL, Wong TL, Wong MC, Lang NP. A systematic review of post-extractional alveolar hard and soft tissue dimensional changes in humans. Clin Oral Implants Res. 2012;23 Suppl 5:1-21. DOI
- Lee BA, Kim B, Kim YT. Supraeruption as a consideration for implant restoration. J Periodontal Implant Sci. 2020;50(4):260-267. DOI
- Marty L, Hoornaert A, Enkel B, Penhoat A, Colat-Parros J, Soueidan A, Jordana F. Implant Health in Treated Periodontitis Patients: A Systematic Review and Meta-Analysis. Dent J (Basel). 2024;12(8):240. DOI
- Herrera D, Sanz M, Kebschull M, Jepsen S, Sculean A, Berglundh T, Papapanou PN, Chapple I, Tonetti MS. Treatment of stage IV periodontitis: The EFP S3 level clinical practice guideline. J Clin Periodontol. 2022;49 Suppl 24:4-71. DOI
- Herrera D, Berglundh T, Schwarz F, Chapple I, Jepsen S, Sculean A, Kebschull M, Papapanou PN, Tonetti MS, Sanz M; EFP Workshop Participants and Methodological Consultant. Prevention and treatment of peri-implant diseases—The EFP S3 level clinical practice guideline. J Clin Periodontol. 2023;50 Suppl 26:4-76. DOI
- Howe MS, Keys W, Richards D. Long-term (10-year) dental implant survival: A systematic review and sensitivity meta-analysis. J Dent. 2019;84:9-21. DOI
Page written by Dr Victor Hazout, periodontist · updated on 23 October 2026
Patient pathway