









Bone grafting before an implant: when it is needed, and which techniques
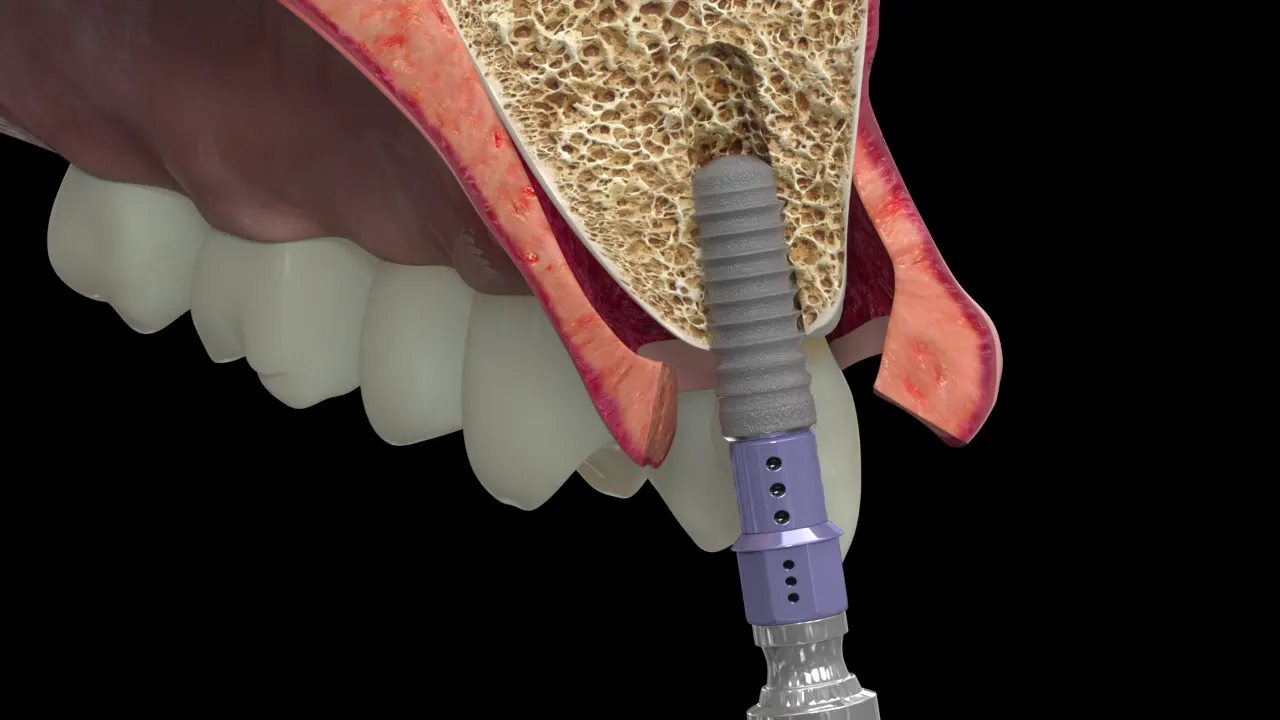
An implant only holds in bone, along its whole length. When that bone is missing, it can be rebuilt, and several techniques achieve this, each suited to a particular shape and size of defect. This page is for anyone who has been told they may need a graft: how missing bone is measured, how the technique is chosen, which materials are used, what the operation involves in principle, and what you should know about its risks and limits.
Why does bone go missing, and how is it measured?
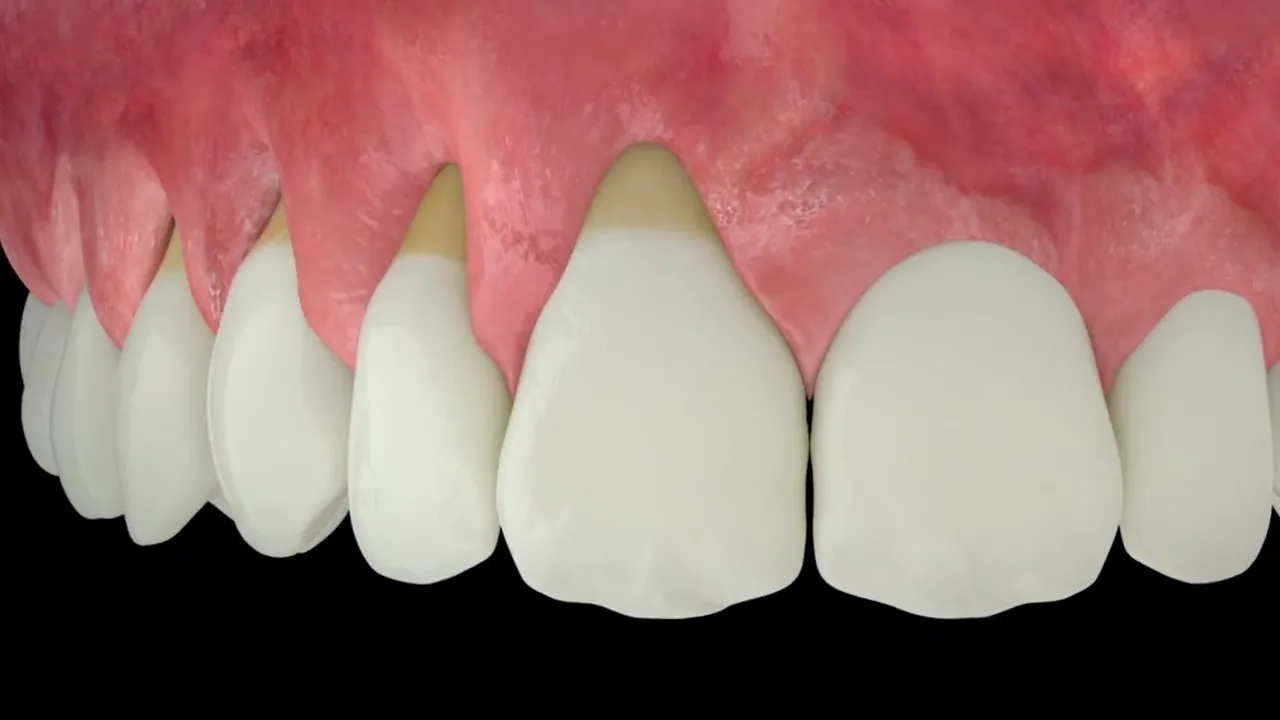
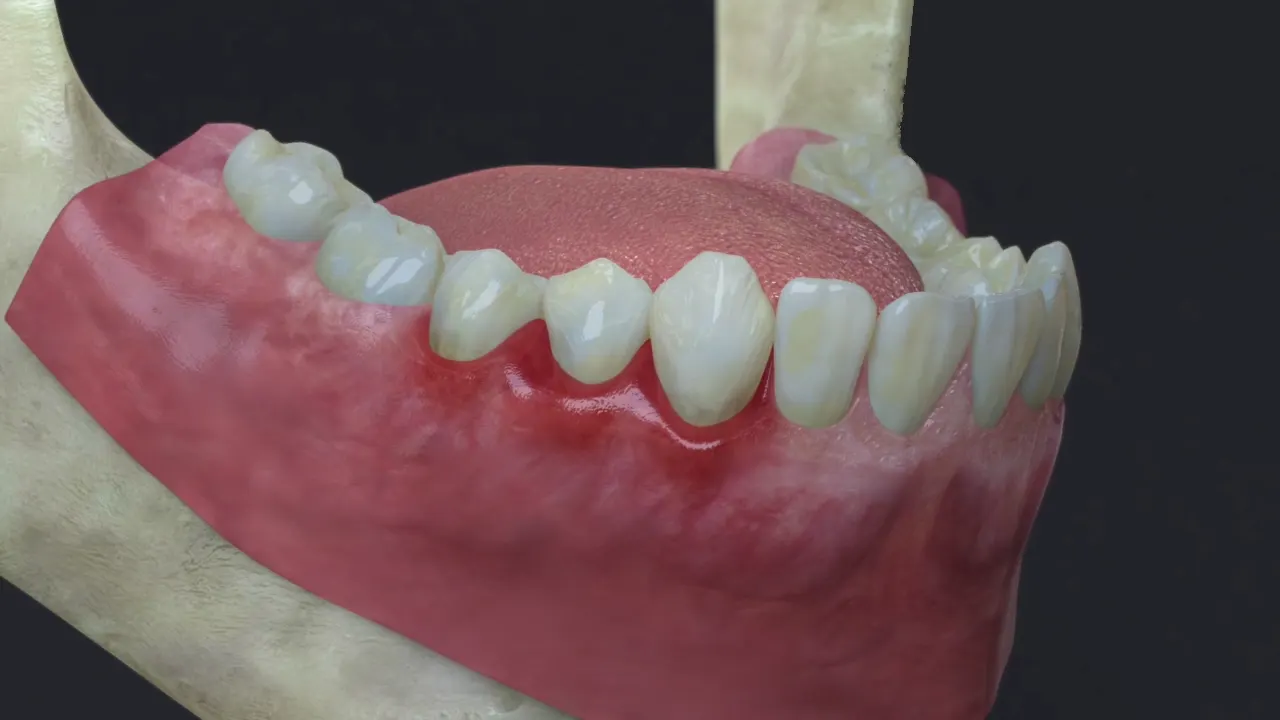
The first cause is resorption after extraction. With no root left to support, the ridge melts away: on average 3.8 mm of width and 1.2 mm of height are lost within six months, according to a systematic review [1]. The second cause, the one most familiar to a periodontist, is long-standing periodontitis: the infection has eaten into the bone around the roots well before the tooth was lost, leaving a defect that is deeper and more irregular. An infection at the tip of a root, a cyst, a fracture or an injury can also take bone with them. In the upper jaw, behind the premolars, the sinus (an air-filled cavity above the roots) may in addition drop down towards the ridge after the teeth are lost.
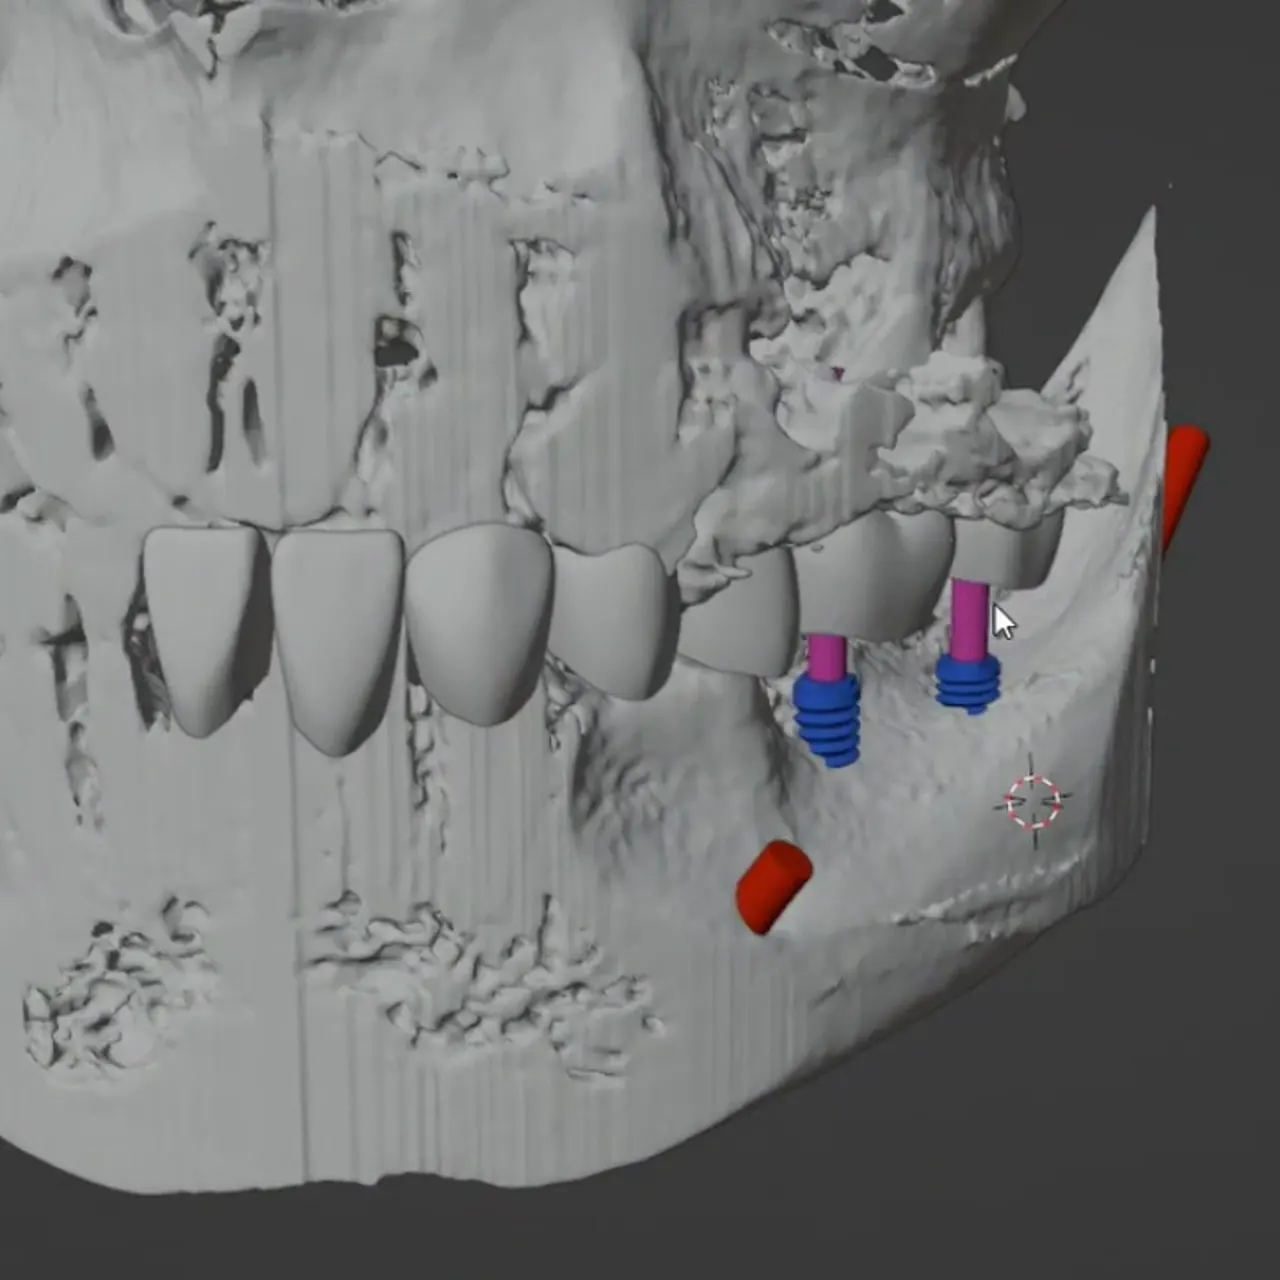
This loss is not always obvious in the mouth, nor on a conventional X-ray, which shows height but says nothing about width. The cone beam CT (a three-dimensional dental scan) measures it: on slices cut across the ridge, Dr Hazout reads the height available down to the nerve or the sinus, the width at several levels and the exact shape of the defect. A ridge that looks sound can turn out, deeper down, to be as thin as a blade.
From this come three families of defect: horizontal (ridge too thin, height preserved), vertical (ridge too low) and combined. This reading settles everything: whether to graft, with which technique, and when, before the implant (two-stage) or during the same operation (one-stage). The full reasoning is set out in the article Why plan in 3D before a bone graft and an implant?
Preserving bone from the moment of extraction
Alveolar ridge preservation fills the socket (the space left by the root) with graft material, usually beneath a membrane. A Cochrane review of 16 randomised trials puts a figure on its effect with a xenograft: loss reduced by about 1.2 mm in width and 1.4 mm in height at six months compared with spontaneous healing, with very low certainty of evidence and no proven effect on implant failure [2]. It is mainly considered when an implant is planned and the bone wall is thin.
It does not abolish resorption: it slows it. Its value lies in making a heavier reconstruction later less likely. It calls for an extraction as gentle as possible, one that respects the walls of the socket.
Guided bone regeneration (GBR)
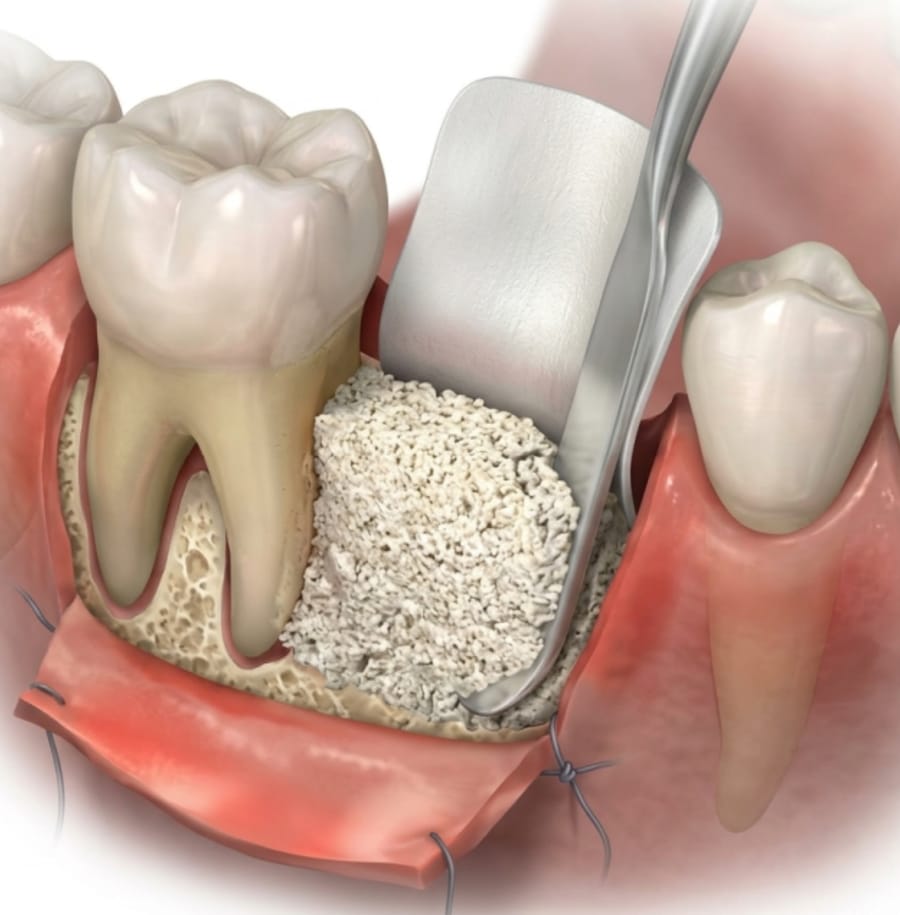
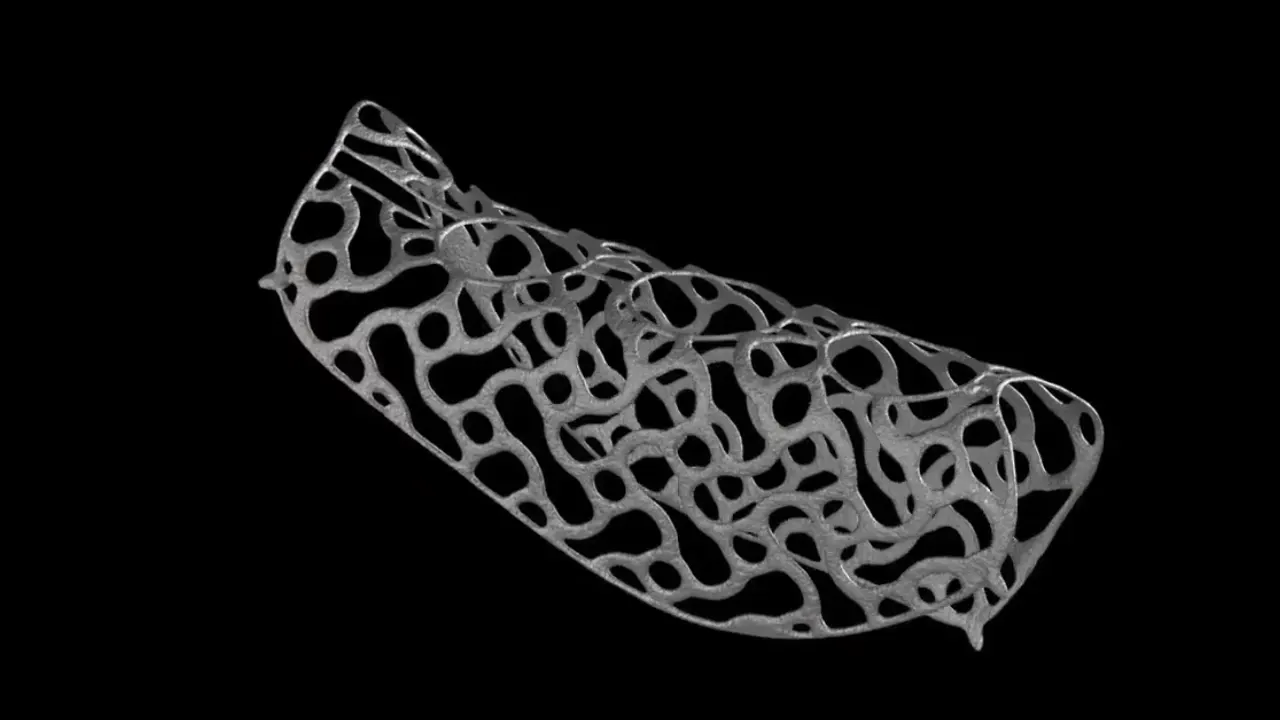
GBR comes down to one idea: graft material laid against the bone, then sealed off from the gum by a membrane. This barrier gives the slower bone cells time to occupy the space before gum cells invade it. Resorbable (collagen) or not, for larger reconstructions it is reinforced with titanium or replaced by a titanium mesh that holds the volume.
It is the most widely used technique for horizontal and moderate defects. For height, where gain is harder to achieve, a meta-analysis reports a mean of 4.2 mm with GBR against 3.5 mm with bone blocks, with complications in 12% of cases for GBR against 24% for blocks [3].
Bone blocks
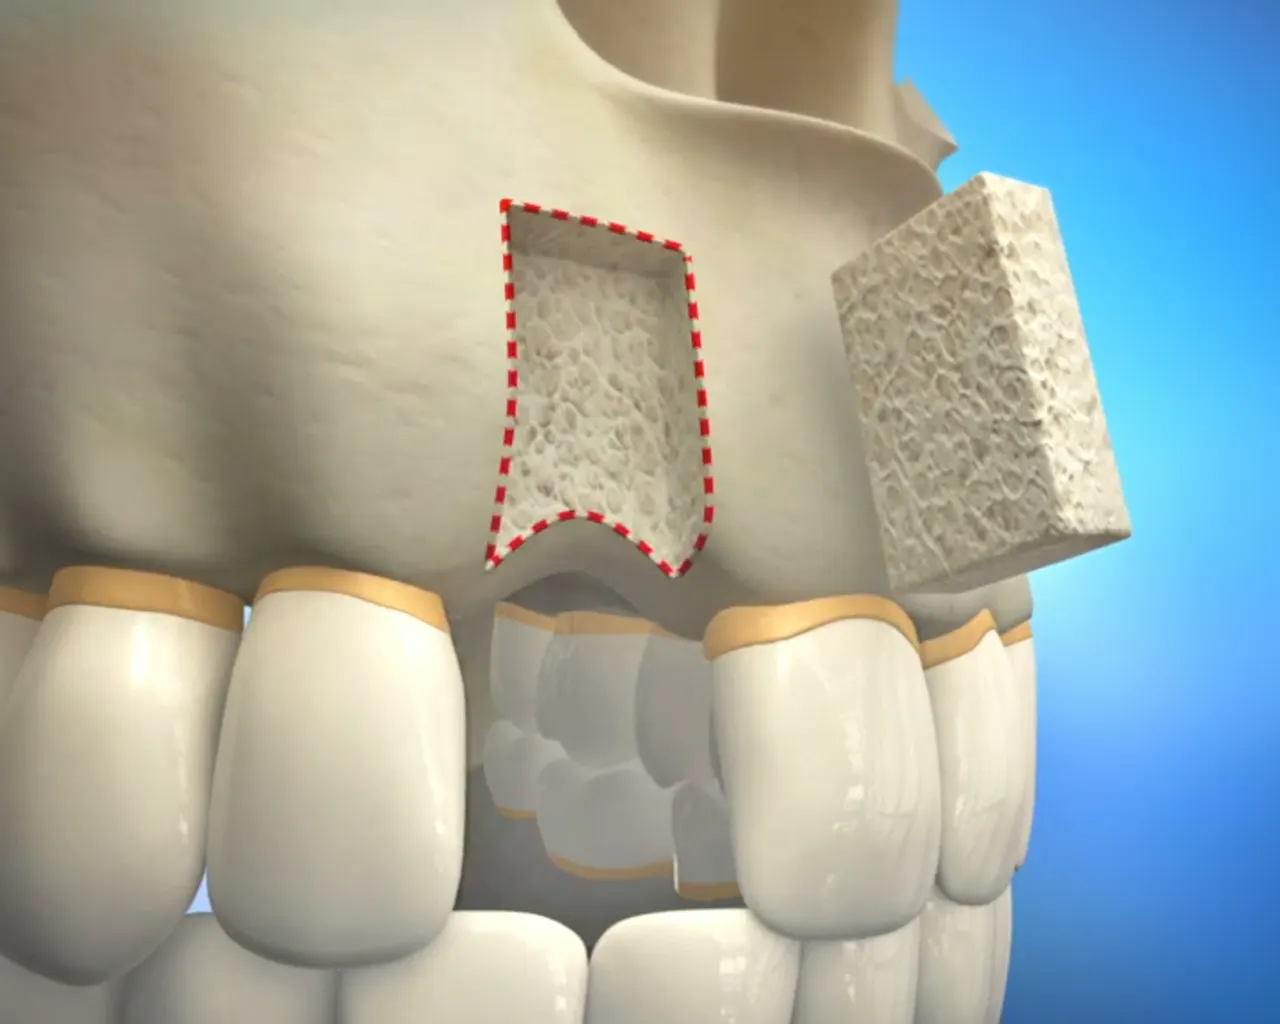
A block is a piece of dense bone, most often taken from the patient’s own jaw (angle of the mandible, chin) or of animal origin, then screwed onto the ridge. It mainly addresses defects in width. The trade-off is usually a second surgical site, with its own risks, including temporary changes in sensation near the donor area.
Sinus lift
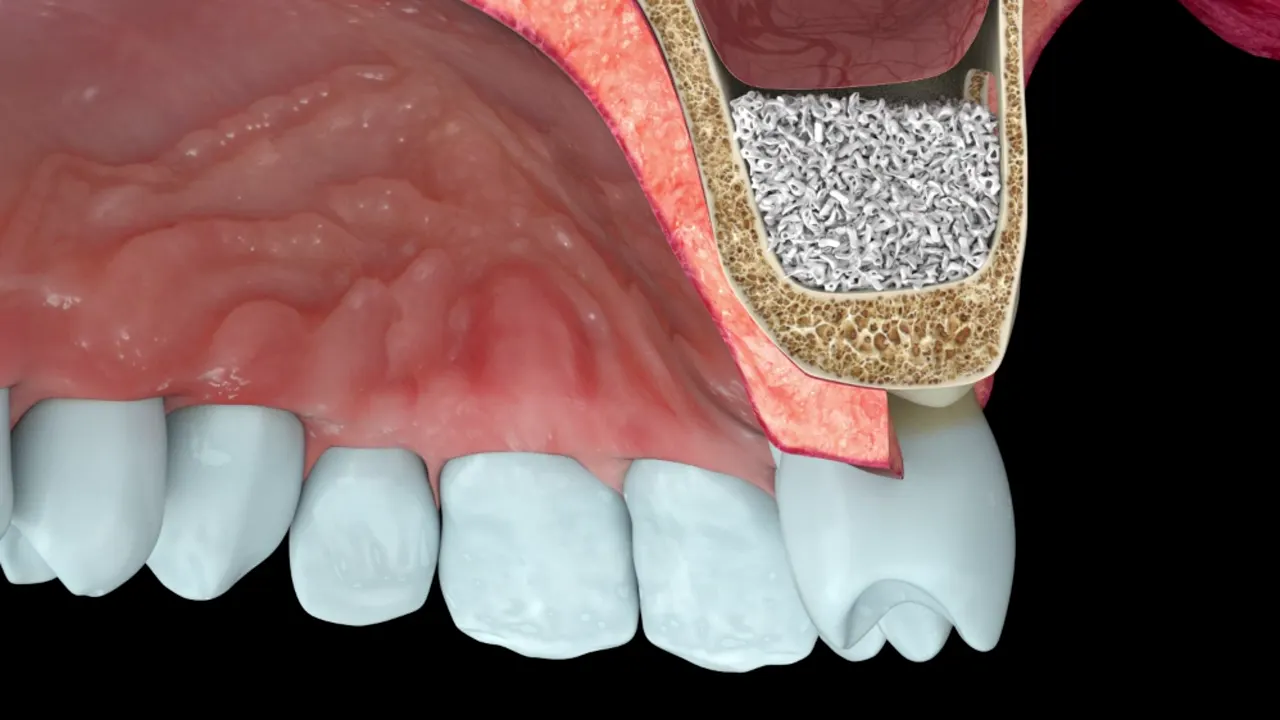
A sinus lift raises the thin membrane lining the sinus and slips graft material beneath it, to recreate the bone height missing in the upper jaw behind the premolars. There are two approaches; the bone height remaining below the sinus decides between them.
- Lateral approach: through a small window opened in the sinus wall, when little height remains. A systematic review reports 90.1% implant survival at three years; membrane perforation is the most frequent complication (19.5% on average), while graft infection stays rare (2.9%) [4].
- Crestal (transalveolar) approach: through the implant’s own drill hole, when more height remains. Survival is 92.8% at three years, comparable to implants placed without grafting [5].
A membrane perforation spotted during surgery is usually repaired on the spot; occasionally it means postponing the graft.
Which materials?
| Material | Origin | Good to know |
|---|---|---|
| Autogenous | Patient’s own bone (chips or block) | Contains living cells; requires harvesting |
| Xenograft | Processed bovine bone with the organic part removed | Resorbs slowly and maintains volume; often mixed with autogenous bone |
| Allograft | Processed human bank bone | Avoids harvesting |
| Synthetic | Calcium phosphates | No biological origin |
For sinus lifts, a Cochrane review found no difference in failure between autogenous bone and bone substitutes, for want of sufficient evidence [6]. The choice is therefore made case by case: the volume to rebuild, the need to hold the shape over time, and your own preferences.
What does a graft involve in principle?
Whatever the technique, the graft is performed under local anaesthetic, in the operating room of the practice in Levallois-Perret. The gum is lifted to uncover the bone; the material is placed and then protected (membrane, mesh or screws depending on the technique); the gum is closed without tension over the added volume. The grafted bone must then form before the implants go in, and a new cone beam CT, limited to the grafted area, often serves to check the volume obtained. The practical arrangements, the course of treatment and the instructions are explained to you at the practice, according to your situation.
Risks, limitations and alternatives
The possible complications: exposure of the membrane or mesh through the gum, infection, partial loss of the graft, pain or swelling and, in the upper jaw, perforation of the sinus membrane. In the lower jaw, the nearby nerve makes 3D planning indispensable. A graft does not always deliver all the volume hoped for: part of the material resorbs during healing, which planning anticipates, and a further graft is sometimes needed at the time the implant is placed.
Some situations lower the chances of success or mean postponing surgery: smoking, poorly controlled diabetes, unstable periodontitis, thin or scarred gum that is hard to close, certain bone medications. And the larger the volume to rebuild, above all in height, the more complications multiply, as the figures quoted above show [3].
Grafting is not always the only route. In the lower jaw, a meta-analysis of randomised trials found comparable five-year results between short implants and vertical augmentation followed by standard implants, with fewer complications for short implants [7]. In the upper jaw, a Cochrane review could not separate sinus lift from short implants, but noted more complications with sinus lift [6]. A tooth-supported bridge or a removable denture remain options too, to be discussed according to your situation.
Frequently asked questions
Can the implant be placed at the same time as the graft?
Yes, when the remaining bone is enough to stabilise the implant and the defect is limited. For large defects, the graft comes first and the implant follows once the bone has formed.
Is animal bone used?
Often, yes: processed bovine bone is an extensively studied material, sometimes mixed with your own bone. If you would rather avoid it, for personal or religious reasons, other materials can be considered.
Can a graft fail?
Yes. Membrane exposure, infection or partial loss of the graft remain possible and sometimes call for further grafting. Smoking increases these risks.
How much does a bone graft cost?
It varies with the technique, the volume and the materials. The ranges charged at the practice are given on the Fees page, and a detailed estimate is given to you after the assessment.
Scientific sources (7)
- Tan WL, Wong TL, Wong MC, Lang NP. A systematic review of post-extractional alveolar hard and soft tissue dimensional changes in humans. Clin Oral Implants Res. 2012;23 Suppl 5:1-21. DOI
- Atieh MA, Alsabeeha NHM, Payne AGT, Ali S, Faggion CM Jr, Esposito M. Interventions for replacing missing teeth: alveolar ridge preservation techniques for dental implant site development. Cochrane Database Syst Rev. 2021;4:CD010176. DOI
- Urban IA, Montero E, Monje A, Sanz-Sánchez I. Effectiveness of vertical ridge augmentation interventions: A systematic review and meta-analysis. J Clin Periodontol. 2019;46 Suppl 21:319-339. DOI
- Pjetursson BE, Tan WC, Zwahlen M, Lang NP. A systematic review of the success of sinus floor elevation and survival of implants inserted in combination with sinus floor elevation. Part I: lateral approach. J Clin Periodontol. 2008;35(8 Suppl):216-240. DOI
- Tan WC, Lang NP, Zwahlen M, Pjetursson BE. A systematic review of the success of sinus floor elevation and survival of implants inserted in combination with sinus floor elevation. Part II: transalveolar technique. J Clin Periodontol. 2008;35(8 Suppl):241-254. DOI
- Esposito M, Felice P, Worthington HV. Interventions for replacing missing teeth: augmentation procedures of the maxillary sinus. Cochrane Database Syst Rev. 2014;CD008397. DOI
- Terheyden H, Meijer GJ, Raghoebar GM. Vertical bone augmentation and regular implants versus short implants in the vertically deficient posterior mandible: a systematic review and meta-analysis of randomized studies. Int J Oral Maxillofac Surg. 2021;50(9):1249-1258. DOI
Page written by Dr Victor Hazout, periodontist · updated on 11 October 2026
Patient pathway