








Understanding periodontitis: recognising the signs and how it is diagnosed
Periodontitis is among the most common chronic diseases, and among the least noticed. It advances without pain, and its first signs pass for merely irritated gums: bleeding when brushing and, much later, receding gums and teeth that seem to loosen. This article explains how to tell it apart from gingivitis, which signs and risk factors should alert you, what “receding gums” really covers and how the diagnosis is reached.
Key points
- Gingivitis is reversible inflammation of the gum; periodontitis destroys the attachment and bone that support the teeth, which patients often describe as receding or loosening teeth.
- The disease is often silent: no pain, bleeding masked in smokers, slow progression over years.
- Smoking, poorly controlled diabetes and a family predisposition are well-documented risk factors; the association with stress is less clear.
- Severe periodontitis affects about one person in ten worldwide.
- Only a full periodontal examination, clinical and radiographic, can establish the diagnosis, classify it by stage and grade and guide treatment.
Gingivitis or periodontitis: where is the line?
It all starts with dental plaque, an organised film of bacteria (a biofilm) that re-forms relentlessly on the tooth surface. When it builds up along the gum line, the body answers with inflammation: this is gingivitis. The gum reddens, swells and bleeds at the slightest touch. At this stage nothing is lost: once plaque is removed regularly, the gum returns to health.
The 2018 international consensus makes gingivitis a major risk factor for, and a necessary precursor of, periodontitis [1]. Not every case of gingivitis progresses to periodontitis, but treating gingivitis is considered primary prevention of periodontitis.
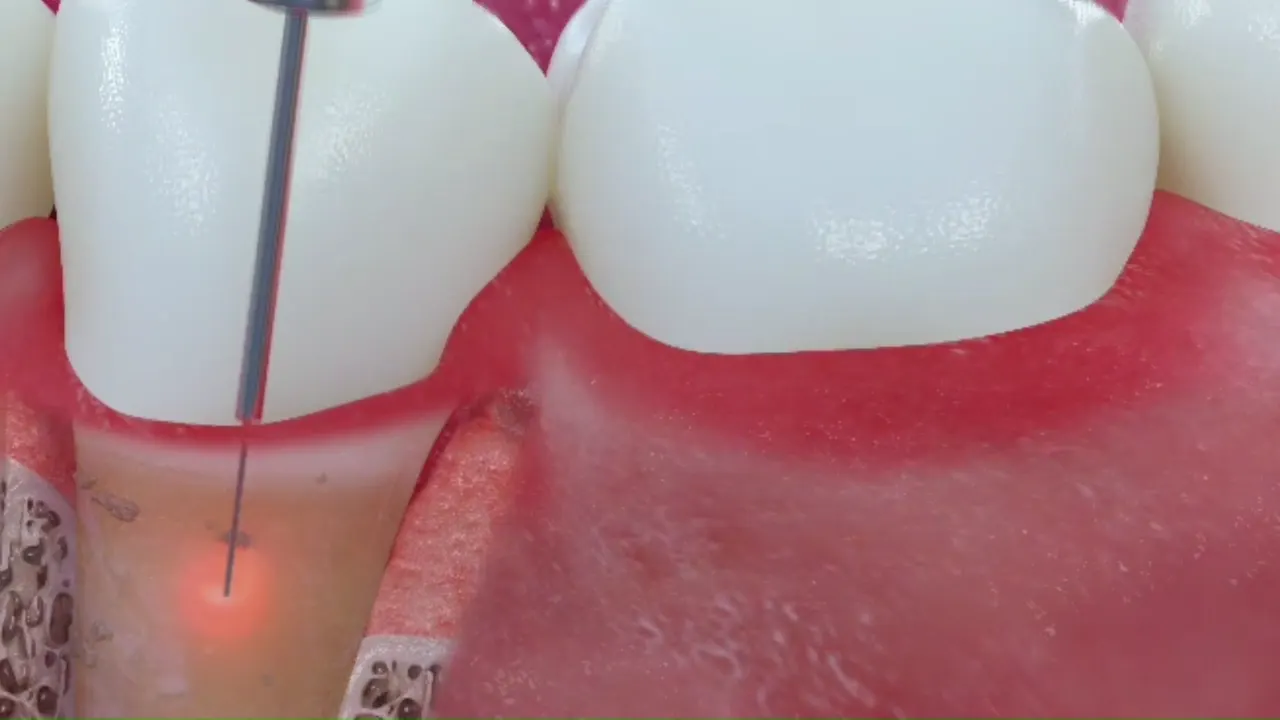
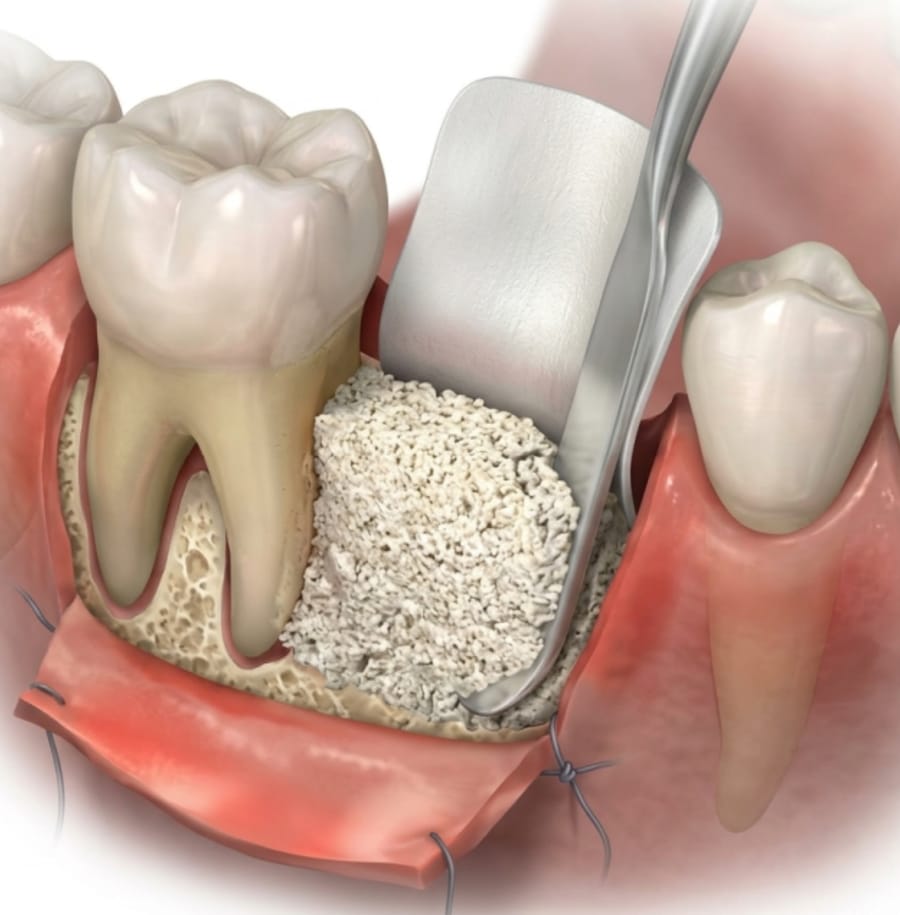
We speak of periodontitis when the inflammation has destroyed part of the attachment: first the fibres that connect the root to the bone, then the bone itself. A pocket opens between the gum and the root; plaque lodged there is now beyond the reach of the toothbrush. This loss of attachment and bone is what defines periodontitis in the 2018 international classification [2]; what is lost does not come back on its own.
Gingivitis can be cured
Gingivitis is the only fully reversible stage. A professional clean removes plaque and tartar; then suitable brushing and daily cleaning between the teeth give the gum back its firmness and pink colour within a few weeks. Bleeding remains the most reliable indicator: when it stops, the inflammation has settled.
If bleeding persists despite careful hygiene, a periodontal assessment checks that it is not already periodontitis. See also: gingivitis: symptoms and treatment.
Why does the disease go unnoticed?
Several reasons explain why periodontitis is so often discovered late:
- It rarely hurts. Chronic gum inflammation causes little pain, except when an abscess forms.
- Bleeding is dismissed. Many people think it is normal for gums to bleed a little when brushing.
- Smoking masks the signs. It reduces blood flow in the gum, which bleeds less despite the disease.
- It progresses slowly, often in bursts, and teeth stay firm until an advanced stage.
- It first affects areas that are hard to see: between the teeth and at the back of the mouth.
The landmark review of the global burden of the disease found a steep rise in the prevalence of severe periodontitis between the third and fourth decades of life, with a peak in onset around the age of 38 [3]. Screening is therefore often most useful in adults who feel nothing yet.
Warning signs
“My gums bleed when I brush” is the most frequent reason for consulting, and the one most often played down. Healthy gum does not bleed, even under vigorous brushing or flossing. The following signs, alone or combined, should lead to an examination:
- gums that bleed when brushing, flossing or using interdental brushes, or spontaneously;
- red, swollen, tender gums;
- bad breath or a bad taste that will not go away;
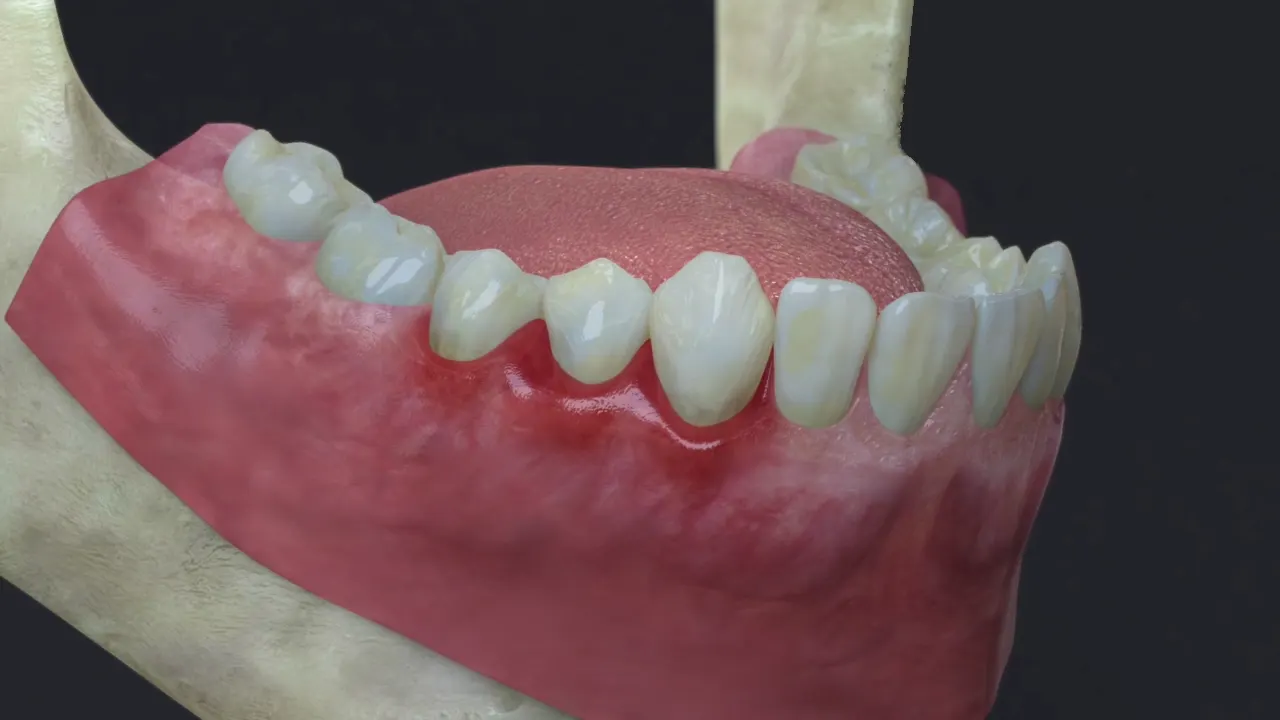
- receding gums, teeth that look longer: what is commonly called receding or “loosening” teeth;
- sensitivity to cold at the neck of the teeth;
- gaps opening between teeth, teeth that drift or flare forward;
- loose teeth, a feeling that your bite has changed;
- a gum abscess: localised swelling, sometimes with pus.
None of these signs on its own tells gingivitis from periodontitis. If they persist for more than two weeks despite careful brushing, an examination is warranted.
Receding gums and “loose teeth”: what the words cover
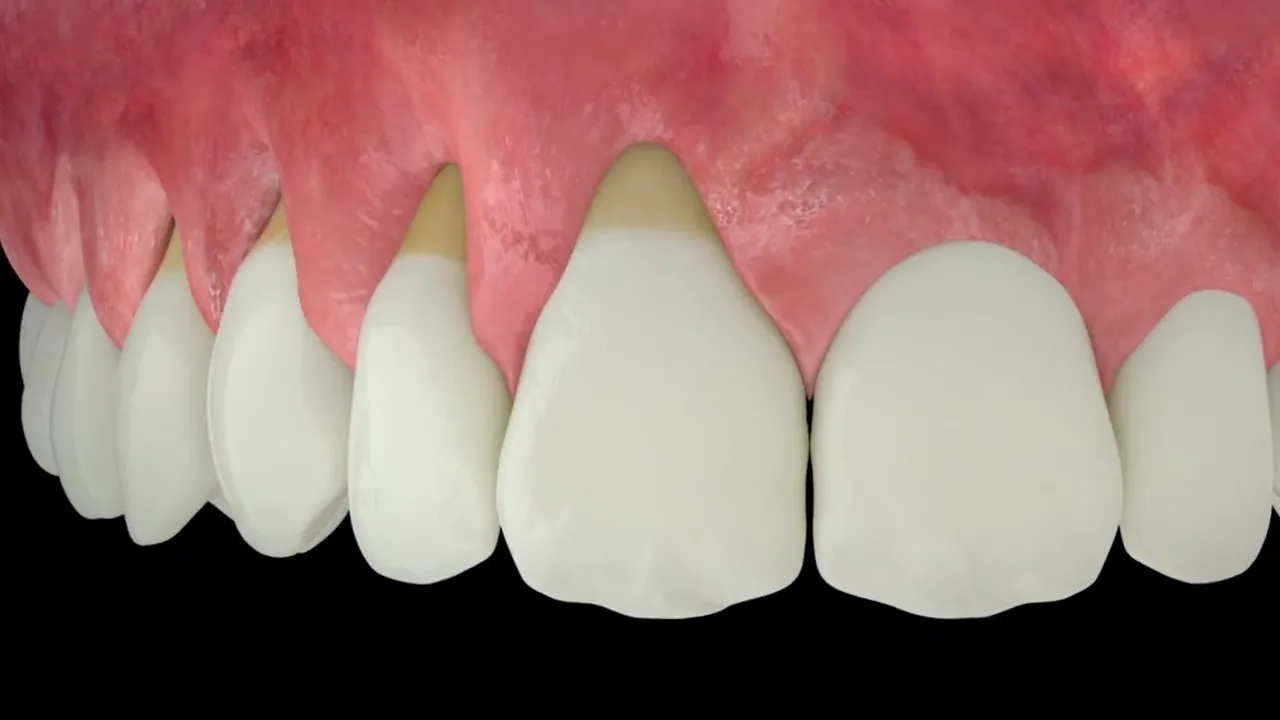
Patients speak of receding gums or teeth “coming loose” when the gum slides down the roots, teeth look longer, dark spaces open between them or a tooth starts to move. The medical term is gum recession when the gum margin itself has moved, and attachment loss when the bone and supporting fibres have gone. In periodontitis the two often go hand in hand: the bone resorbs, the gum that covered it follows, and the root is laid bare.
Not every receding gum is periodontitis, however. Gum can recede on a healthy tooth under over-vigorous brushing, because it is naturally thin or because the tooth sits out of line, with no inflammation and no pocket. Only an examination settles it, and the approach differs: treating the infection in one case, protecting or covering the root in the other. Isolated recessions and their treatment by gum graft have their own page.
One point deserves emphasis: gum that recedes during periodontitis treatment is not a sign of worsening. As the inflammation settles, the swollen gum shrinks back onto bone that was already reduced; the teeth look longer, but they are better supported. This is a sign of healing, not of advancing disease.
Risk factors
Plaque is necessary for the disease, but on its own it does not explain why some people lose their teeth and others do not. The body's response, shaped by several factors, plays a decisive role.
Smoking. A meta-analysis of follow-up studies estimates that smoking raises the risk of developing or worsening periodontitis by about 85% (relative risk 1.85) [6]. This is an observed association, but a strong one, consistent across studies and backed by known mechanisms (narrowing of blood vessels, impaired immune response and healing). Smoking is also one of the two main risk factors named by the World Health Organization, together with poor oral hygiene [5].
Diabetes. In 2018, the European Federation of Periodontology and the International Diabetes Federation published a joint consensus on the links between the two diseases [7]. It describes a two-way relationship: poorly controlled diabetes is associated with more frequent and more severe periodontitis, while untreated periodontitis is associated with poorer blood sugar control. When diabetes is well controlled, periodontal risk comes close to that of the general population. The mechanisms, the figures and the effect of periodontal treatment on blood sugar are developed in the article Diabetes and periodontitis.
Genetics. An older but widely cited twin study estimated that about half of the variation in adult periodontitis in the population was genetic, even once smoking was taken into account [8]. No genetic test is of practical use in routine care today; a family history of early tooth loss, however, is a good reason to be screened.
Stress and emotional disorders. A 2021 meta-analysis found an association between periodontitis and depression or anxiety [9]. The data come mainly from case–control studies, some of them contradictory, and the relationship may run both ways. It cannot be concluded that stress causes periodontitis: this is an association, whose mechanisms (stress hormones, neglected oral hygiene, smoking) remain to be clarified.
Other factors weigh in: age, some diseases or treatments that weaken immunity, insufficient oral hygiene, overhanging fillings or crowded teeth that trap plaque.
How many people are affected?
The World Health Organization estimates that severe periodontal diseases account for more than one billion cases worldwide [5]. According to the systematic review by Kassebaum et al., severe periodontitis affected 10.8% of the world's population in 2010, about 743 million people, making it the sixth most prevalent condition [3].
In the United States, the 2009–2010 national health survey, based on a full-mouth examination, found periodontitis in more than 47% of adults aged 30 and over (8.5% severe), and moderate or severe disease in 64% of those over 65 [4]. Figures vary with definitions and examination methods, but every study points the same way: the disease is common and grows more so with age.
A quick self-check
These questions do not replace an examination, but they can help you decide whether it is time to ask for one:
| Question | If the answer is yes |
|---|---|
| Do your gums bleed regularly when you brush? | A sign of inflammation, worth assessing |
| Do your teeth seem to be getting longer or moving? | Possible loss of support |
| Is a tooth loose? | Examination recommended without delay |
| Do you smoke, or do you have diabetes? | Higher risk: screening useful even without symptoms |
| Did a close relative lose their teeth before 60? | Possible predisposition |
| Was your last gum examination more than a year ago? | A check-up is sensible |
A single “yes” is enough to justify a check-up. No “yes” answers does not rule out the disease, particularly in smokers, whose gums bleed little.
How is the diagnosis made?
The diagnosis rests on two simple examinations, painless in the great majority of cases.
Examining the gums. Bleeding, plaque, tooth mobility and involvement between the roots of molars are recorded.
X-rays. They show the height of the bone around the roots and the pattern of bone loss, horizontal or crater-shaped.
The clinical examination and X-rays confirm or rule out periodontitis, then describe it according to the 2018 classification [2]. The stage (I to IV) reflects severity and complexity: at stage I, bone loss is confined to the upper part of the root; at stage IV, teeth have already been lost to the disease and chewing is impaired. The grade (A to C) reflects the rate of progression, slow, moderate or rapid, taking smoking and diabetes into account [10]. This classification is not a mere label: it sets the intensity of treatment and the pace of follow-up. Its practical consequences and the steps of treatment are explained on the page How periodontitis is treated; long-term follow-up, on the Periodontal maintenance page.
At Dr Hazout's practice in Levallois-Perret, this assessment is carried out from the first consultation, with the necessary X-rays; what it involves and what to bring are described on the First visit page.
Frequently asked questions
Can you have periodontitis without bleeding?
Yes, particularly in smokers, whose gums bleed less, or in areas with little inflammation. That is why a full periodontal examination is essential.
At what age should I be screened?
There is no strict minimum age. Severe forms often appear between 30 and 40; a gum examination should be part of every adult dental check-up, and earlier if there is a family history, smoking or diabetes.
My parents lost their teeth: am I bound to do the same?
No. A predisposition raises the risk, but does not decide the outcome on its own. Early screening, suitable oral hygiene and regular follow-up make a clear difference to the outlook.
Are receding gums and periodontitis the same thing?
Not always. Receding gums describes what you see: the gum margin moving back and the root becoming exposed. It is most often the consequence of periodontitis, but gum can also recede on a healthy tooth, under over-vigorous brushing for instance. Examining the gums and X-rays settle the question.
Does bad breath mean periodontitis?
Not necessarily. It most often comes from the tongue or from gingivitis, more rarely from other causes. Persistent bad breath does, however, warrant a gum examination.
Scientific sources (10)
- Chapple ILC, Mealey BL, Van Dyke TE, et al. Periodontal health and gingival diseases and conditions on an intact and a reduced periodontium: Consensus report of workgroup 1 of the 2017 World Workshop on the Classification of Periodontal and Peri-Implant Diseases and Conditions. J Clin Periodontol. 2018;45 Suppl 20:S68-S77. DOI
- Papapanou PN, Sanz M, et al. Periodontitis: Consensus report of workgroup 2 of the 2017 World Workshop on the Classification of Periodontal and Peri-Implant Diseases and Conditions. J Clin Periodontol. 2018;45 Suppl 20:S162-S170. DOI
- Kassebaum NJ, Bernabé E, Dahiya M, Bhandari B, Murray CJL, Marcenes W. Global burden of severe periodontitis in 1990-2010: a systematic review and meta-regression. J Dent Res. 2014;93(11):1045-1053. PubMed
- Eke PI, Dye BA, Wei L, Thornton-Evans GO, Genco RJ. Prevalence of periodontitis in adults in the United States: 2009 and 2010. J Dent Res. 2012;91(10):914-920. DOI
- World Health Organization. Oral health – Fact sheet (updated 17 March 2025). who.int
- Leite FRM, Nascimento GG, Scheutz F, López R. Effect of smoking on periodontitis: a systematic review and meta-regression. Am J Prev Med. 2018;54(6):831-841. PubMed
- Sanz M, Ceriello A, Buysschaert M, et al. Scientific evidence on the links between periodontal diseases and diabetes: Consensus report and guidelines of the joint workshop on periodontal diseases and diabetes by the International Diabetes Federation and the European Federation of Periodontology. J Clin Periodontol. 2018;45(2):138-149. DOI
- Michalowicz BS, Diehl SR, Gunsolley JC, Sparks BS, Brooks CN, Koertge TE, Califano JV, Burmeister JA, Schenkein HA. Evidence of a substantial genetic basis for risk of adult periodontitis. J Periodontol. 2000;71(11):1699-1707. DOI
- Zheng DX, Kang XN, Wang YX, et al. Periodontal disease and emotional disorders: A meta-analysis. J Clin Periodontol. 2021;48:180-204. DOI
- Tonetti MS, Greenwell H, Kornman KS. Staging and grading of periodontitis: Framework and proposal of a new classification and case definition. J Periodontol. 2018;89 Suppl 1:S159-S172 (publié simultanément dans J Clin Periodontol). DOI
Related treatments

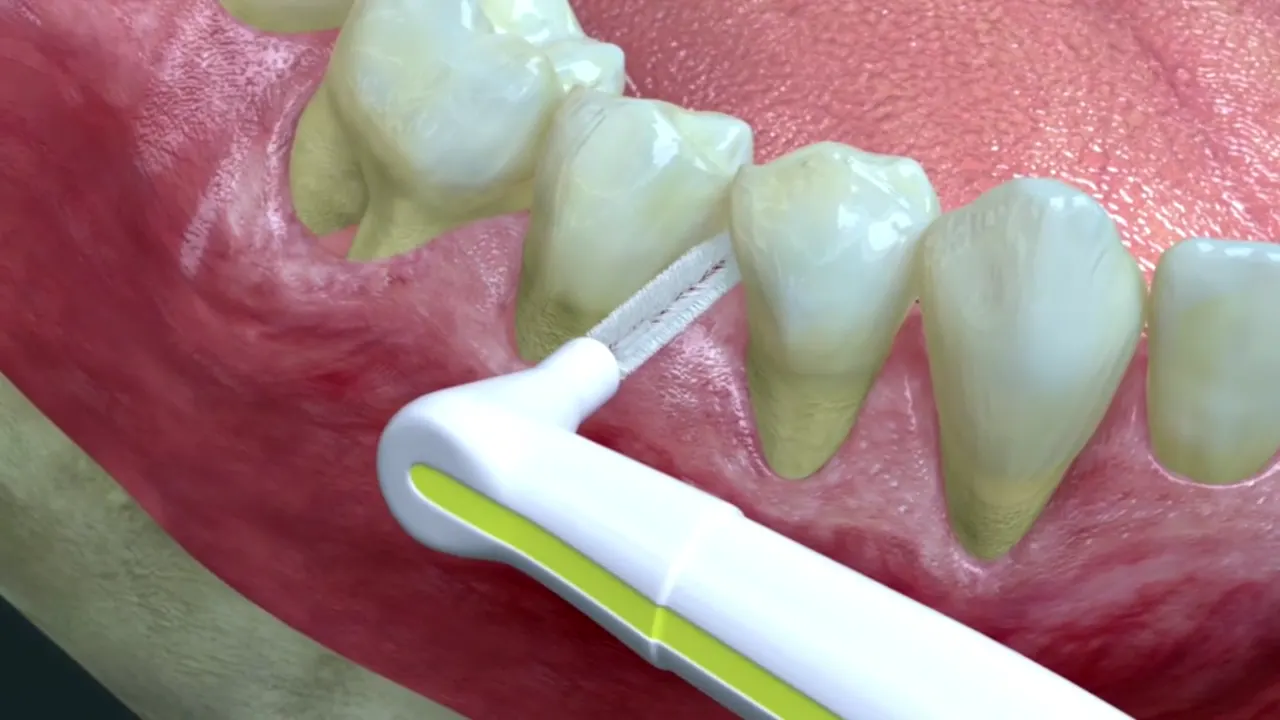
How periodontitis is treated: from assessment to stability
Treating periodontitis is not a “deep clean”. Here is the pathway as Dr Hazout practises it in Levallois-Perret: the assessment, full-mouth treatment in a single…
Periodontal maintenance: keeping results over time
Once the pockets have been treated, treatment is not over: it changes pace. Maintenance, or supportive periodontal care, serves to detect any return of the disease early…
Read next
Gum care around implants: preventing peri-implant mucositis and peri-implantitis
An implant cannot decay. But the gum and bone around it can become inflamed and break down, sometimes faster than around a tooth. The two diseases involved, peri-implant…
How to choose a periodontist
Bleeding gums, receding gums, periodontitis diagnosed by your dentist: the time comes to see a practitioner who focuses on the gums. How do you find your way? Rather…
Diabetes and periodontitis: a two-way link, with the figures
Diabetes raises the risk of periodontitis; periodontitis, in turn, makes blood sugar harder to control. No relationship between the mouth and a general disease is better…
Patient pathway