









Gum aesthetics: the gum frames the smile
A balanced smile is not only a matter of the shape and colour of the teeth. The gum draws their frame: its height, how even it runs from tooth to tooth, the papillae between the teeth. When that frame is out of balance, correcting the gum may be enough, or may prepare work on the teeth. This page explains what gum aesthetics can correct, in what order, and what it cannot promise.
Contents10 sections
- What are we talking about?
- Health first: what gum aesthetics must not do
- The gummy smile: when too much gum shows
- Uneven gum line, short teeth: harmony before veneers or crowns
- After periodontitis: black triangles and an uneven gum line
- Restorations that respect the gum
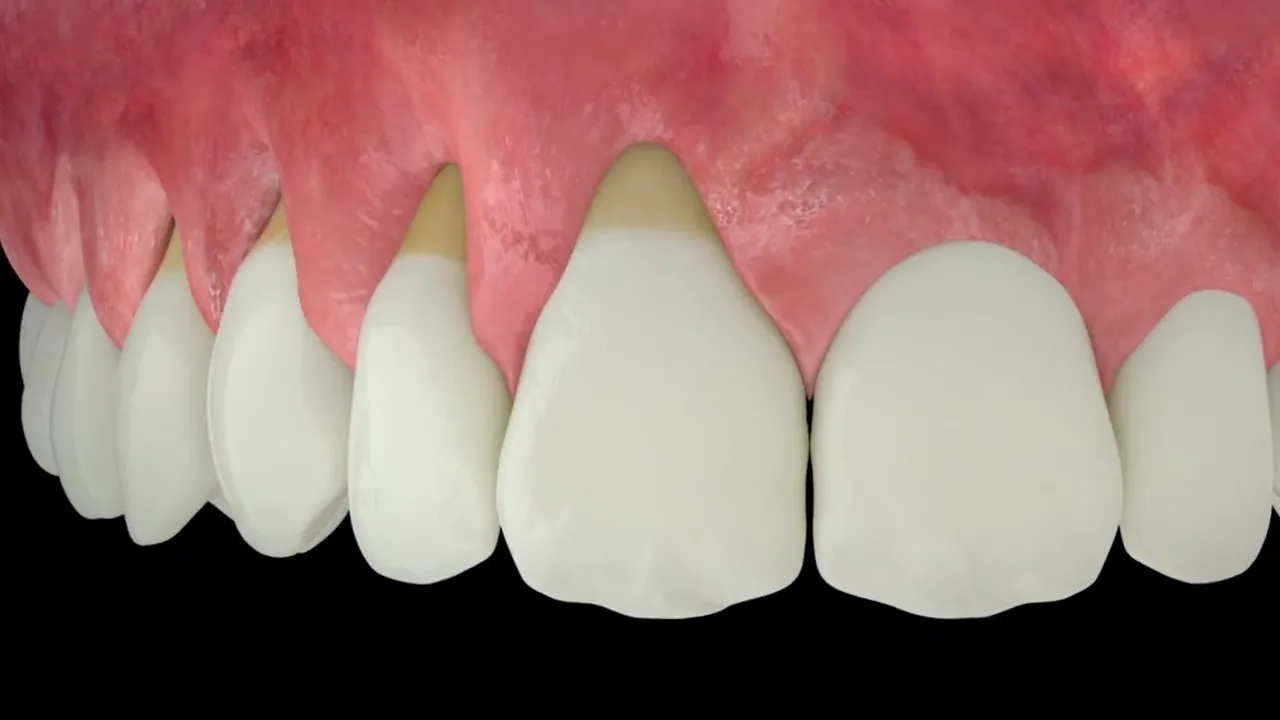
- Gum recession
- Who it is for, and when to hold back
- The analysis before any correction
- Results, limits and follow-up
What are we talking about?
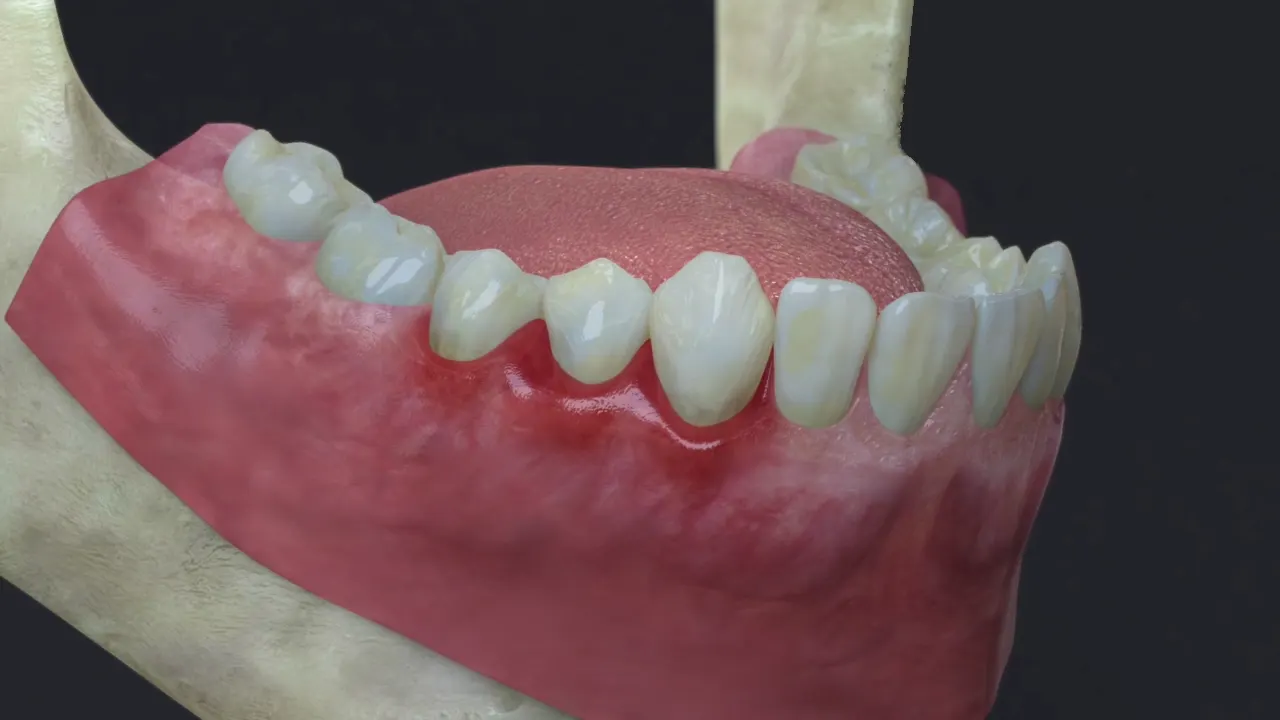
Gum aesthetics brings together the procedures that alter the shape, height or thickness of the gum to serve the appearance of the smile. The medical term is periodontal plastic surgery: minor procedures, under local anaesthetic, that move, remove or add gum tissue. They fall to the periodontist because they involve the tissues that support the tooth, and because their success rests first on the health of those tissues.
Requests fall into five families: too much gum on show when smiling (gummy smile), an uneven or asymmetrical gum line from one tooth to the next, teeth that look short, dark spaces between the teeth after periodontitis ("black triangles"), and gum that has drawn back over a root. Each situation has its cause and its answer; some correct well, others in part, and a few are not a matter of gum at all.
Health first: what gum aesthetics must not do
No aesthetic correction is carried out on inflamed gums. Gingivitis or periodontitis is treated and stabilised first; the gum line often changes after that treatment anyway, as the gum loses its swelling and draws back where bone has gone. Acting before that stage means working on an outline that is about to move, and hiding a disease that carries on beneath a reshaped surface.
So it is on healthy gum, once periodontitis treatment is complete and the gum has settled, that what remains to be harmonised is judged. The same rule holds before veneers or crowns: the edge of a restoration set on inflamed gum keeps the inflammation alive and ends up exposed.
The gummy smile: when too much gum shows
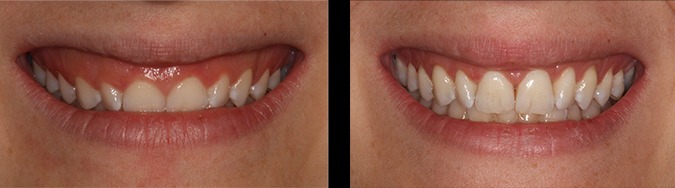
A gummy smile reveals a marked height of gum when smiling. Its causes vary: teeth that look short because the gum did not recede normally after eruption (altered passive eruption), a very mobile or short upper lip, vertical growth of the upper jaw, sometimes gum thickened by inflammation or certain medicines. Treatment depends on the cause, hence the need for a precise examination and X-rays [1].
The examination measures the height of gum revealed when you smile, the length of the visible crowns against their true length, the position of the junction between enamel and root beneath the gum, and the distance between that junction and the bone. This last measurement dictates the procedure: if the bone sits at the right distance, removing the excess gum is enough; if it is too close, the bone must be reshaped as well, or the gum returns to its former place [1].
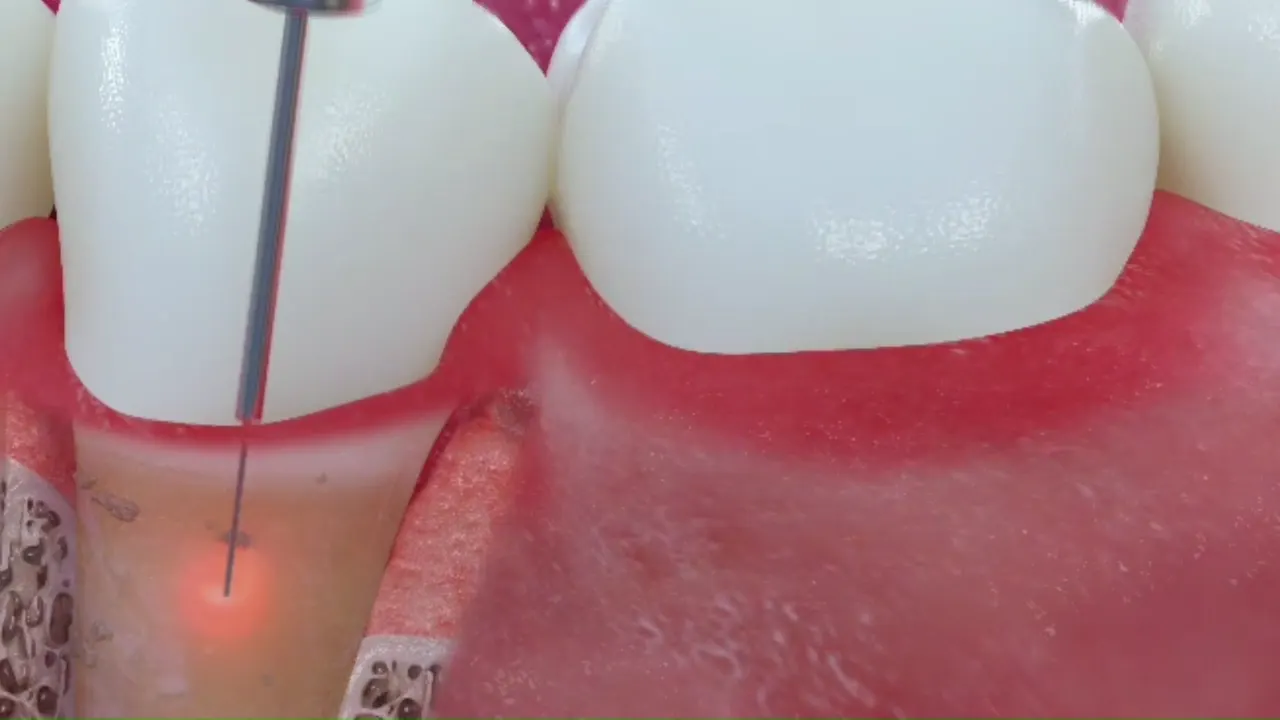
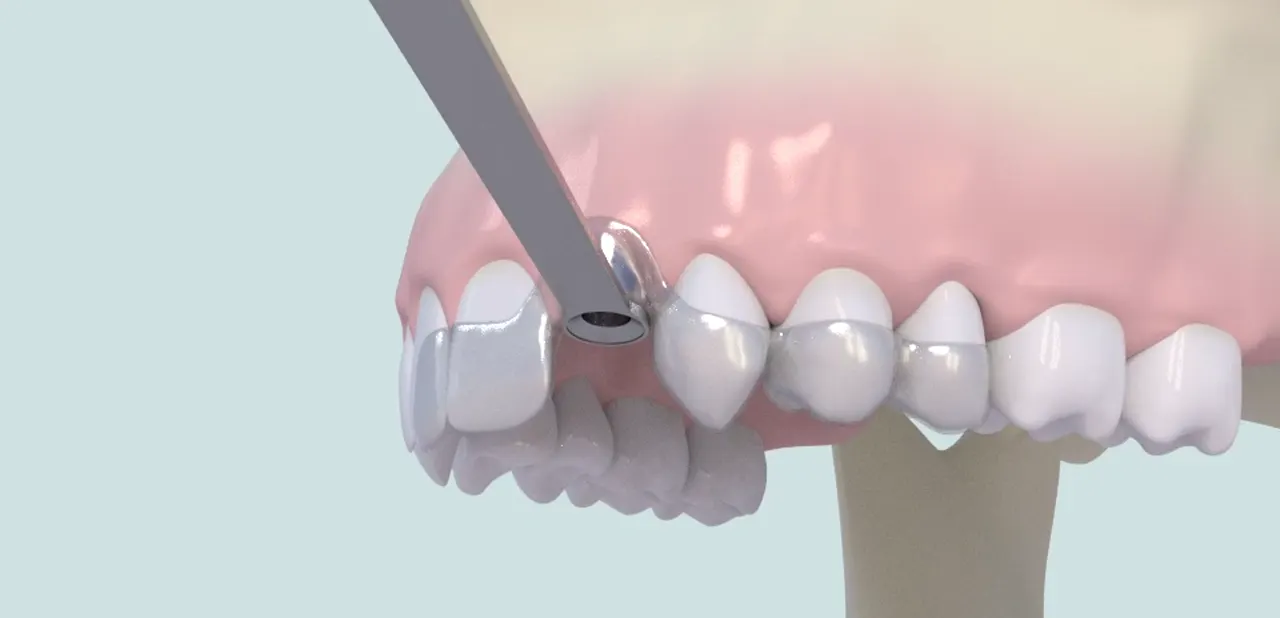
When the gum covers part of the tooth, a gingivectomy removes the excess and a gingivoplasty reshapes the outline: the future gum line is traced, then the tissue is remodelled. At the practice this gum contouring is done with a laser, which cuts the gum precisely and keeps bleeding to a minimum.
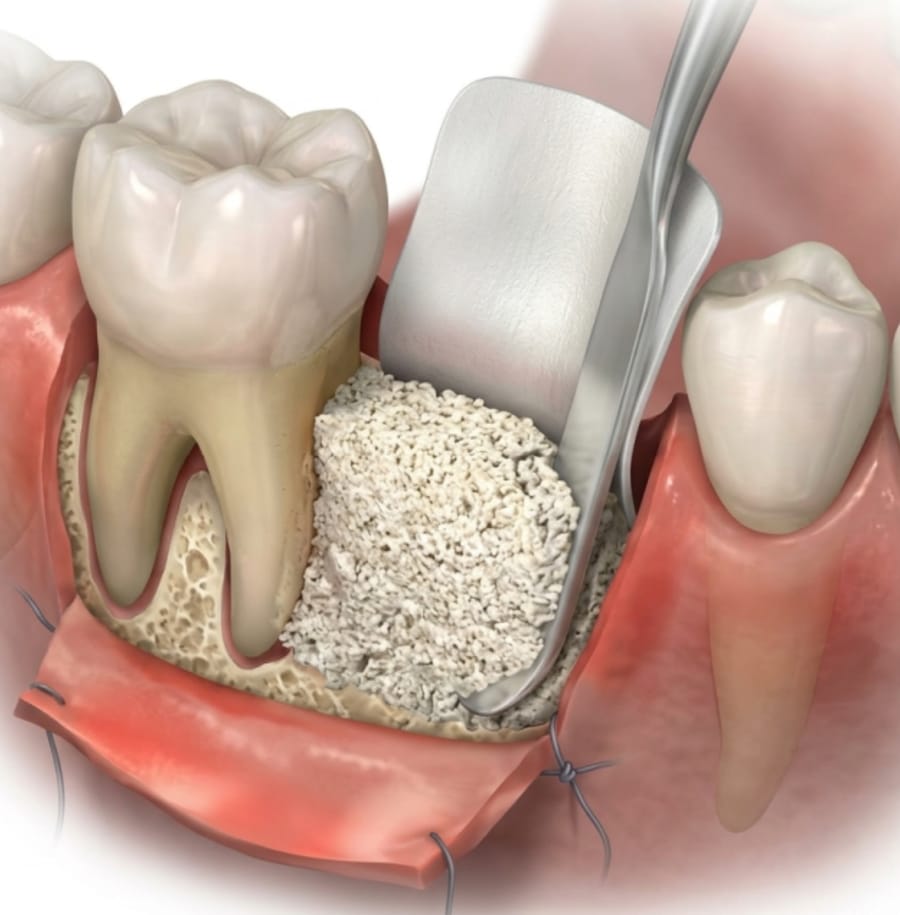
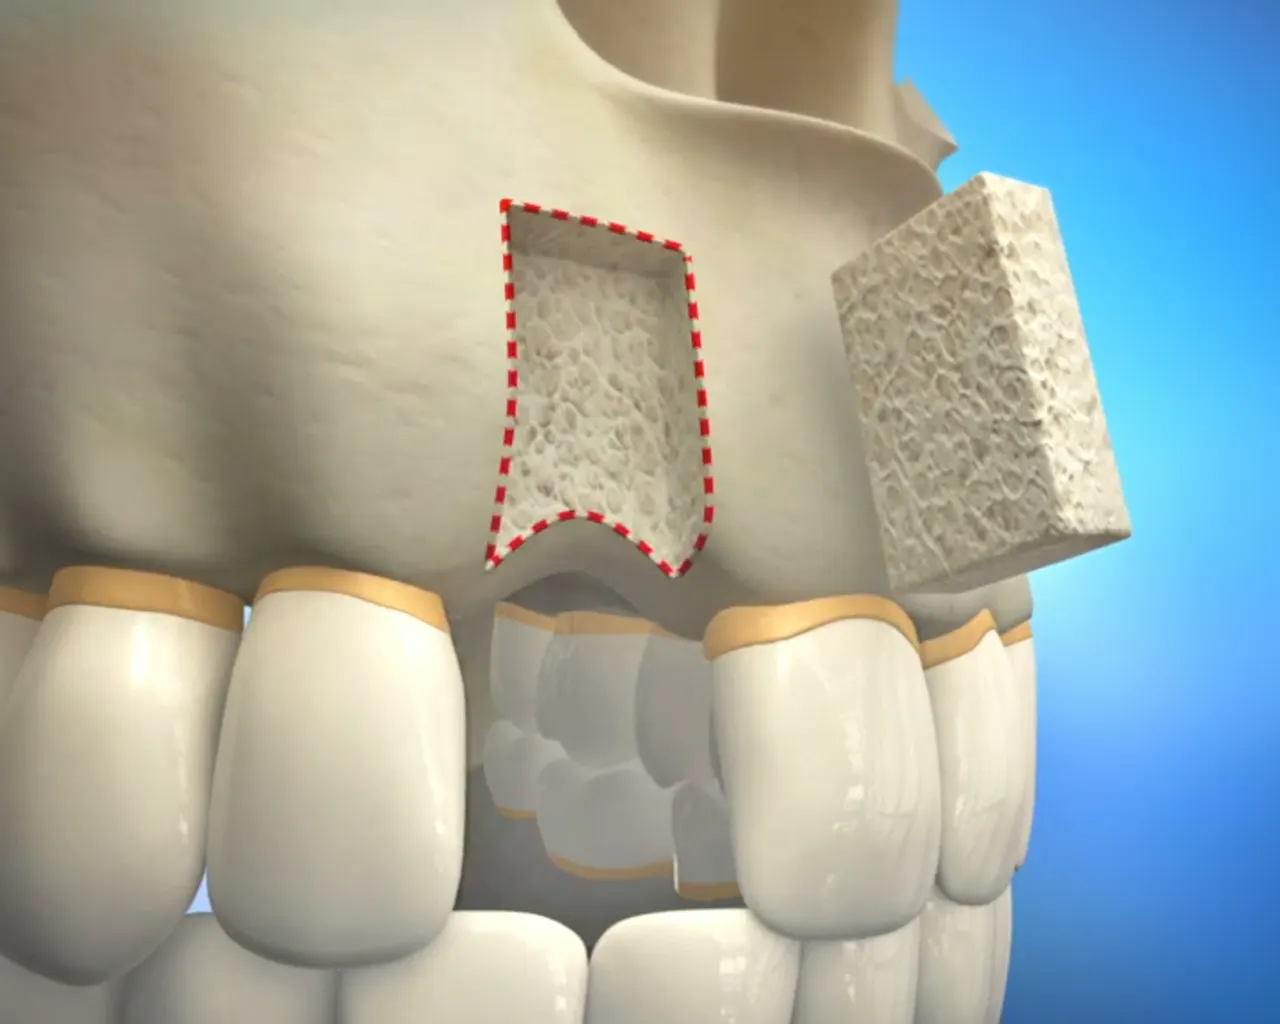
If the underlying bone sits too close to the gum margin, it must be reshaped as well: this is crown lengthening, which uncovers more of the tooth and restores the normal distance between bone and gum margin. Other causes of a gummy smile call for other answers, orthodontic or surgical; a very mobile lip, for instance, is not corrected by removing gum.
Uneven gum line, short teeth: harmony before veneers or crowns
A gum line that changes level from one tooth to the next, or a single tooth shorter than its neighbour, stands out all the more when the teeth themselves are regular. Reshaping tooth by tooth, by gingivectomy or crown lengthening, brings the gum margins back into line. It is planned around the smile line, the lip line and the desired length of the teeth.
Before veneers or crowns on the front teeth, this step is often decisive: the dentist making the restorations needs a stable, symmetrical gum line to design teeth of equal length. Crown lengthening also serves when a tooth is too short to hold a crown. Gum correction comes before the restoration, to let the new outline settle; Dr Hazout coordinates these steps with the restorative dentist.
After periodontitis: black triangles and an uneven gum line
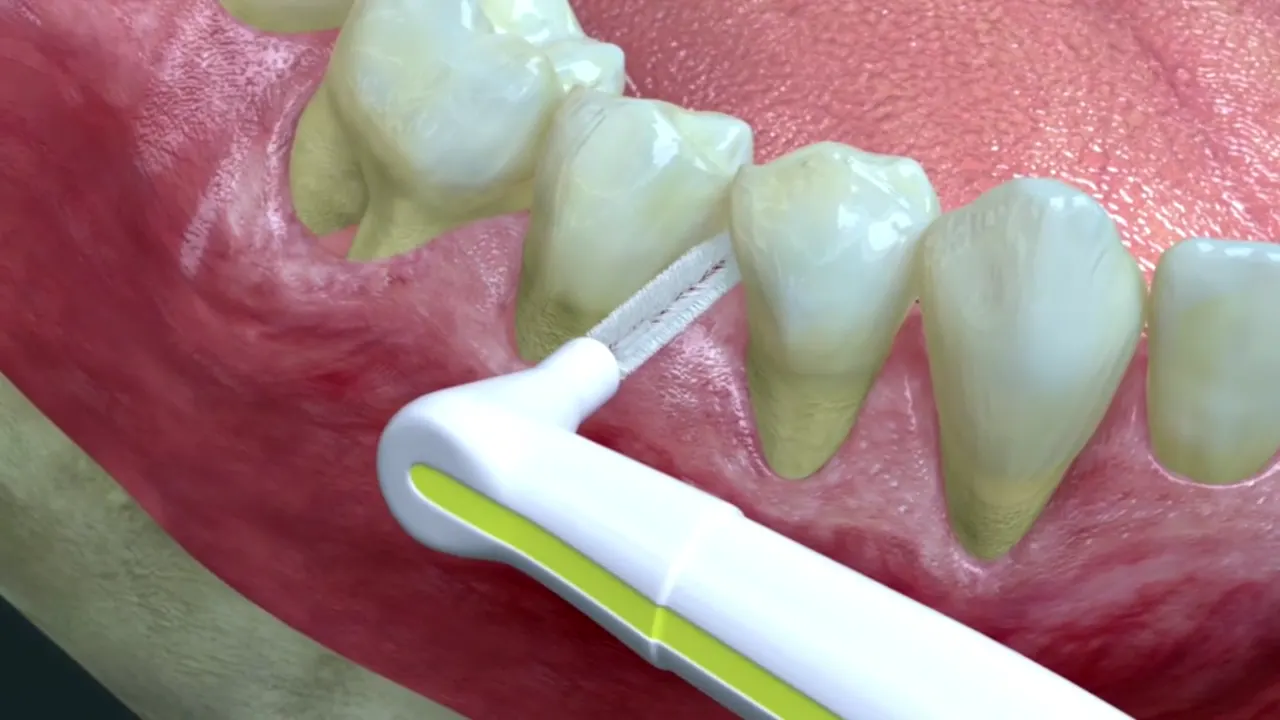
Treated periodontitis often leaves visible traces: the papillae between the teeth have shrunk, dark spaces have opened (black triangles) and the gum line no longer runs level. Whether a papilla is present depends largely on the distance between the contact point of the teeth and the bone: the greater that distance, the more likely the space stays open [2].
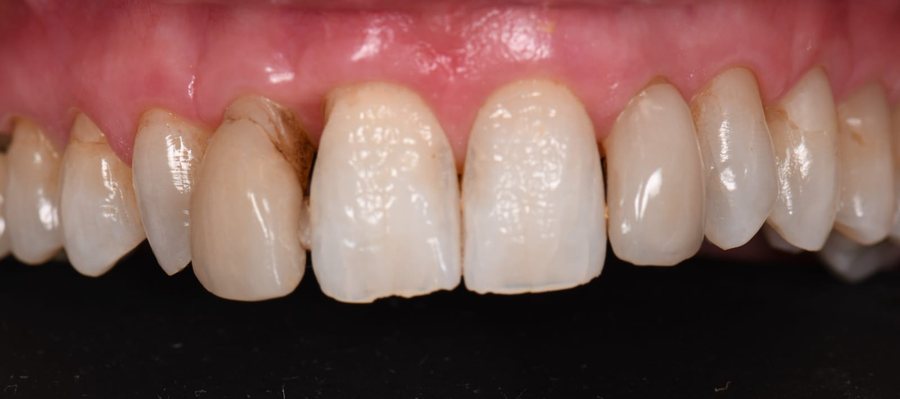
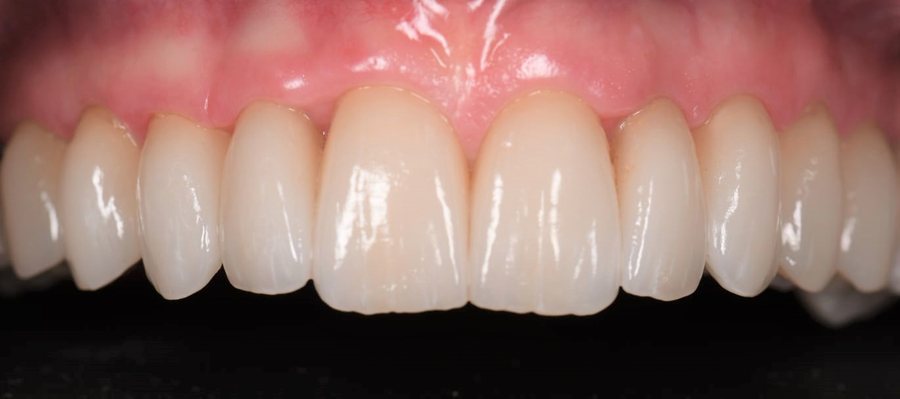
Let us be clear about what is possible. Gum lost between the teeth does not grow back predictably: no graft recreates a papilla where the bone that carried it has gone. Balance is restored by other levers: healthy, stable gums, gum corrections where needed, then a change in the shape of the teeth (veneers, restorations, sometimes orthodontic closure) that closes the spaces by bringing the contact point closer to the gum. The work is coordinated between the periodontist and the dentist who carries out the restorations.
Restorations that respect the gum
The edge of a crown or veneer lives against the gum. Poorly fitted or stained, it traps plaque, feeds inflammation and underlines the smile with a dark rim. Before front-tooth restorations are redone, the gum is brought back to health; the new edge is then placed and polished so that the gum stays healthy against it.
Gum recession
A receding gum makes the tooth look longer and breaks the regularity of the outline. When the recession is suitable, a gum graft covers the root and thickens the gum. The signs, the criteria for deciding, the techniques and a before/after case are presented on the Gum recession and grafts page.
Who it is for, and when to hold back
These procedures are for patients whose gums are healthy or stabilised, who clean their teeth well and whose expectation matches what the gum can offer. Several situations lead to postponing, or to deciding against treatment:
- active or unreassessed periodontitis: correction waits for stabilisation;
- smoking, which slows healing and spoils the result; stopping is raised;
- insufficient plaque control: a new gum line only stays crisp if it is maintained;
- very thin gum or insufficient bone, which limit what can be removed or reshaped without provoking a recession;
- an expectation that does not depend on the gum: a short lip, teeth whose shape or colour is at issue, black triangles due to major bone loss;
- certain medicines (anticoagulants, drugs acting on bone) or general conditions that require coordination with the treating physician.
The analysis before any correction
It all begins with an analysis visit at the Levallois-Perret practice: photographs of the smile, examination of the gum and X-rays to locate the bone. Dr Hazout shows you what he proposes to correct, and what he does not. When restorations are planned, the plan is drawn up with the dentist who will make them, so that the gum is corrected to suit the teeth to come.
The practical arrangements, the course of treatment and the aftercare instructions are explained at the practice, according to your situation.
Results, limits and follow-up
When the indication is right and the bone has been taken into account, the new outline of a gummy smile or an uneven gum margin holds over time. On the other hand, gum aesthetics does not recreate a lost papilla, does not lengthen a short lip and does not replace orthodontics when it is the teeth that are out of place. The photographs on this page are individual cases; they say nothing about another patient's result.
Follow-up is that of any gum: regular visits, built into periodontal maintenance for patients treated for periodontitis. The aesthetic result then owes as much to daily care as to the initial procedure. The practice's fee ranges are given on the Fees page; a written estimate is provided after the analysis.
Frequently asked questions
Is a gingivectomy permanent?
Yes, when the indication is right: if the bone sits at the right distance from the new gum margin, the outline stays stable. If it is too close, the gum tends to creep back; that is why it is checked before the procedure.
Why a laser?
It allows a precise outline of the new gum line and coagulates as it cuts, which keeps bleeding to a minimum. It does not replace checking the bone level before the procedure.
Can black triangles disappear?
Rarely through the gum alone. When the papilla has gone with the bone that carried it, it does not grow back predictably. The spaces are closed mainly by changing the shape or position of the teeth, once the gum is stable.
Can the gum be corrected after periodontitis?
Yes, once the disease is stabilised and the gum is healthy again. The examination then sets out what can be harmonised and what is better addressed by changing the teeth.
Gingivectomy or gingivoplasty: what is the difference?
Gingivectomy removes excess gum; gingivoplasty reshapes its outline into a regular form. Both are usually combined in a single gum-contouring procedure, done at the practice with a laser, after checking the position of the bone.
How much does a laser gingivectomy cost?
€1,200. The estimate is given after the examination; all fees are on the Fees page.
Scientific sources (2)
- Mele M, Felice P, Sharma P, Mazzotti C, Bellone P, Zucchelli G. Esthetic treatment of altered passive eruption. Periodontol 2000. 2018;77(1):65-83. DOI
- Tarnow DP, Magner AW, Fletcher P. The effect of the distance from the contact point to the crest of bone on the presence or absence of the interproximal dental papilla. J Periodontol. 1992;63(12):995-996. PubMed
Page written by Dr Victor Hazout, periodontist · updated on 11 October 2026
Patient pathway