






Periodontitis, heart and blood vessels: where does the evidence really stand?
People with periodontitis more often have cardiovascular disease: cardiologists and periodontologists recognise this link, found in large studies. This article sets out what these studies show, the direct and indirect pathways linking the gums to the arteries, what periodontal treatment changes, and what to know if you have heart disease.
Key points
- Independent association between severe periodontitis and cardiovascular disease: EFP–World Heart Federation consensus (2020) [1] and American Heart Association statement (2025) [2].
- Pathways under study: direct, through bacteria entering the bloodstream, and indirect, through low-grade inflammation and endothelial dysfunction [3].
- Link found with heart attack, stroke, atrial fibrillation and heart failure, according to the AHA [2].
- Periodontal treatment improves markers: CRP [4], IL-6 and systolic blood pressure [8], endothelial function in one trial [5].
- If you take an anticoagulant or an antiplatelet drug, never stop it without medical advice.
An association recognised by cardiologists
Atherosclerosis is the thickening of artery walls by plaques made of fats and inflammatory cells; it causes most heart attacks and ischaemic strokes. In 2020, a joint workshop of the European Federation of Periodontology and the World Heart Federation concluded that a solid body of evidence supports independent associations between severe periodontitis and cardiovascular disease [1]. 'Independent' means the association persists once shared factors such as smoking, age or diabetes are taken into account, as far as the studies were able to measure them.
In December 2025, the American Heart Association (AHA) published a new scientific statement updating its 2012 statement. It confirms the association with heart attack, stroke, atrial fibrillation and heart failure, and underlines the weight of shared risk factors [2]. The term used is association: a link found by studies, whether direct or indirect.
By which routes might the gums reach the arteries?
- Direct pathway: bacteria from the pockets, including Porphyromonas gingivalis, reach the bloodstream; they have been found in atheromatous plaques and can invade cells of the vessel wall [3] [2].
- Indirect pathway: periodontitis sustains chronic low-grade inflammation, with raised CRP, IL-6 and TNF-α [2].
- Endothelial dysfunction: the endothelium, the layer of cells lining the inside of blood vessels, governs their dilation; its impairment is an early stage of atherosclerosis [3].
- Cross-reactive immune responses: antibodies against periodontal bacteria might also recognise structures in the vessel wall (molecular mimicry) [2].
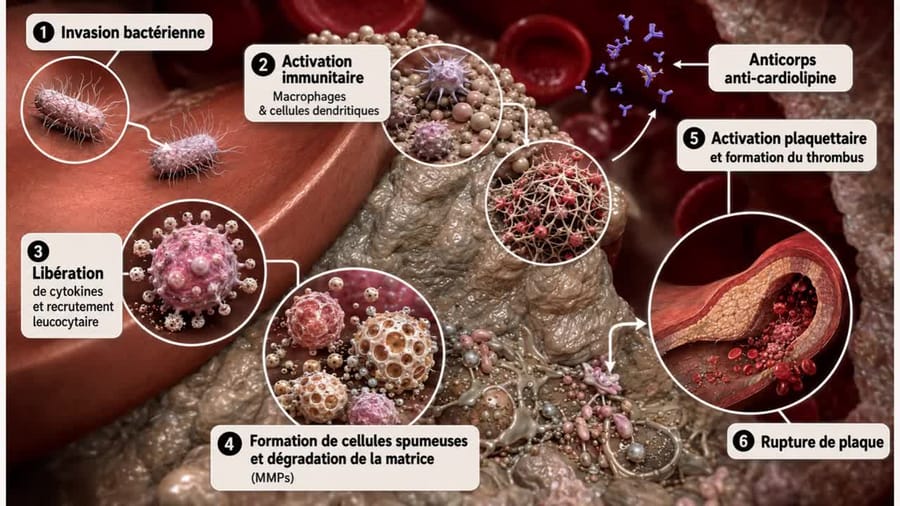
These mechanisms are documented in the laboratory, in animals and, for several of them, in humans: periodontal bacteria found in atheromatous plaques, higher markers of inflammation [3] [2]. They explain why cardiologists and periodontologists take this link seriously.
Direct and indirect links: what the studies show
Part of the link is indirect: smoking, diabetes and excess weight favour both periodontitis and cardiovascular disease, which are therefore often found in the same people [2]. The association is not explained by these factors alone: it persists once they are taken into account [1], and genetic studies known as Mendelian randomisation find a signal for some strokes of cardiac origin [7].
The AHA calls for further longitudinal studies and randomised trials [2]. To measure an effect on the number of heart attacks, several thousand people would have to be followed for years with one group denied full periodontal treatment, which raises an ethical problem since periodontitis needs treating in its own right. Trials therefore follow markers that are easier to measure: blood-vessel function, CRP, blood pressure.
The link also runs the other way: some general diseases, or their treatments, may favour periodontitis.
What periodontal treatment really changes
On markers, the results are broadly favourable:
- In 2007, a randomised trial published in the New England Journal of Medicine (120 patients with severe periodontitis) showed that intensive treatment temporarily worsens endothelial function the next day, then clearly improves it at 60 and 180 days compared with usual care [5].
- A meta-analysis of 26 randomised trials measures an average fall in CRP of 0.69 mg/L six months after treatment [4].
- Another meta-analysis finds a fall in IL-6 and systolic blood pressure, with moderate certainty [8].
On cardiovascular events (heart attack, stroke), trials are still few: the 2022 Cochrane review identified two [6]. Cochrane and the AHA alike call for further trials [6] [2].
If you have cardiovascular disease
- Antithrombotic medicines (anticoagulants, antiplatelet drugs): they are not stopped without the advice of the prescribing doctor. The EFP–WHF consensus devotes part of its recommendations to periodontal treatment in these patients [1].
- Prevention of endocarditis: if you have an artificial heart valve or a history of endocarditis, say so; antibiotic prophylaxis may be required according to cardiology guidelines.
- Coordination: the EFP–WONCA consensus encourages dentists to identify cardiovascular risk factors and refer to the GP [9]. With your consent, a periodontal report goes to your GP or cardiologist.
- Lifestyle: stopping smoking is recommended from the first step of periodontal treatment [10]; it benefits the heart as much as the gums. Diet and weight also count for both (see nutrition and inflammation).
Treatment is described on the periodontitis treatment page; at the practice in Levallois-Perret, it is offered because it treats the mouth, not as a treatment for the heart. Your cardiology follow-up, your medicines and control of blood pressure, cholesterol and smoking remain the measures with proven benefit for the heart. Once periodontitis is stabilised, periodontal maintenance keeps gum inflammation under control: that is the reasonable goal to keep in mind.
Should you worry about your heart if you have periodontitis?
Periodontitis is one of the factors associated with cardiovascular disease that cardiologists recognise [2]. Finding it is an opportunity to review the major risk factors (smoking, high blood pressure, cholesterol, diabetes) with your GP, especially as smokers and people with diabetes are over-represented among periodontal patients [9].
Periodontitis alone does not call for a cardiac work-up. There is every reason, however, to treat it for the sake of your teeth and not to leave a blood pressure or blood sugar unmeasured. The overview of the links between periodontitis and general health places this link among the others, with the same rigour.
Frequently asked questions
Is periodontitis a cardiovascular risk factor like smoking?
It is independently associated with cardiovascular disease: cardiologists describe it as an associated factor. Smoking, high blood pressure and cholesterol remain the risk factors to act on first.
Will having my gums treated reduce my risk of a heart attack?
Treatment lowers CRP and IL-6, two markers of inflammation, as well as systolic blood pressure, and it improved blood-vessel function in one trial. Trials that directly measure heart attacks and strokes are still few.
I take an anticoagulant: can I be treated?
Yes, in the vast majority of cases, without interrupting the medicine. Arrangements are adapted with your doctor if needed.
Does periodontal treatment lower cholesterol?
Meta-analyses mainly show a fall in inflammation (CRP, IL-6) and in systolic blood pressure; blood lipids change little after periodontal treatment.
Is treatment risky for the heart?
Intensive treatment causes a temporary inflammatory reaction the next day; in the trial that measured it, blood-vessel function then improved compared with usual care.
Should I have a cardiac work-up because I have periodontitis?
Not for that reason alone. However, if you smoke, are overweight, or have never had your blood pressure and blood sugar measured, it is a good time to discuss this with your GP.
Scientific sources (10)
- Sanz M, Marco del Castillo A, Jepsen S, Gonzalez-Juanatey JR, D'Aiuto F, Bouchard P, et al. Periodontitis and cardiovascular diseases: Consensus report. J Clin Periodontol. 2020;47(3):268-288. DOI
- Tran AH, Zaidi AH, Bolger AF, Del Brutto OH, Hegde R, Patton LL, Rausch J, Zachariah JP ; au nom des comités de l’American Heart Association. Periodontal disease and atherosclerotic cardiovascular disease: a scientific statement from the American Heart Association. Circulation. 2026;153:e73-e88 (publié en ligne le 16 décembre 2025). DOI
- Hajishengallis G, Chavakis T. Local and systemic mechanisms linking periodontal disease and inflammatory comorbidities. Nat Rev Immunol. 2021;21:426-440. DOI
- Luthra S, et al. Treatment of periodontitis and C-reactive protein: A systematic review and meta-analysis of randomized clinical trials. J Clin Periodontol. 2023;50(1):45-60. DOI
- Tonetti MS, D'Aiuto F, Nibali L, Donald A, Storry C, Parkar M, et al. Treatment of periodontitis and endothelial function. N Engl J Med. 2007;356(9):911-920. DOI
- Ye Z, Cao Y, Miao C, Liu W, Dong L, Lv Z, Iheozor-Ejiofor Z, Li C. Periodontal therapy for primary or secondary prevention of cardiovascular disease in people with periodontitis. Cochrane Database Syst Rev. 2022;10(10):CD009197. doi:10.1002/14651858.CD009197.pub5. DOI
- Zhao Y, Zhang C, Chang X, Zhang J, Shu C, Lin C, Hou J. Causal association between periodontitis and systemic diseases: a systematic review and meta-analysis of mendelian randomization studies. BMC Oral Health. 2026;26:383. DOI
- Meng R, Xu J, Fan C, Liao H, Wu Z, Zeng Q. Effect of non-surgical periodontal therapy on risk markers of cardiovascular disease: a systematic review and meta-analysis. BMC Oral Health. 2024;24:692. DOI
- Herrera D, Sanz M, Shapira L, Brotons C, Chapple I, Frese T, et al. Association between periodontal diseases and cardiovascular diseases, diabetes and respiratory diseases: Consensus report of the Joint Workshop by the European Federation of Periodontology (EFP) and the European arm of the World Organization of Family Doctors (WONCA Europe). J Clin Periodontol. 2023;50(6):819-841. DOI
- Sanz M, Herrera D, Kebschull M, Chapple I, Jepsen S, Berglundh T, et al. Treatment of stage I–III periodontitis—The EFP S3 level clinical practice guideline. J Clin Periodontol. 2020;47(Suppl 22):4-60. DOI
Related treatments

How periodontitis is treated: from assessment to stability
Treating periodontitis is not a “deep clean”. Here is the pathway as Dr Hazout practises it in Levallois-Perret: the assessment, full-mouth treatment in a single…
Periodontitis and general health: what the studies really show
Periodontitis is a chronic inflammation of the tissues that support the teeth. Studies link it to many general diseases: diabetes, heart and blood-vessel disease,…
Read next

Periodontitis and Alzheimer's disease: a real association, mechanisms under study
Several large studies, including two cohorts published in 2026, link periodontitis to a higher risk of dementia and Alzheimer's disease, and the bacterium…

Nutrition, micronutrition and periodontal inflammation: what the studies show
Diet weighs on gum inflammation: a handful of randomised trials show as much, over short periods and with modest effects. Whether periodontitis feeds the chronic…
Understanding periodontitis: recognising the signs and how it is diagnosed
Periodontitis is among the most common chronic diseases, and among the least noticed. It advances without pain, and its first signs pass for merely irritated gums:…