









Periodontal regeneration: rebuilding part of the lost support
After initial treatment, a deep pocket may linger where the bone has been hollowed out along a root. In some of these situations, regenerative surgery can rebuild part of the lost bone and attachment, rather than merely cleaning the area. This page explains why these defects form, when periodontal regeneration is indicated and when it is not, with which materials, on what principle, and what the studies allow you to hope for.
Contents8 sections
- Why does bone hollow out along a root?
- When to consider it: the indications
- When regeneration is not indicated
- The materials: membranes, enamel matrix derivative, bone substitutes
- The principle of the procedure
- What the X-rays show
- What results to expect, and what limits?
- What the result depends on, and what follow-up?
Why does bone hollow out along a root?
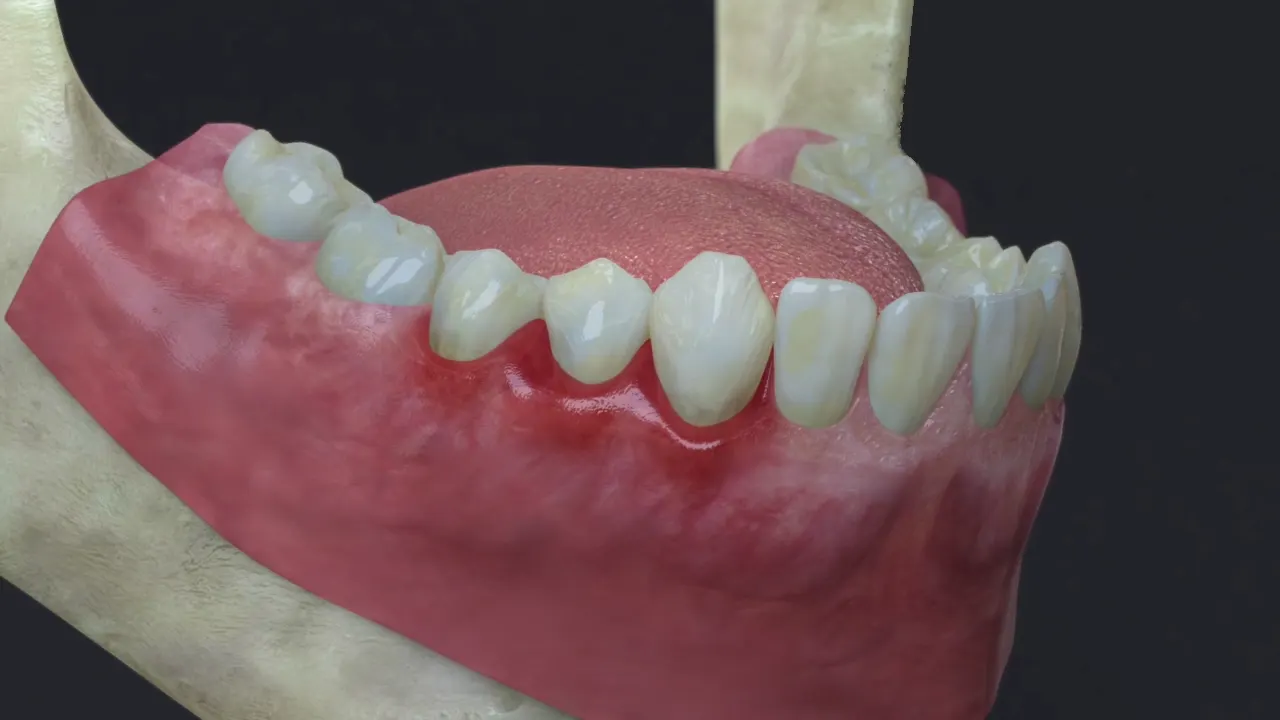
Periodontitis destroys, little by little, the bone and the ligament that hold the tooth (see understanding periodontitis). Most often this loss is horizontal: the bone level drops fairly evenly across several teeth. But destruction can run faster on one side of a root than on the other. The bone then hollows out into a trough along that root: this is an intrabony defect, or vertical defect, at the bottom of which the pocket stays deep despite cleaning.
Several factors favour this pattern of loss: uneven bone thickness around the tooth, an area that is hard to clean (tilted tooth, narrow space, unusual root shape), an overhanging restoration, sometimes excessive load on the tooth. On molars, which have several roots, destruction can reach the space between the roots: this is furcation involvement. That space, beyond the reach of the toothbrush, is among the hardest to clean, and it is one reason why molars are the teeth most often lost to periodontitis.
These defects cannot be seen from the outside. They are picked up at the clinical examination and by X-rays, which reveal the hollowing of the bone along the root or the shadow between the roots of a molar.
When to consider it: the indications
Regeneration does not replace initial treatment: it follows it, at re-evaluation, when a pocket stays deep despite careful cleaning and good hygiene. The 2020 European guideline proposes it for residual pockets associated with an intrabony defect of at least 3 mm, in other words a vertical hollowing of the bone along a root [1].
The shape of the defect matters as much as its depth. A narrow defect enclosed by several bony walls responds well to regeneration; horizontal bone loss spread across a whole arch cannot be rebuilt this way [2]. X-rays and the clinical examination settle the question before the procedure is proposed.
The same guideline retains a second indication: class II furcation involvement (clear destruction between the roots, but not right through the tooth) on lower molars and on the outer surface of upper molars. In these situations, regenerative surgery is preferred to extraction [1]. When the involvement runs through the whole furcation (class III), regeneration is no longer indicated; other options are then discussed: cleaning under the gum, access surgery, separating or removing one root [1].
When regeneration is not indicated
Regeneration is demanding surgery, and its result hinges on precise conditions. It is not proposed, or not straight away, in the following situations:
- horizontal bone loss, however deep: no technique rebuilds it predictably;
- uncontrolled inflammation or insufficient plaque control: regeneration is only considered in gum tissue that is healthy and maintained;
- heavy smoking, which markedly reduces healing and the gain obtained [2]; stopping or cutting down is discussed before the procedure;
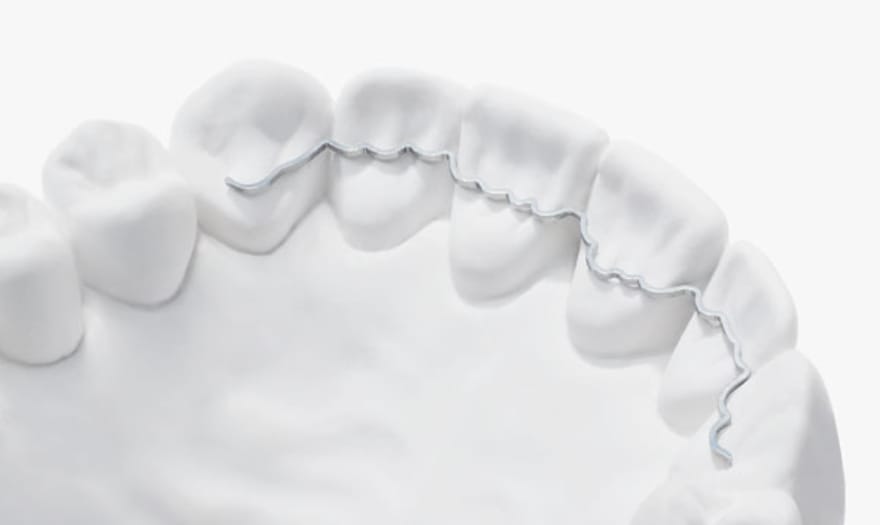
- a very loose tooth that has not been stabilised: a splint may be fitted beforehand;
- a tooth that cannot be kept (fractured root, destruction too extensive, class III furcation with no option): the question then becomes how to replace it, covered on the Implants page;
- certain general conditions or medicines that impair bone healing, to be weighed up with the treating physician.
The materials: membranes, enamel matrix derivative, bone substitutes
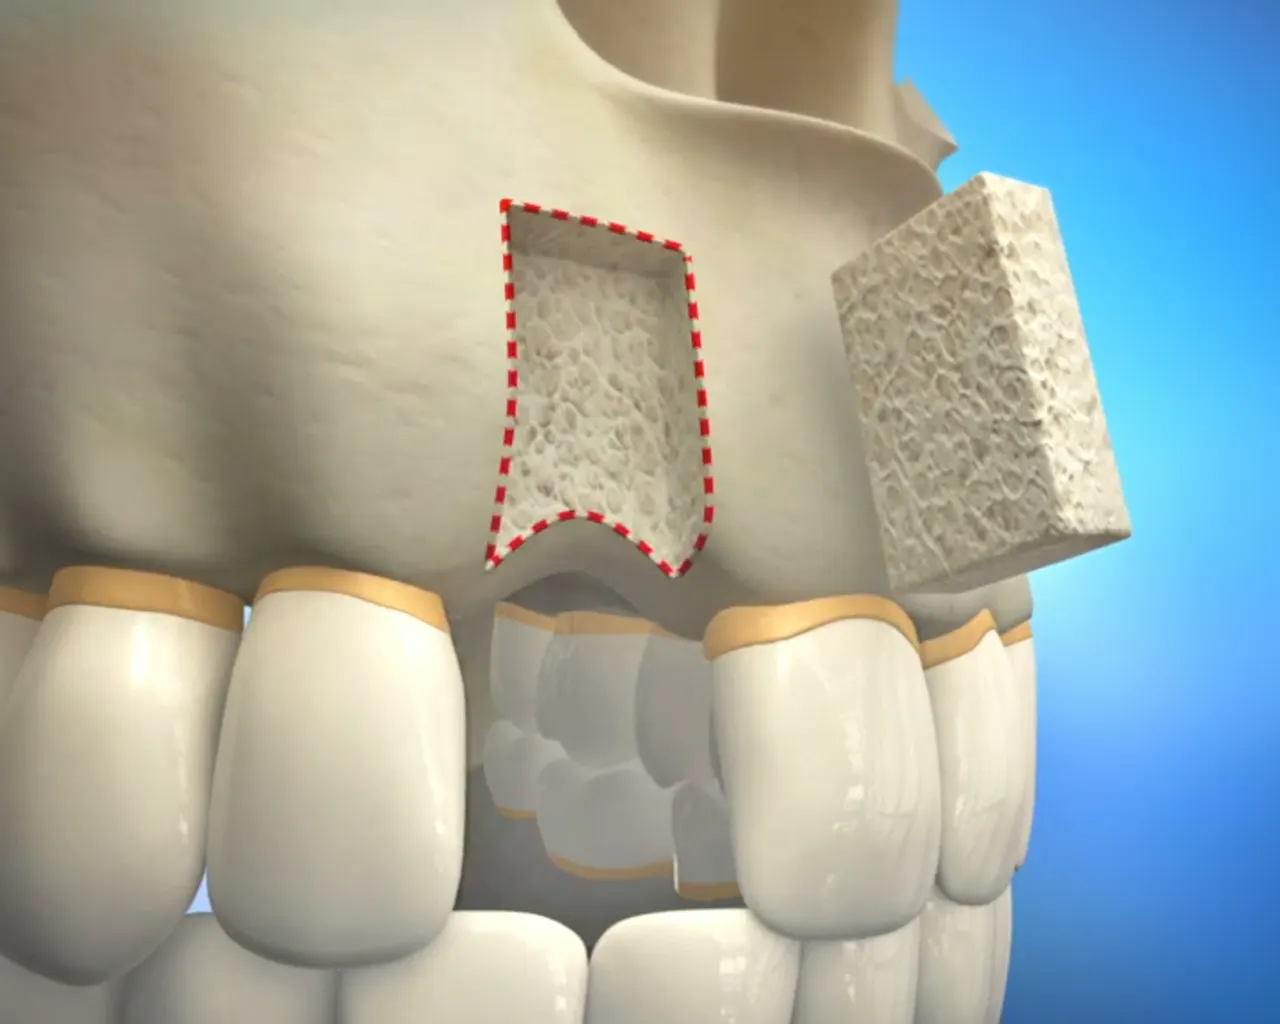
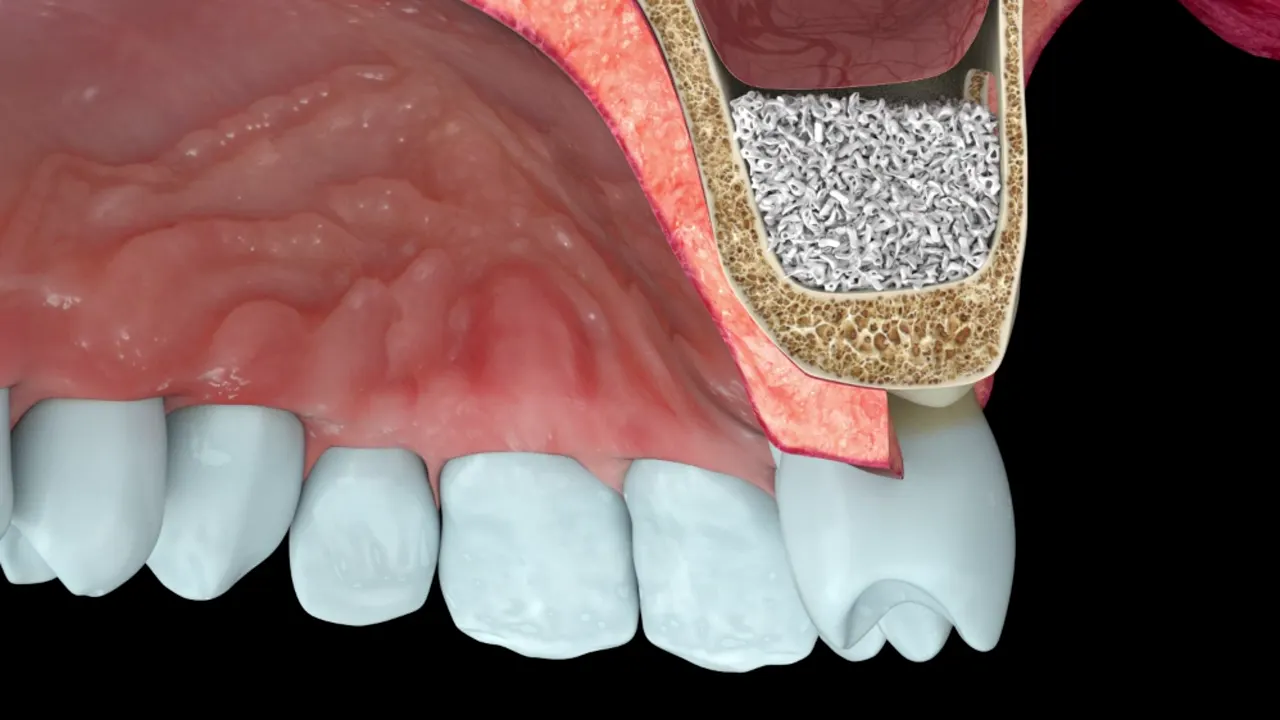
The principle of regeneration is to give the cells of the ligament and bone the time and space to recolonise the defect before the gum, quicker to heal, moves in. Three families of materials serve this end. The membrane, resorbable or not, is a barrier laid over the defect: this is guided tissue regeneration. Enamel matrix derivative is a protein gel applied to the cleaned root, which encourages the formation of a new attachment. Bone substitutes (of animal, human or synthetic origin) fill the defect and support the membrane or the gum.
For intrabony defects, the 2020 European guideline retains the use of either a membrane or enamel matrix derivative, with or without the addition of a bone substitute, and stresses the way the gum is lifted: papilla preservation flaps, which keep the gum between the teeth intact so that the wound closes cleanly over the material [1]. For class II furcations, it retains enamel matrix derivative alone, or a bone substitute with or without a resorbable membrane [1]. The choice between these options depends on the shape of the defect: a wide, poorly contained defect calls for a filler that holds the space, a narrow defect may make do with a protein.
Other products are under study, such as platelet concentrates prepared from the patient's own blood or various growth factors. They are not among the options retained by this guideline; their contribution still belongs to research, and nothing shows that they improve the results of the established materials [1].
The principle of the procedure
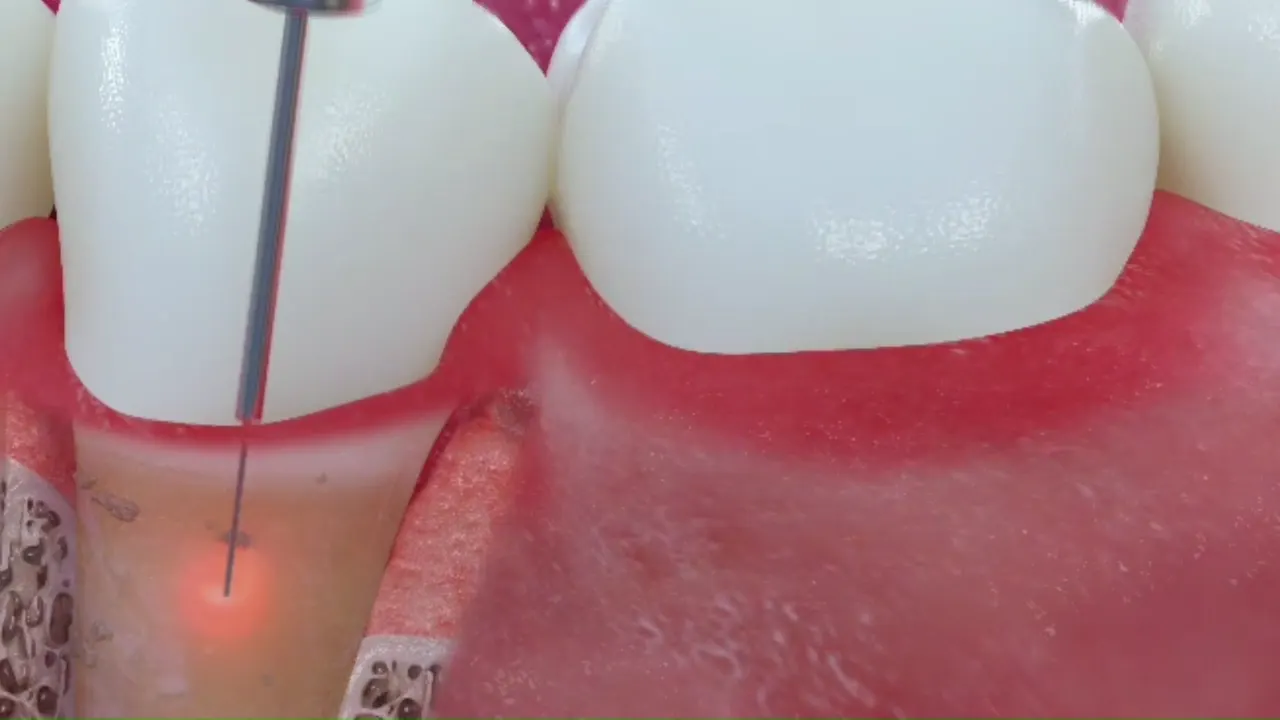
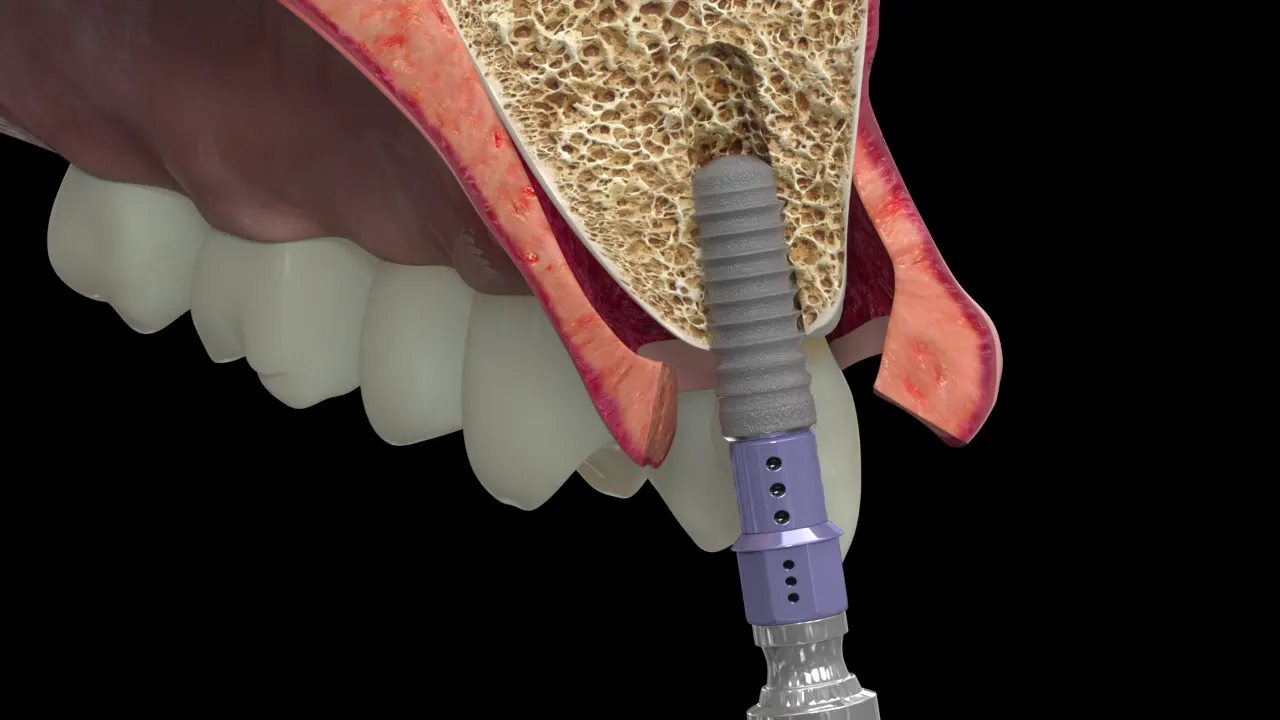
The procedure is carried out by Dr Hazout at the Levallois-Perret practice. The gum is gently lifted to reach the defect, papilla preserved; root and bone are cleaned with care, because no regeneration is possible on a surface that is still contaminated. The defect is then filled with a graft material and protected, depending on the case, by a membrane or by a protein that supports healing of the attachment. Finally the gum is repositioned and sutured over the whole.
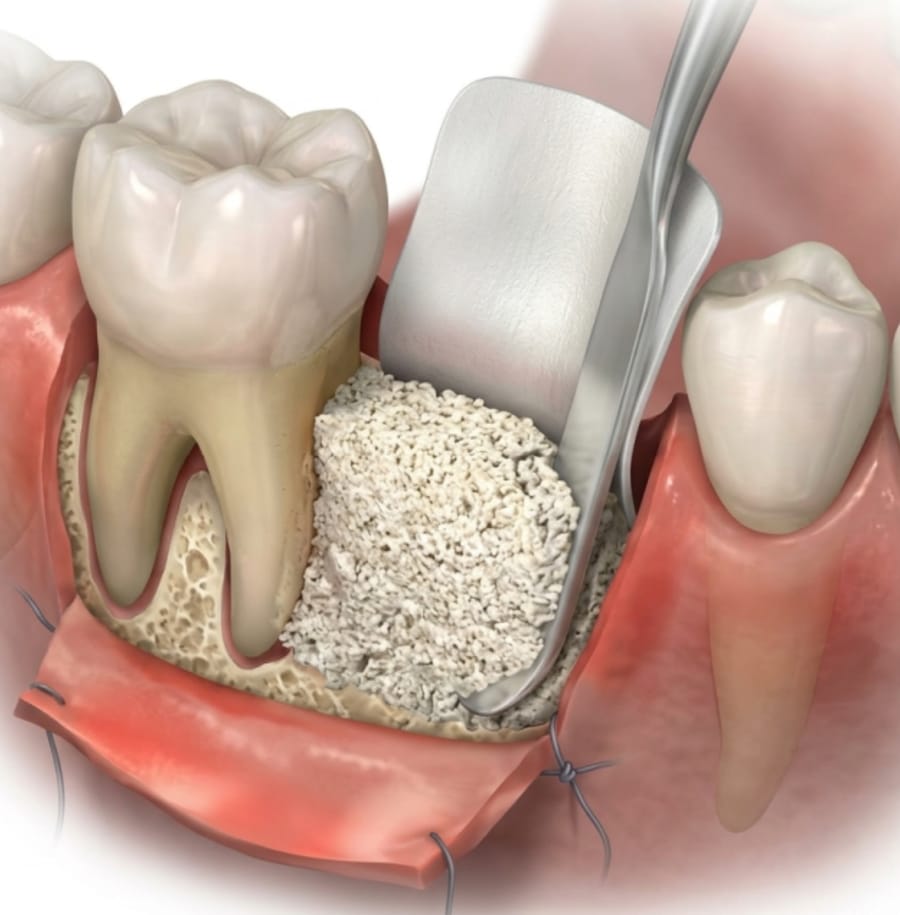
The membrane holds open the space in which bone and attachment must re-form, without the faster-healing gum moving into the defect. Instruments and, where appropriate, a laser do the cleaning; the choice of materials depends on the shape of the defect. Complete closure of the gum over the material is one of the conditions of success: that is what fine sutures and papilla preservation flaps are there to achieve.
The practical arrangements, the course of treatment and aftercare instructions are explained to you at the practice, according to your situation.
What the X-rays show
Bone re-forms slowly, and the result is judged over time. The images below compare the same area before treatment and seven years on.
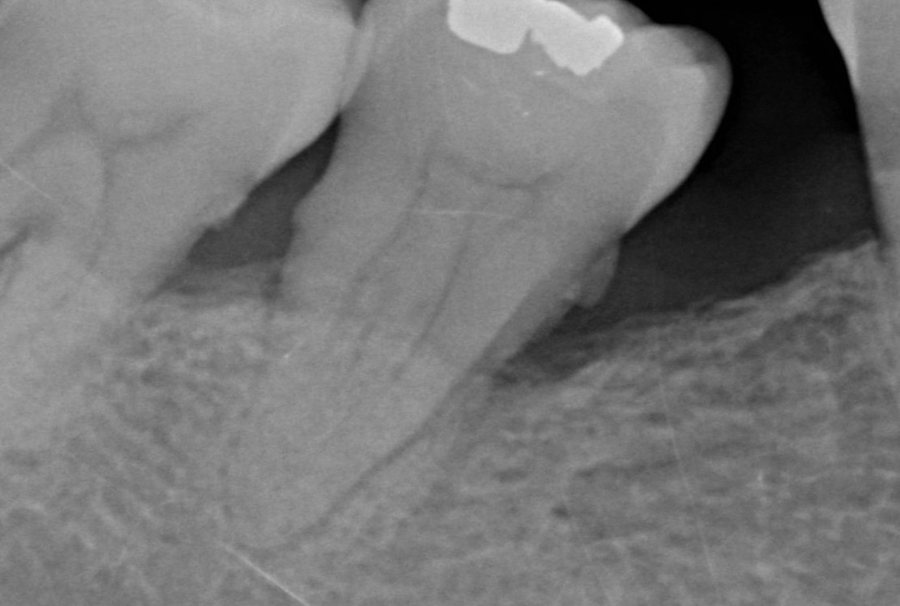
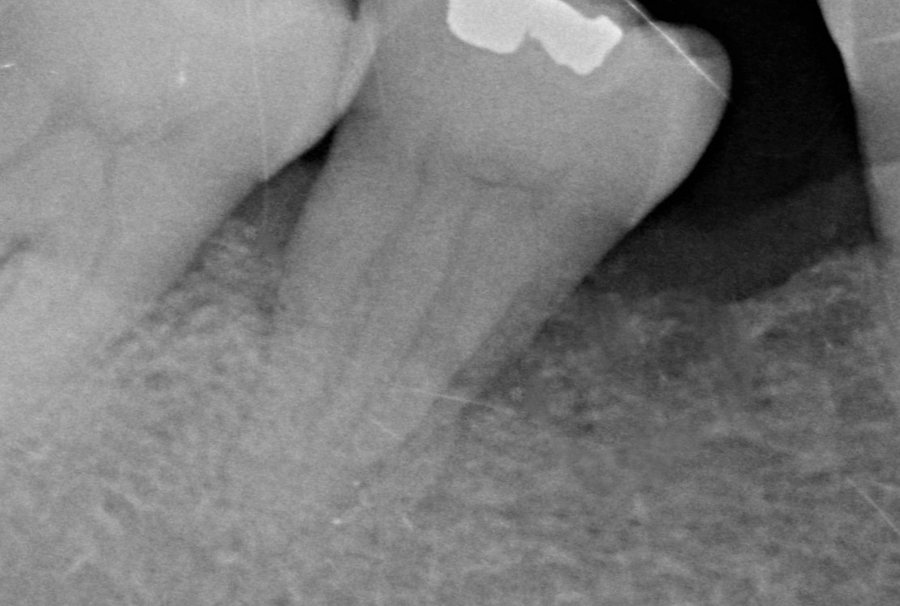
An X-ray shows bone density, not the exact nature of the tissue that has formed: visible fill bears witness to reconstruction, without the image proving an entirely new attachment. What the patient notices is simpler: a pocket that is no longer deep, an area that no longer bleeds and a tooth that holds firmer.
What results to expect, and what limits?
Studies comparing regeneration with access surgery alone show, on average, a greater attachment gain and pocket reduction with regeneration [3]. The 2020 meta-analysis used for the European guideline, drawing on 79 randomised trials, puts this additional attachment gain at about 1.3 mm on average (confidence interval 0.95 to 1.73 mm) compared with surgical cleaning alone, with wide variation from one study to the next and a strength of evidence rated low to moderate [3].
This figure is an average; in a deep, narrow defect the gain can be considerably greater, in a wide, poorly contained defect it can stay small. Regeneration does not restore all of the lost support, and it does not apply to bone lost horizontally. Nor does it ensure that the tooth will be kept for life: that is decided by the stability of the gums in the years that follow.
What the result depends on, and what follow-up?
- Plaque control before and after surgery: regeneration only succeeds in healthy gum tissue.
- Smoking, which markedly holds back healing and the gain obtained [2].
- The shape of the defect and tooth mobility: a loose tooth may be stabilised beforehand.
- Maintenance: regular follow-up visits safeguard the result over time.
Follow-up is that of any treated periodontitis: periodontal maintenance visits at a frequency that depends on your risk, with particular attention to the regenerated area. A patient who gives up maintenance often loses the benefit of regeneration; this is one of the most firmly established limits of this surgery [2].
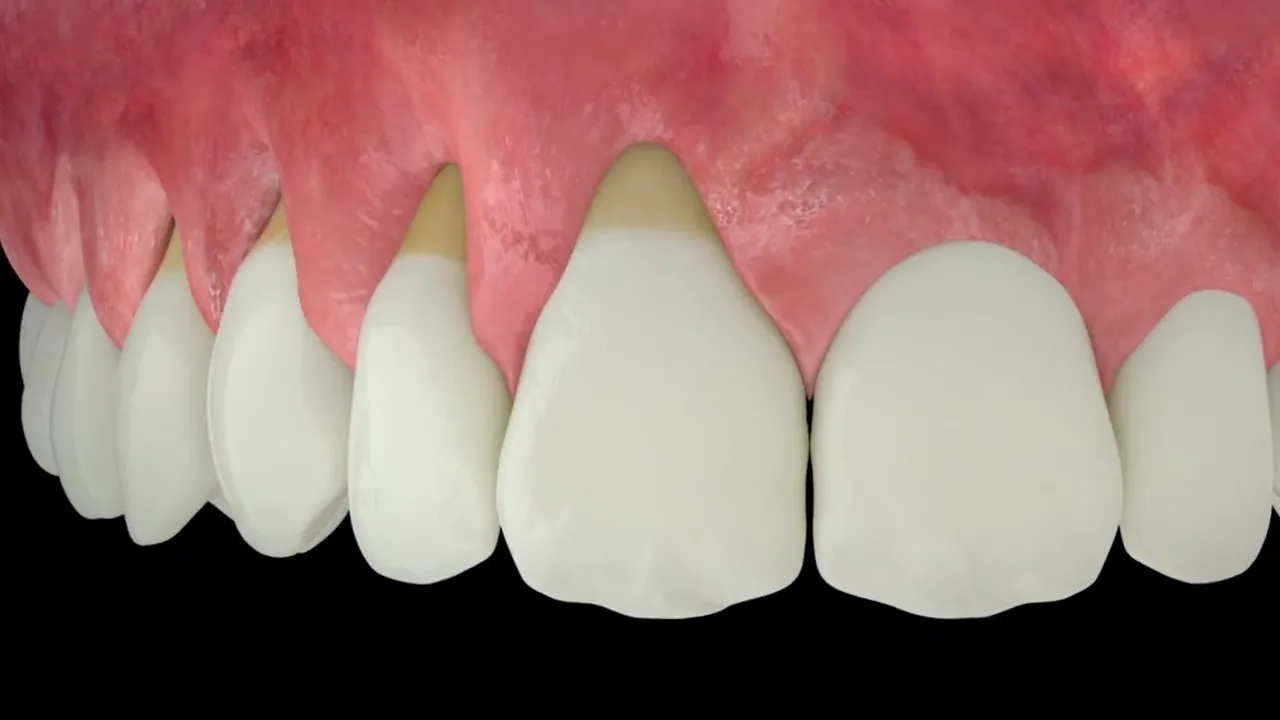
When the defect is not suitable, other options exist: pocket-reduction surgery, or simply closer watch over a stable pocket. They are discussed after re-evaluation, on the Periodontitis treatment page. Gum recessions, which bare the visible surface of the root without a deep bone defect, call for a different approach, that of gum grafts.
Frequently asked questions
Does regeneration make all the lost gum and bone grow back?
No. It rebuilds part of the support in a favourable defect. Bone lost horizontally across all the teeth does not re-form with this technique.
Can regeneration be done around a loose tooth?
Moderate mobility does not rule out the procedure, but a very loose tooth heals less well. It is most often stabilised beforehand with a splint bonded to its neighbours.
What if the tooth cannot be kept?
When destruction is too extensive, regeneration is not proposed and replacing the tooth is discussed, with an implant or another solution. Treating the periodontitis stays essential before any implant is placed.
Scientific sources (3)
- Sanz M, Herrera D, Kebschull M, et al. Treatment of stage I-III periodontitis-The EFP S3 level clinical practice guideline. J Clin Periodontol. 2020;47 Suppl 22:4-60. PubMed
- Cortellini P, Tonetti MS. Clinical concepts for regenerative therapy in intrabony defects. Periodontol 2000. 2015;68(1):282-307. DOI
- Nibali L, Koidou VP, Nieri M, Barbato L, Pagliaro U, Cairo F. Regenerative surgery versus access flap for the treatment of intra-bony periodontal defects: A systematic review and meta-analysis. J Clin Periodontol. 2020;47 Suppl 22:320-351. DOI
Page written by Dr Victor Hazout, periodontist · updated on 11 October 2026
Patient pathway