









Periodontal splinting: stabilising loose teeth
After advanced periodontitis, some teeth stay uncomfortably loose even once the gums are healthy again. A bonded splint ties them together so that chewing is more comfortable. It complements treatment of the disease without standing in for it. This page explains why teeth become loose, how the periodontist assesses them, when a splint is called for, what living with one involves and what it cannot do.
Loose teeth: the signs that bring people to the practice
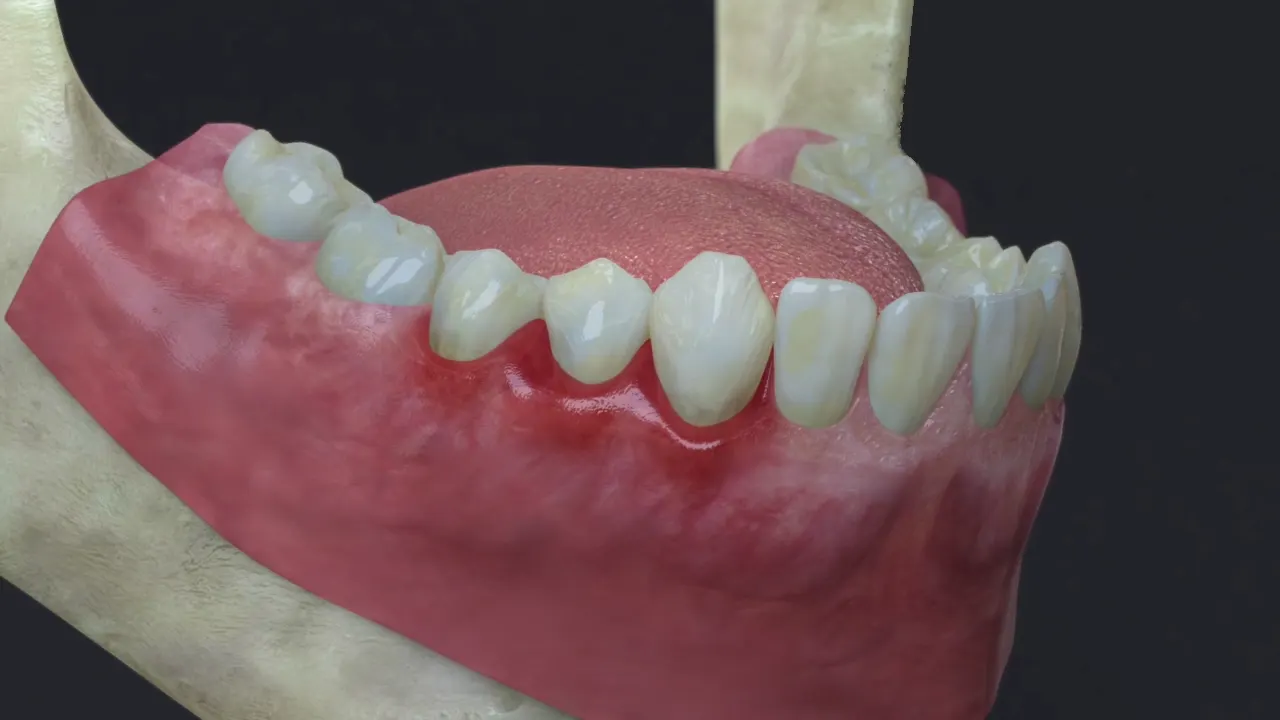
A healthy tooth moves imperceptibly under the finger: its ligament acts as a shock absorber. Mobility becomes a sign the moment it can be felt or seen. Patients describe a tooth that moves when the tongue pushes it, discomfort when chewing (avoiding biting on one side, hard food turning unpleasant), sometimes the feeling that a tooth is "about to fall out".
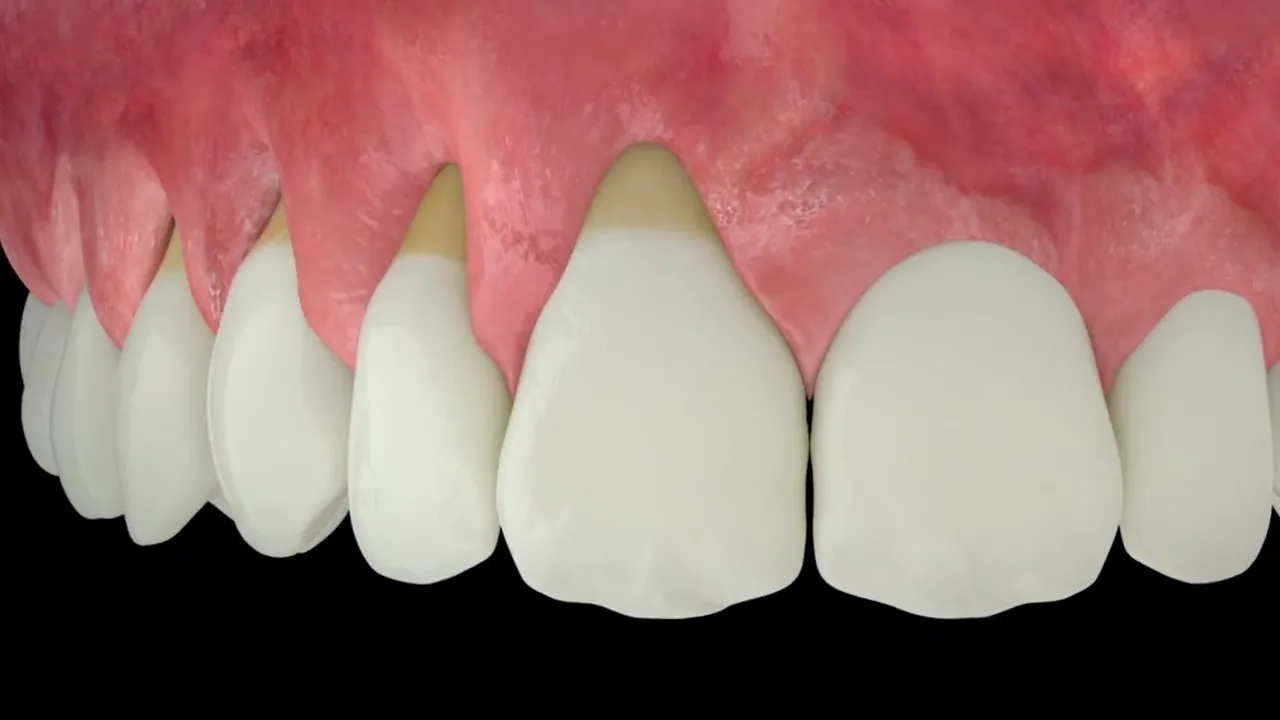
Other signs are more subtle. Front teeth that drift apart, opening a gap that was never there, or that move forward and look longer: this migration is common in advanced periodontitis, because teeth no longer held by enough bone give way to the pressure of the tongue and of chewing. A change in how the teeth meet when the mouth closes, or a tooth that seems "higher" than the rest, stem from the same mechanism.
Mobility that appears out of the blue, with pain or swelling, points more to an abscess or an injury and calls for a prompt visit. Mobility that settles in slowly, on gums that bleed, signals periodontitis that has already destroyed part of the support.
Why teeth become loose
A tooth is held in the bone by the ligament around it. When periodontitis has destroyed part of that bone, the tooth rests on a shortened support and moves more under chewing or tongue pressure. This is the first cause, loss of support. Treatment halts the destruction and often reduces this mobility, but it does not always give back the lost bone height.
The second cause is inflammation itself. An inflamed ligament is swollen and slack; the tooth moves more than bone loss alone would explain. This share of the mobility is reversible: it recedes after treatment, as the gum loses its swelling and the ligament firms up. That is why the decision to fit a splint usually waits for re-evaluation.
The third cause is overload. A tooth that receives forces that are too strong or badly directed, because it stands ahead of the others, because it has lost its neighbours, or because of clenching and grinding at night, moves more even with adequate support. On a tooth with reduced support, this overload keeps the mobility going and can worsen bone loss. Teeth may also drift: they spread apart, move forward or tip, which alters how forces are shared and prolongs the discomfort.
What the periodontist assesses
At Dr Hazout's practice in Levallois-Perret, mobility is measured tooth by tooth, by gently moving the tooth between two instruments. Three levels are usually told apart: slight, barely perceptible mobility; clear but horizontal mobility; and marked mobility in every direction, vertical included. The grade is recorded and compared from one visit to the next: mobility that increases despite treatment does not mean the same thing as stable mobility.
X-rays show how much bone remains around each root and the pattern of the loss. Examining the gums shows whether inflammation is present. Examining how the teeth meet hunts for overload on the loose tooth. Finally, the overall state of the tooth (decay, fractured root, root canal treatment) weighs in the decision: a tooth with a fractured root will not be stabilised by a splint.
Re-evaluation, after periodontal treatment, is when these elements are reviewed. Part of the mobility has gone with the inflammation; what remains comes down to lost support or overload. It is this residual mobility that raises the question of a splint.
The bonded splint
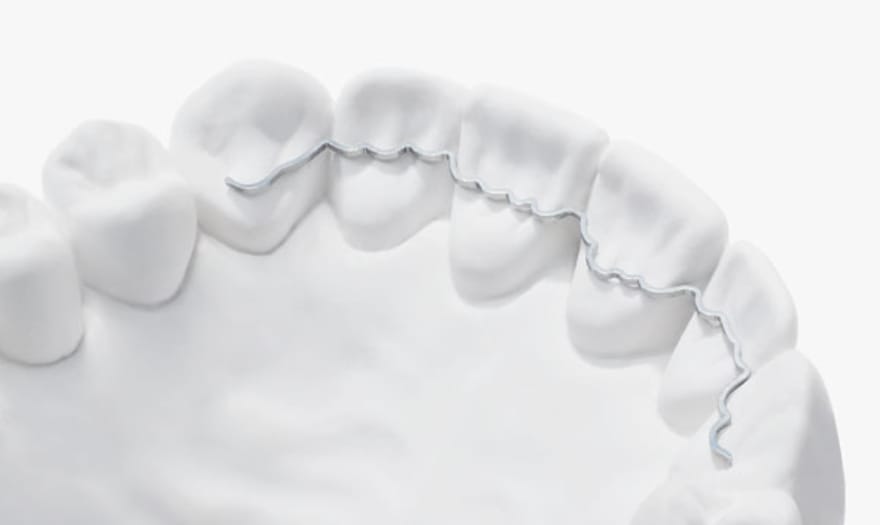
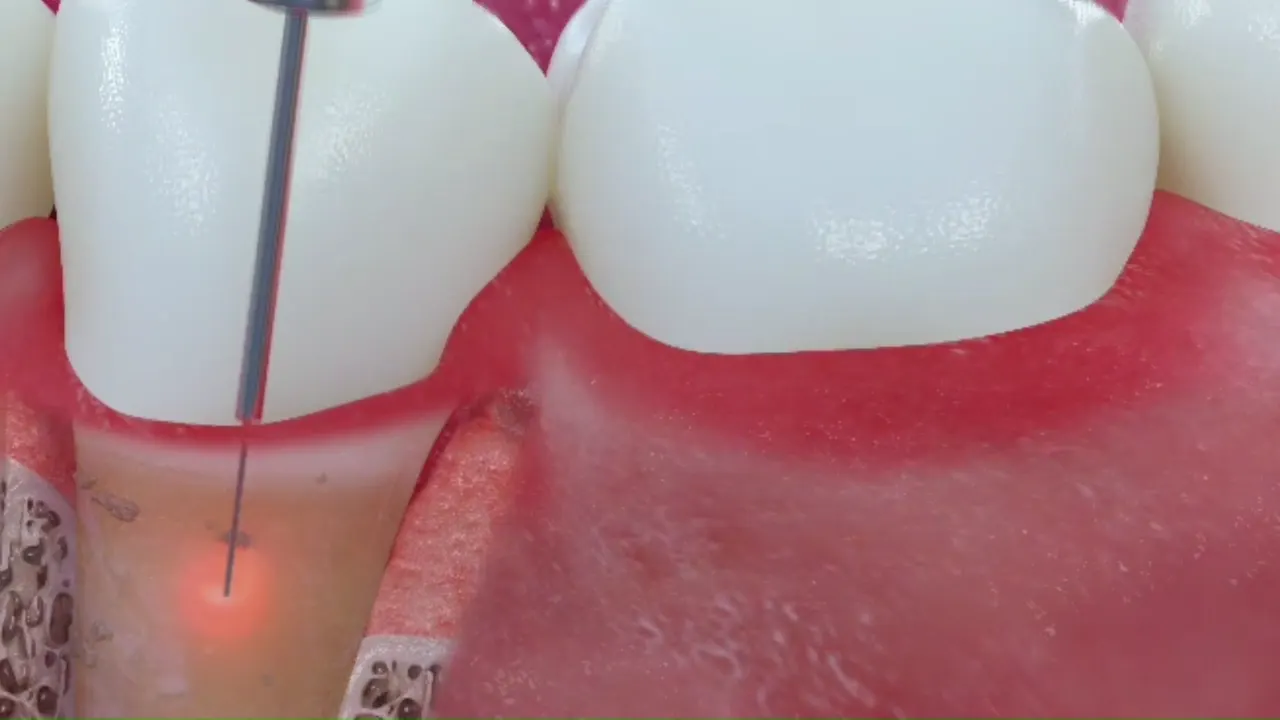
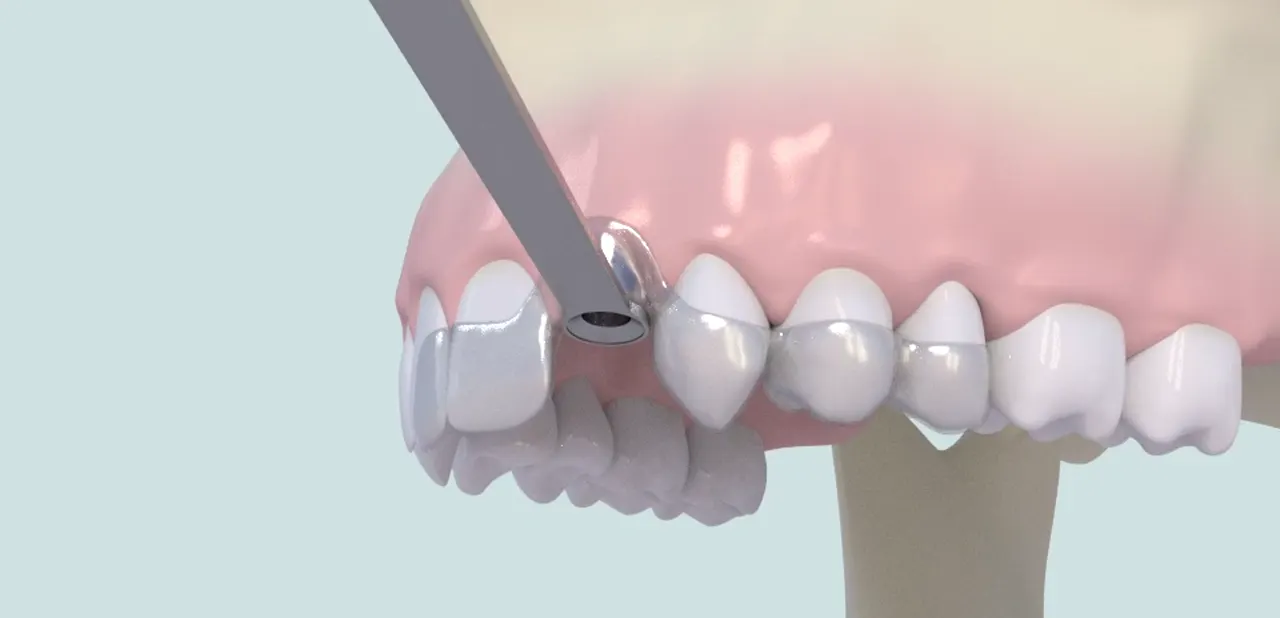
A periodontal splint joins several teeth with a fine wire bonded to their inner surface. Loose teeth lean on their steadier neighbours; chewing forces are spread across the group instead of bearing down on the weakest tooth, and chewing becomes comfortable again. The wire cannot be seen from the front.
A periodontal splint should be told apart from the retainer fitted at the end of orthodontic treatment, which stops moved teeth drifting back to where they started. The principle is the same, the aim differs: here, the point is to give stability back to teeth whose support has shrunk.
The animation, step by step
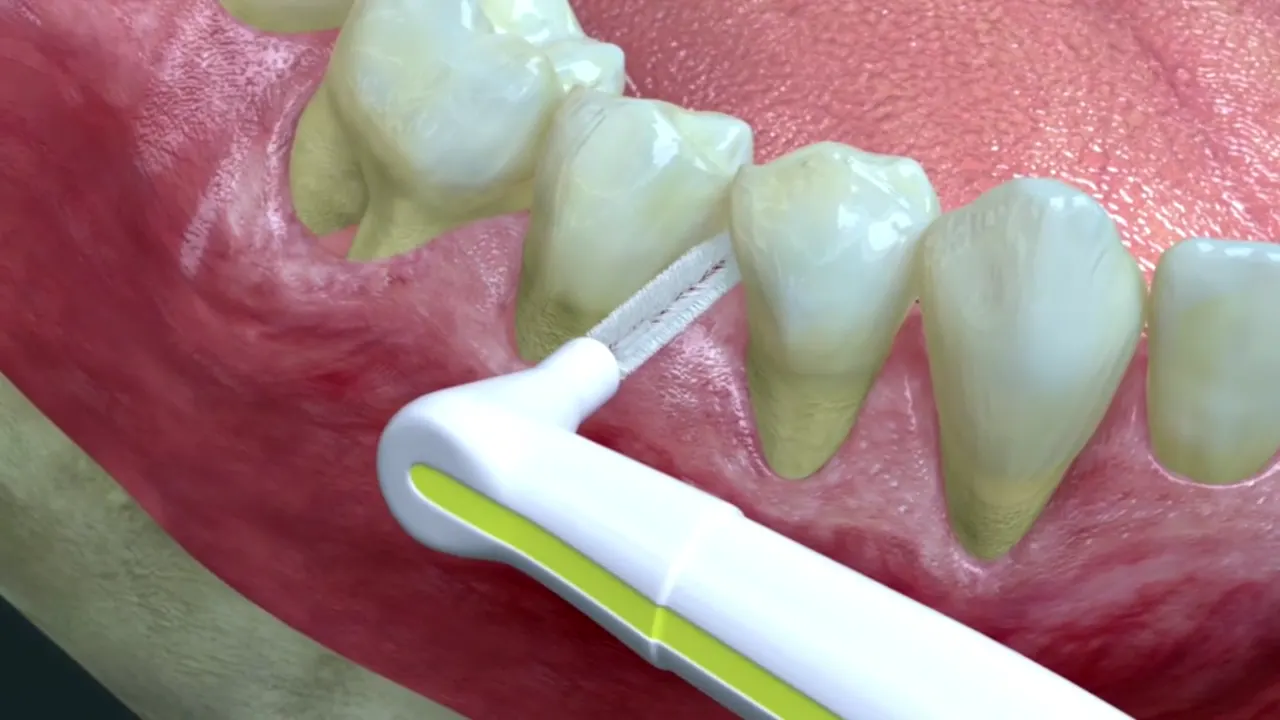
The animation shows three moments. First, a digital impression of the teeth, taken with a camera, used to design a wire that fits their shape exactly. Next, the wire bonded on the tongue side, hugging the outline of each tooth. Finally, a conventional twisted wire held by composite pads, showing where plaque gathers around the pads and along the wire.
This last shot explains why caring for a splint matters as much as fitting it: plaque trapped around the wire keeps the gums inflamed for as long as it is left in place.
Clinical case: a glass-fibre splint that also closes the gaps
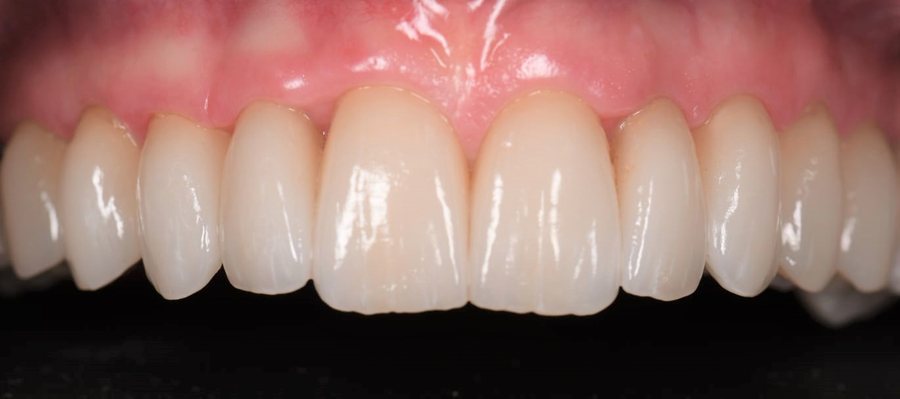
In this practice patient, the lower incisors had become mobile after periodontitis treatment, and small gaps had opened between them. Doctor Hazout chose a glass-fibre splint: a translucent ribbon is applied to the inner surface of the teeth, soaked in composite resin, then light-cured. The same resin, added between the teeth when the splint is placed, closes the gaps that spoiled the smile.
The video shows the steps of the placement, then the result seen from the front: the splint is invisible, and the front teeth once again form a continuous line. Like any splint, it is cleaned every day with interdental brushes and checked at follow-up visits. This outcome is specific to this patient; every situation is different.
When is a splint useful?
A splint does not treat periodontitis. It comes in once inflammation is controlled by periodontal treatment, or temporarily during it, if a tooth is too loose to clean or to chew on comfortably.
The European guideline on the most advanced periodontitis (stage IV) states that temporary splinting of very loose teeth may be considered at every step of treatment, and that long-term splinting may be considered when mobility persists or increases, for the patient's comfort [1]. The recommendation remains open: studies are few [2]. The decision is therefore made case by case.
A splint thus comes into the discussion when:
- residual mobility, after re-evaluation, gets in the way of chewing or brushing;
- mobility increases from one visit to the next even though the gums are healthy;
- a very loose tooth needs protecting during regenerative surgery on itself or on a neighbour;
- teeth have drifted and orthodontic treatment has just moved them back into place.
When teeth have drifted, orthodontic treatment can be considered once the disease is stable; a splint often completes it. Conversely, a tooth whose support is almost entirely gone, fractured or repeatedly infected is not saved by a splint: tying it to its neighbours risks dragging them down with it. Replacing it is then discussed on the Implants page.
The practical arrangements, the course of treatment and the aftercare instructions are explained at the practice, according to your situation.
Living with a splint: hygiene and follow-up
A splint makes cleaning more demanding: the wire closes the gap between the teeth on the tongue side, and plaque gathers around the pads. On teeth whose support is already reduced, this plaque is the chief danger. Daily care is therefore an integral part of the treatment.
Cleaning between the teeth and under the wire is done every day with suitable interdental brushes, where ordinary floss no longer passes. The splint is checked at every maintenance visit, at a frequency that depends on your risk: the mobility of the joined teeth is reassessed, the bonding checked and repaired if needed.
What a splint does not do
A splint does not treat the disease: if inflammation returns, bone keeps being lost beneath a wire that masks the mobility. It does not rebuild lost support; a joined tooth is still a tooth with reduced support, whose prognosis depends on the stability of the gums. Nor does it replace correcting an overload: if a tooth bears excessive forces, adjusting how the teeth meet, or a night guard in case of clenching, is discussed alongside.
Its drawbacks are well known: more demanding hygiene, debonding that needs repair, and the risk, if a tooth with too little support is included, of putting more strain on its neighbours. That is why the decision is made after re-evaluation, tooth by tooth, and why a tooth that cannot be kept is dealt with differently.
Frequently asked questions
Is the splint permanent?
It can be temporary, for the duration of treatment, or stay in place for several years if mobility persists. It is checked and repaired when needed.
Can it be seen?
Not from the front: the wire is bonded to the inner surface of the teeth.
Does it stop me losing the tooth?
It makes the tooth more comfortable, but it is controlling inflammation and maintenance that protect its support.
What if the wire comes loose?
Contact the practice, without waiting for the next maintenance visit.
Does the splint damage the teeth?
It is bonded to the enamel without cutting it, and can be removed without damage. The risk comes not from the wire but from the plaque it holds, if daily cleaning is not adapted.
Scientific sources (2)
- Herrera D, Sanz M, Kebschull M, Jepsen S, Sculean A, Berglundh T, Papapanou PN, Chapple I, Tonetti MS. Treatment of stage IV periodontitis: The EFP S3 level clinical practice guideline. J Clin Periodontol. 2022;49 Suppl 24:4-71. DOI
- Dommisch H, et al. Efficacy of tooth splinting and occlusal adjustment in patients with periodontitis exhibiting masticatory dysfunction: A systematic review. J Clin Periodontol. 2022. DOI
Page written by Dr Victor Hazout, periodontist · updated on 22 October 2026
Patient pathway