









Why plan in 3D before a bone graft and an implant?
A conventional X-ray shows bone from the front, like a cast shadow, and says nothing about its width. Yet width is often what decides: will the implant hold on its own, is a graft needed, and how? Three-dimensional planning settles these questions before the gum is opened. For anyone preparing for a graft or an implant, here is what it brings, and what it does not solve.
Key points
- Cone beam CT measures bone height and width, and locates the nerve in the lower jaw and the sinus.
- Planning starts from the future crown: the implant goes where the tooth demands, and the missing bone is then measured around it.
- The plan reaches the mouth through a surgical guide and, for large reconstructions, a titanium mesh drawn on the same volume.
- Even with a guide, the placed implant deviates from the plan by about 1 to 1.5 mm on average: a 2 mm safety margin remains the rule.
- Its limits: X-ray dose, metal artefacts, accuracy that varies between machines, and a perfect plan is no guarantee of healing.
What cone beam CT reveals, and a panoramic X-ray does not
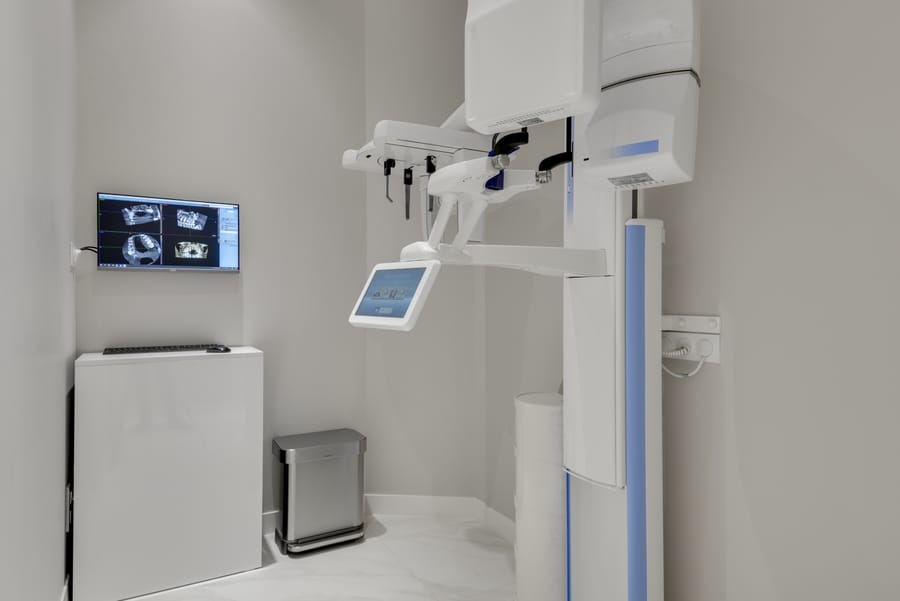
Cone beam CT (CBCT) reconstructs the jaws in three dimensions. The clinician scrolls through slices in every plane, above all cross-sections cut at right angles to the ridge, which show the bone “in section”.
These slices reveal:
- the bone height available, from the top of the ridge to the nerve or sinus;
- the width of the ridge at several levels (wide at the base, it may taper to a knife edge at the top);
- the angle of the ridge relative to the opposing teeth;
- the apparent density of the bone and any lesions (retained root, cyst, infection).
A review of recommendations judges cone beam CT justified for diagnosis, planning and intraoperative transfer in implant dentistry [1]. After an extraction, the ridge loses on average 3.8 mm of width within six months [2]: that very loss, invisible on a panoramic X-ray, is precisely what 3D imaging brings to light.
Two structures to respect: the nerve and the sinus
In the lower jaw, the inferior alveolar nerve runs through a bony canal beneath the roots of the premolars and molars. It is what gives the lower lip and chin their sensation; injuring it risks numbness or abnormal sensations. On the cone beam CT, the canal is identified and traced from end to end, together with its exit (the mental foramen) and any loops.
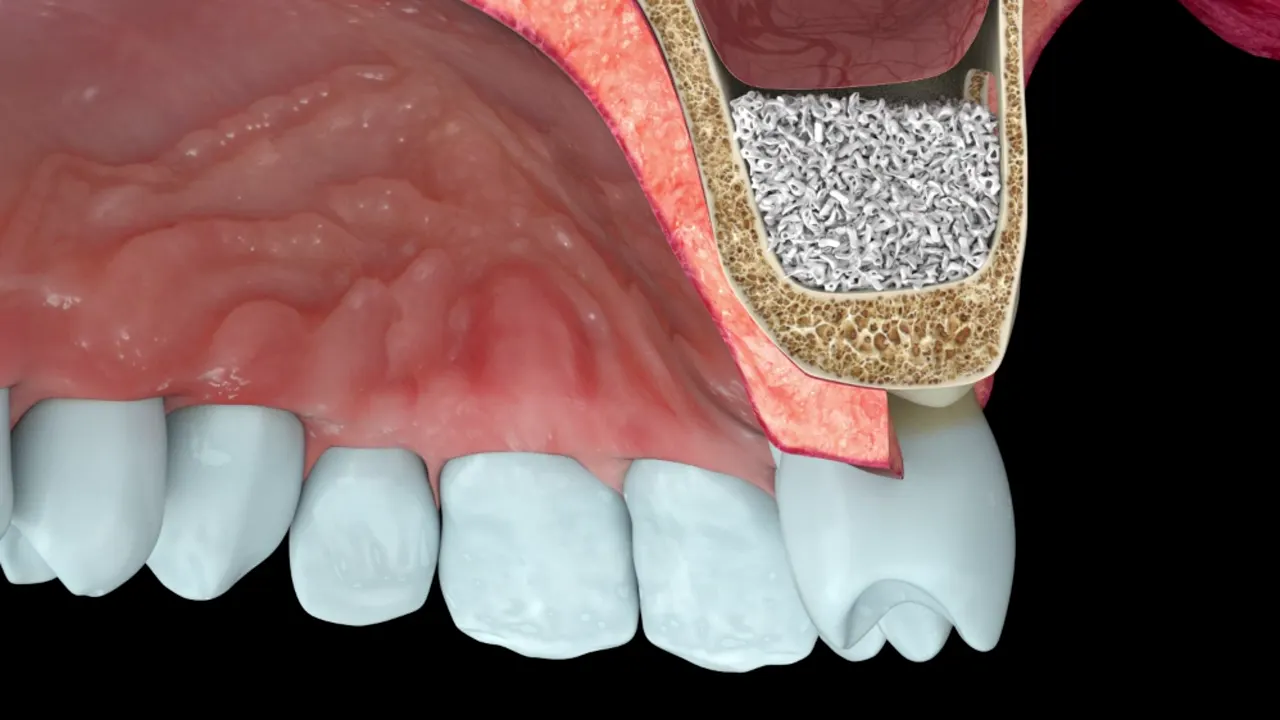
In the upper jaw, the sinus is an air-filled cavity lined with a thin membrane, just above the roots of the molars. Cone beam CT shows the bone height beneath it, the thickness of the membrane, any internal walls (septa) and the state of the sinus lining. All of these point towards a crestal or a lateral sinus lift. During a lateral sinus lift, membrane perforation is the most frequent complication, in 19.5% of cases on average in a systematic review [3]: knowing the anatomy before opening is already a way of anticipating it.
Starting from the tooth, not the bone
For a long time the implant went wherever bone was left, and the crown had to make do, sometimes at the cost of an oblique axis or a neck impossible to clean properly. Prosthetically driven planning reverses the order of decisions, in four steps:
- a digital impression of the teeth (taken with an intraoral scanner) is superimposed on the cone beam CT: visible teeth and invisible bone appear in the same space;
- the future crown is modelled in the place that chewing, appearance and cleaning demand;
- the virtual implant is slipped beneath that crown, along the axis of the chewing forces;
- only then is it checked whether bone surrounds this implant along its whole length. Where it is missing, the volume to rebuild is defined around the implant as it should be, not the other way round.
For a periodontist, this logic counts twice over: an implant well aligned beneath its crown is easier to clean every day. And poor plaque control ranks among the most firmly established risk factors for peri-implantitis [6]. Planning the position is already preparing gum care around the implant.
From plan to mouth: guide and mesh
A plan is only worth something if it is faithfully reproduced in theatre. Two tools build that bridge between the screen and the mouth.
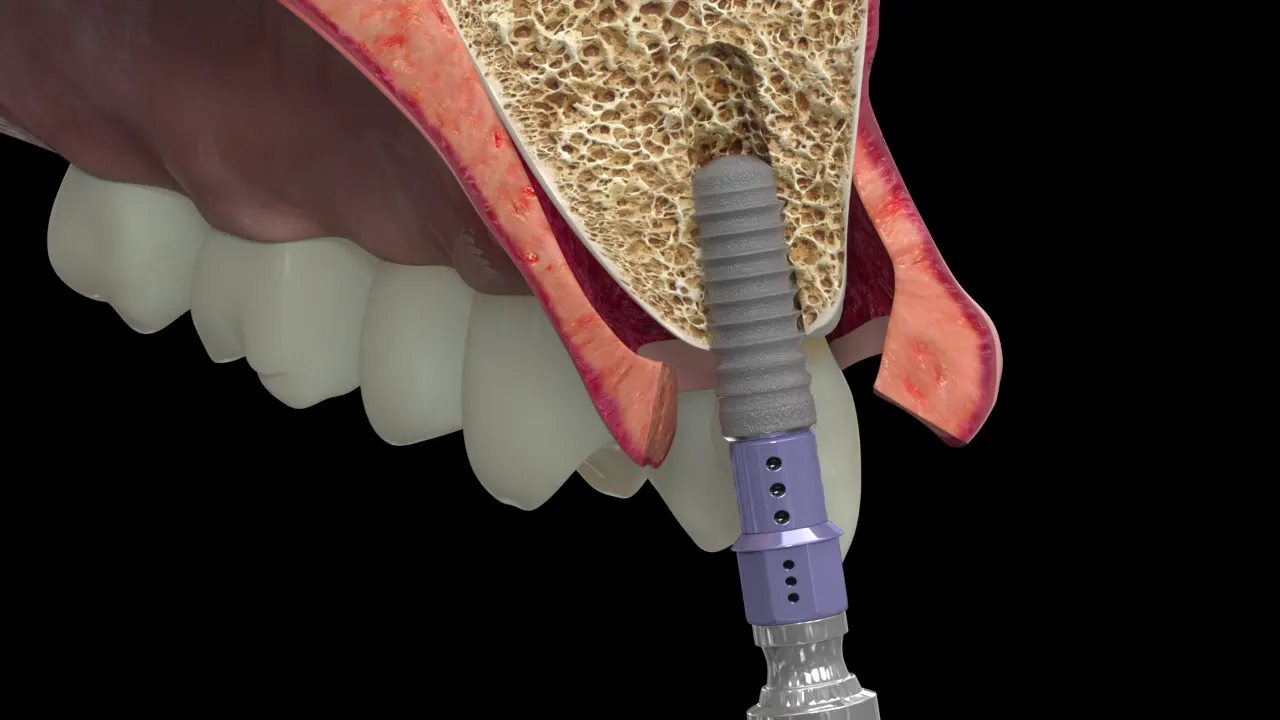
The surgical guide is a splint that steers the drills along the planned axis. Its accuracy has been measured: on average, the placed implant deviates from the plan by a little over a millimetre (1.2 mm at the entry point, 1.4 mm at the tip) and by 3.5° [4]. Guiding every step, rather than only the first drill, tightens these deviations further: against freehand placement, the angular deviation drops from 7.5° to 2.6° and the deviation at the tip from 2.2 mm to 0.9 mm [5]. The comparison table of the three techniques and the principle of placement are on the page Placing an implant and guided surgery.
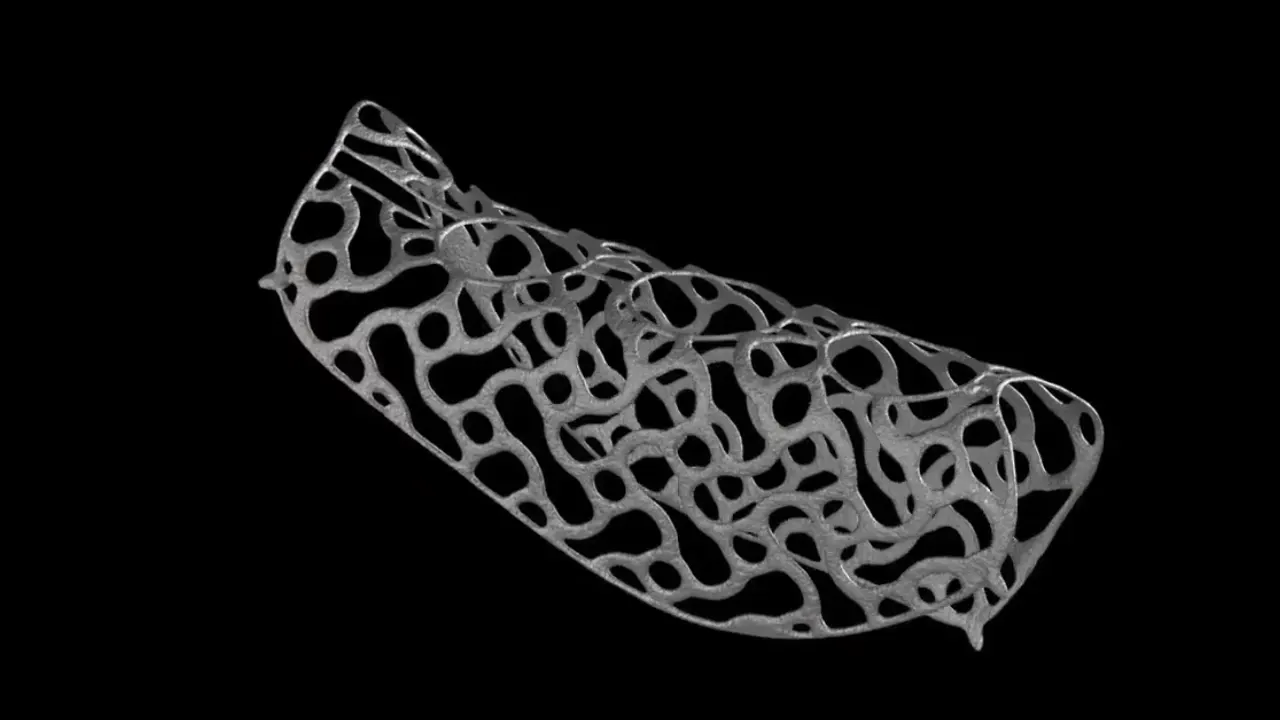
For large reconstructions, the custom titanium mesh is born of the same file: it gives physical form to the bone volume drawn around the implants. A 2025 meta-analysis reports, with these meshes, a mean bone gain of 6.4 mm in width and 5.1 mm in height [7]. Design and manufacture are described in the article on 3D printing, and the treatment steps on the Custom titanium mesh page.
What 3D does not solve
- Dose. Cone beam CT delivers more radiation than a panoramic X-ray, and very unevenly from one machine to another: the equivalent of 2 to 200 panoramic images [1]. The field of view is therefore kept to what is needed, and the scan is repeated only if it could change the decision.
- Artefacts. Metal crowns, old implants or patient movement draw streaks that hide the neighbouring bone [1].
- Measurement accuracy. It reaches 0.2 mm on the best-performing machines, but can be several times poorer depending on the machine and its settings [1]. Figures read on screen are not measurements to the tenth of a millimetre.
- Transfer. Even with a guide, a deviation of about 1 to 1.5 mm persists on average [4]; and the guide must sit perfectly still in the mouth.
- Biology. A perfect plan ensures neither gum healing nor bone formation. With custom meshes, exposure still occurs in close to one case in five [7].
Finally, greater accuracy does not automatically mean better clinical outcomes: when the available systematic reviews are pooled, implant survival is the same after guided surgery and after freehand placement; the benefit of guidance would lie chiefly in reducing surgical risk in difficult cases [8]. 3D planning is a tool for decision-making and safety, not a promise.
In which situations is 3D planning useful?
| Situation | Main contribution of 3D |
|---|---|
| Implant in the back of the lower jaw | Distance to the nerve, ridge width |
| Implant in the back of the upper jaw | Height below the sinus, choice of crestal or lateral sinus lift |
| Thin ridge after an old extraction | Width measurement, decision to graft |
| Large defect in height and width | Design of the volume to rebuild and of a custom mesh |
| Several implants or aesthetic zone | Positions and axes coordinated with the crowns |
In a straightforward situation with bone to spare, planning is still useful but can be lighter. At Dr Hazout’s practice in Levallois-Perret, its level is matched to the difficulty of the case: never maximal as a matter of routine, never cut back when the nerve or sinus are close.
Frequently asked questions
Is cone beam CT dangerous?
Its dose exceeds that of a panoramic X-ray but remains low when the field is confined to the area of interest. The scan is prescribed when it can change the treatment decision, which is the case before a graft or an implant.
Is a new cone beam CT needed after the graft?
Often, yes, before the implants are placed: it checks the bone volume obtained and refines the implant positions. The field is then confined to the grafted area.
Does the software decide instead of the surgeon?
No. It calculates and displays; the clinician chooses the implant position, the grafting technique and the safety margins, in the light of the clinical examination and the state of the gums.
Does a guide or a mesh make surgery risk-free?
No. They narrow the gap between plan and reality, but a deviation of about one millimetre remains, and healing also depends on the gums, smoking and oral hygiene.
Scientific sources (8)
- Jacobs R, Salmon B, Codari M, Hassan B, Bornstein MM. Cone beam computed tomography in implant dentistry: recommendations for clinical use. BMC Oral Health. 2018;18:88. DOI
- Tan WL, Wong TL, Wong MC, Lang NP. A systematic review of post-extractional alveolar hard and soft tissue dimensional changes in humans. Clin Oral Implants Res. 2012;23 Suppl 5:1-21. DOI
- Pjetursson BE, Tan WC, Zwahlen M, Lang NP. A systematic review of the success of sinus floor elevation and survival of implants inserted in combination with sinus floor elevation. Part I: lateral approach. J Clin Periodontol. 2008;35(8 Suppl):216-240. DOI
- Tahmaseb A, Wu V, Wismeijer D, Coucke W, Evans C. The accuracy of static computer-aided implant surgery: A systematic review and meta-analysis. Clin Oral Implants Res. 2018;29 Suppl 16:416-435. PubMed
- Werny JG, Frank K, Fan S, Sagheb K, Al-Nawas B, Narh CT, Schiegnitz E. Freehand vs. computer-aided implant surgery: a systematic review and meta-analysis—part 1: accuracy of planned and placed implant position. Int J Implant Dent. 2025;11:35. DOI
- Schwarz F, Derks J, Monje A, Wang HL. Peri-implantitis. J Periodontol. 2018;89 Suppl 1:S267-S290. DOI
- Ragucci GM, Fernández Augè A, Tresserra Parra A, Elnayef B, Hernández-Alfaro F. Comparison between CAD/CAM titanium mesh vs. conventional titanium mesh in bone regeneration: a systematic review and meta-analysis. Int J Implant Dent. 2025;11:55. DOI
- Tomar S, Chaudhary P, Ganguly A. Comparing the clinical outcomes of guided and freehand dental implant surgery: An umbrella review of systematic reviews and meta-analyses. J Prosthet Dent. 2026;135(5):e53-e59. DOI
Related treatments
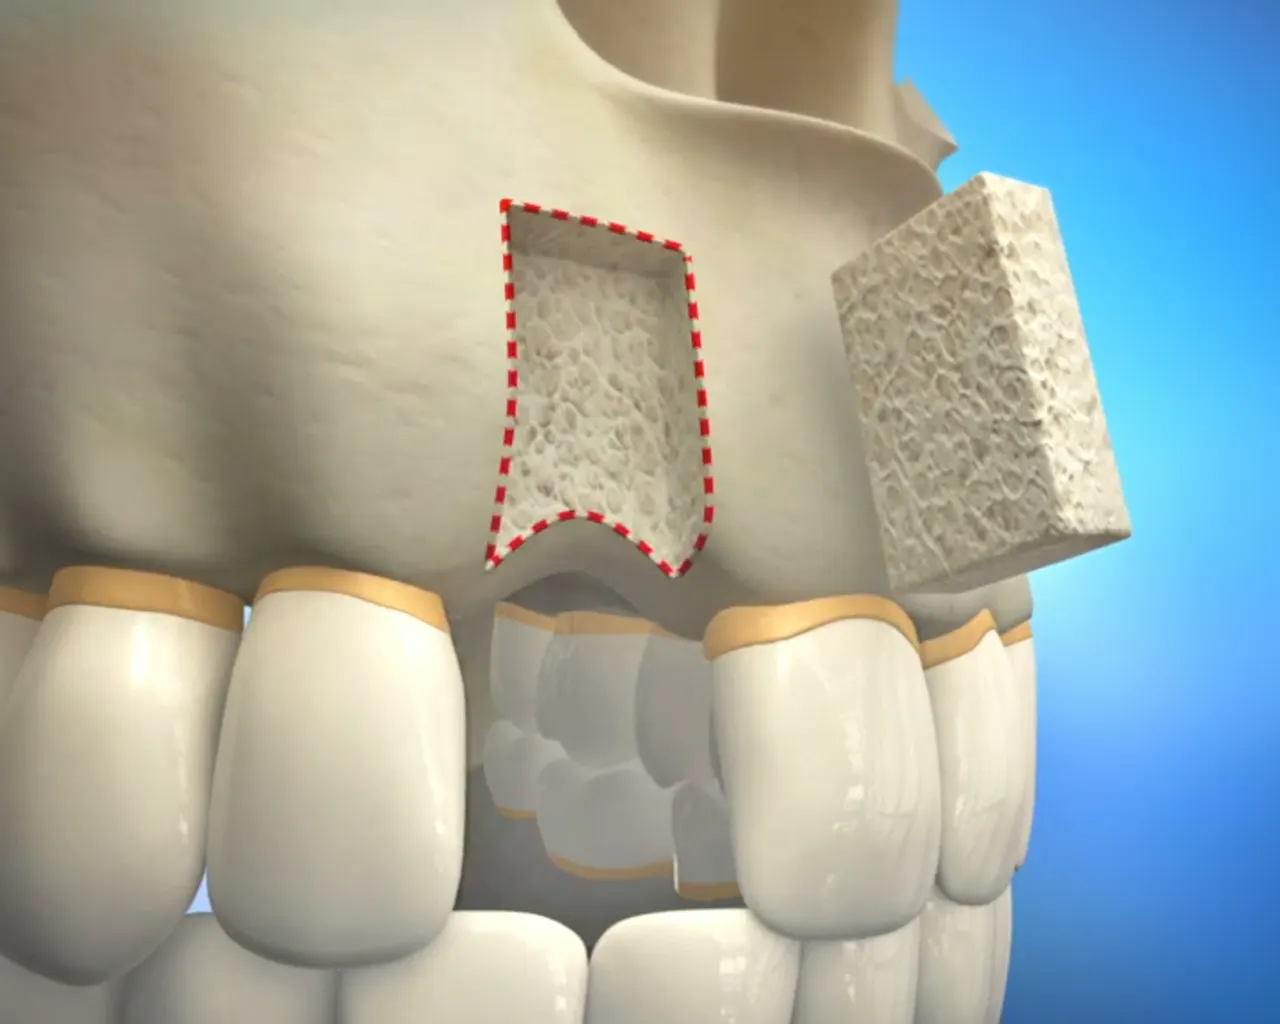
Bone grafting before an implant: when it is needed, and which techniques
An implant only holds in bone, along its whole length. When that bone is missing, it can be rebuilt, and several techniques achieve this, each suited to a particular…
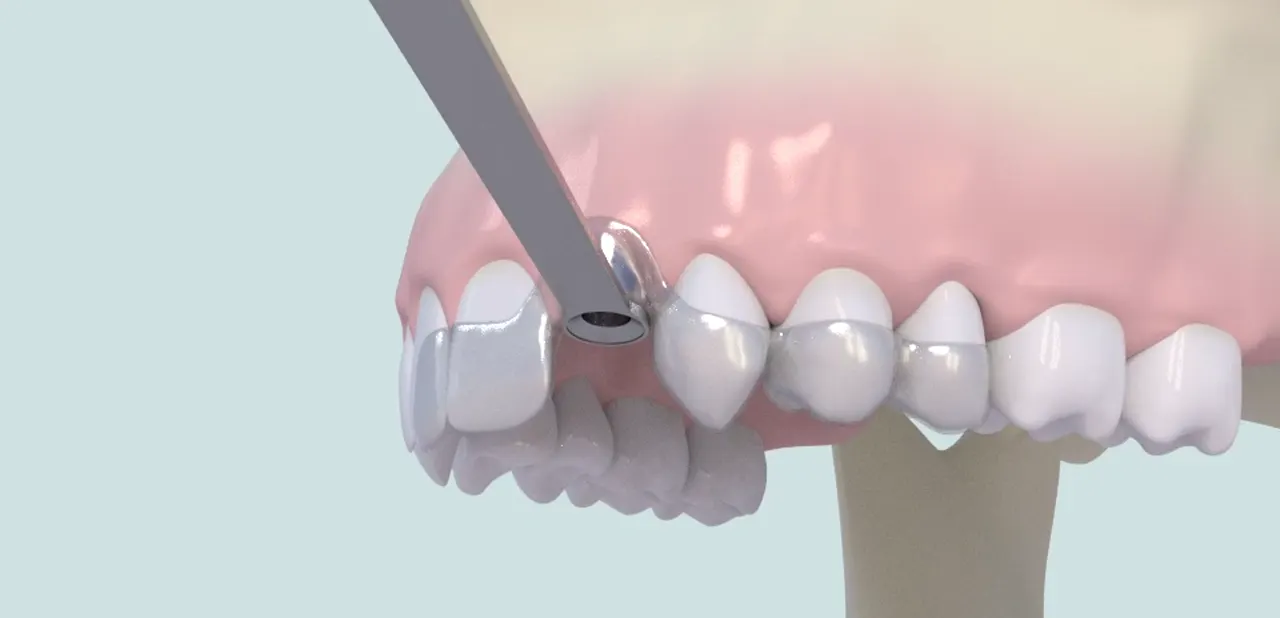
Placing an implant: the steps, and what guided surgery brings
An implant is placed long before the day of surgery. 3D imaging decides where it should go; the surgical guide carries that decision into the mouth. This page follows…
Read next

How is a titanium mesh made by 3D printing?
A custom titanium mesh exists in a single copy: one patient, one bone defect. Between the scan image and the sterile part used in theatre lie a digital workflow and an…
Gum care around implants: preventing peri-implant mucositis and peri-implantitis
An implant cannot decay. But the gum and bone around it can become inflamed and break down, sometimes faster than around a tooth. The two diseases involved, peri-implant…
Patient pathway