









How is a titanium mesh made by 3D printing?
A custom titanium mesh exists in a single copy: one patient, one bone defect. Between the scan image and the sterile part used in theatre lie a digital workflow and an industrial process of great precision. For the patient curious about what will be placed in their jaw, this article describes each link in the chain, its tolerances and its limits, then what this manufacturing changes, and does not change.
Key points
- The mesh is designed on a computer from the cone beam CT images (DICOM files), then converted into a 3D file (STL) for manufacturing.
- It is most often produced by laser powder bed fusion of titanium (SLM or DMLS), one layer after another.
- The material: medical-grade titanium, often the Ti-6Al-4V alloy, sometimes unalloyed titanium.
- After printing: removal of supports, heat and surface treatments, dimensional inspection, cleaning, then sterilisation.
- Laser metal deposition (DED), shown in some industrial videos, is a different process; it is not used to make these meshes.
From image to part: the digital workflow
Everything starts with a cone beam CT, the three-dimensional dental scan. It delivers images in DICOM format, the medical imaging standard: greyscale slices that do not yet contain any “object” that could be manufactured.
A review of 23 studies describes the steps [1]:
- Segmentation: the software isolates bone from the other tissues and derives a 3D model from it.
- Conversion to STL: the model is exported to a surface format that every printing machine can read.
- Design (CAD): the bone volume to rebuild is drawn around the future implants, then the mesh is shaped over that volume: thickness, perforations, screw positions.
- Manufacturing, quality control and sterilisation, most often entrusted to a specialist manufacturer.
The quality of the mesh rests first on the quality of the image. A review of recommendations points out that the accuracy of measurements on cone beam CT varies widely between machines, and that metal artefacts (crowns, old implants) and patient movement alike degrade it [2]. A part of the ridge that is poorly visible on the image will be poorly rendered by the mesh.
The planning logic, which starts from the position of the future crowns, is developed in the article Why plan in 3D before a bone graft and an implant?
Laser powder bed fusion
The international vocabulary standard for additive manufacturing (ISO/ASTM 52900) distinguishes seven families of process. The one for meshes is powder bed fusion: thermal energy selectively fuses regions of a powder bed [3].

The machine spreads a very thin layer of titanium powder, a few tens of micrometres thick. A laser scans the surface and melts the powder only where the mesh must exist. The build plate drops by one layer thickness, a fresh layer is spread, and so on until the whole part is built. All of this takes place under inert gas (argon), because hot titanium reacts with the oxygen in the air.

The acronyms SLM (selective laser melting) and DMLS (direct metal laser sintering) cover variants or trade names within one and the same family. In the review cited above, 7 studies relied on SLM and 9 on DMLS for titanium meshes [1].
Why this process? Because it produces thin, curved, perforated shapes beyond the reach of a bent sheet, and a different part for every patient without dedicated tooling.
What about machining?
Machining takes material away from a block with cutters, as a sculptor would. For titanium meshes it serves mainly for finishing: surface correction, drilling, dimensional adjustments [4]. Five-axis milling is also used to make other custom scaffolds, in PEEK (a polymer) or bone, from pre-formed blocks [1].
The material: which titanium?
Titanium has been, for decades, the reference metal for dental implants and bone surgery plates. In contact with air or tissue, its surface covers itself with a thin, stable oxide layer that makes it very unreactive in the body: this is its biocompatibility. Light, rigid for its weight, it can be produced in very thin sheets; three qualities invaluable in a mesh that must hold a volume without troubling the gum that covers it.
Two families are used. Ti-6Al-4V (titanium alloyed with 6% aluminium and 4% vanadium, known as “grade 5”) is the reference alloy in metal 3D printing. A dedicated standard, ASTM F3001, governs its extra-low-interstitial (ELI) version produced by powder bed fusion; it covers the powder, process parameters, composition, mechanical properties, heat treatment and dimensional inspection [5].
Unalloyed titanium (grades 2 or 4) has its place too. The review of 23 studies records grade IV, Ti-6Al-4V and grade V [1]; a Japanese series of 14 cases used grade 2 titanium in 0.3 mm sheets [6]. Mesh thickness ranges, across studies, from 0.1 to 2 mm, around 0.5 mm on average; the two studies that report perforation size give about 1 mm [1].
After printing: post-processing
A part fresh out of the machine cannot be used as it is. The usual steps:
- Removal of unfused powder and cutting away the supports that carried the part during printing.
- Heat treatment, to relieve the internal stresses born of rapid melting and cooling cycles; hot isostatic pressing (HIP) can reduce residual porosity [4, 5].
- Surface treatment: fusion leaves half-melted powder particles on the surface, which polishing, blasting or chemical or electrochemical etching remove [1, 4].
- Dimensional inspection, cleaning and packaging.
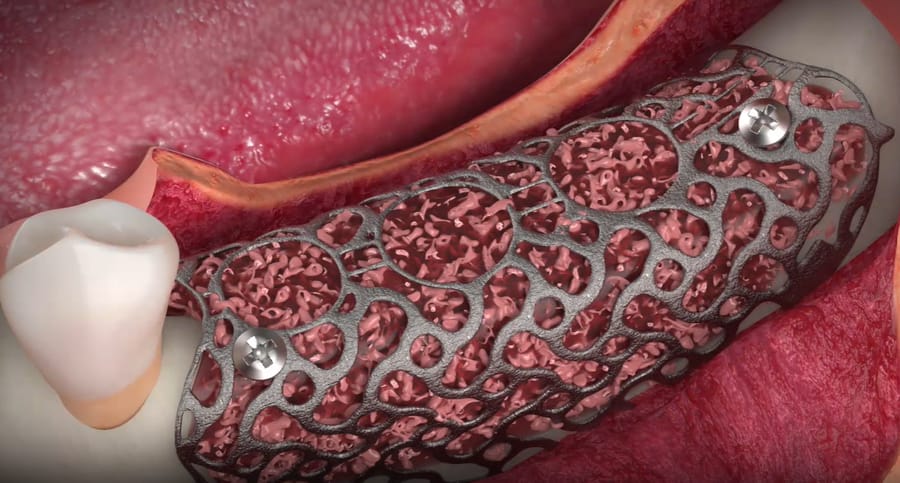
Sterilisation
The mesh arrives either sterile from the manufacturer or is sterilised at the practice under a validated protocol, for example by autoclave (pressurised steam). The review of 23 studies notes that the sterilisation method often goes unreported in publications [1]; the Japanese series describes autoclaving at 121 °C [6]. At Dr Hazout’s practice in Levallois-Perret, sterilisation follows the usual pathway for medical devices, with full traceability.
How accurate is it?
Three levels of accuracy stand apart. First, the image, which depends on the cone beam CT [2]. Next, manufacturing: one manufacturer quotes dimensional deviations of about ± 0.1 mm for features of comparable size [7]. Finally, placement: on models, the mean deviation between planned and achieved contour ran from about 0.8 to 1 mm depending on the mesh design, a “self-positioning” shape reducing it [7]. That study was conducted in vitro: it is no substitute for measurements in patients.
In other words, the machine is rarely the weak link. Image quality, design and the stability of the mesh during surgery weigh more.
Not to be confused with laser metal deposition (DED)
In directed energy deposition (DED), powder or wire is fed into the laser beam and melted the instant it is laid down [3]. It is another family in the ISO/ASTM 52900 standard, devoted mainly to building or repairing large industrial parts. Its resolution is unsuited to a shell a few tenths of a millimetre thick such as a dental mesh.
What does it mean for the patient?
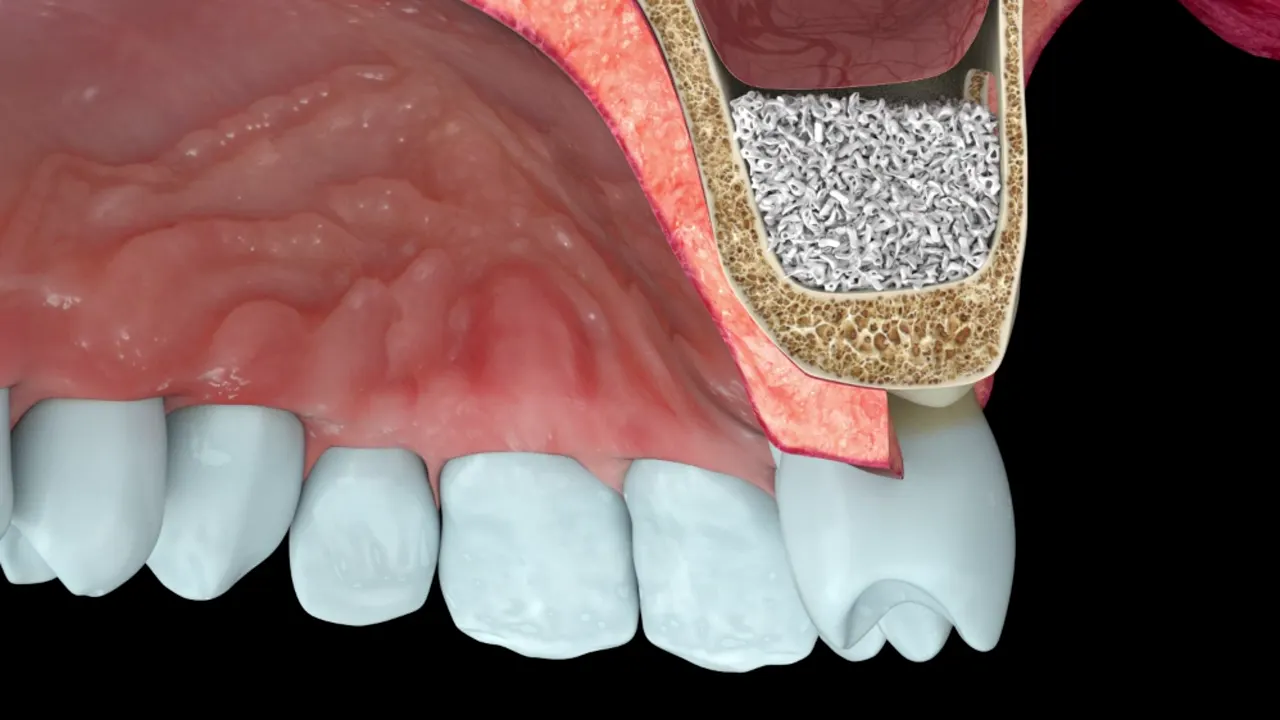
Additive manufacturing changes nothing about the biology: it is still the graft that becomes bone. What it brings is a part fitted before the operation, with no bending at the chairside, hence fewer sharp edges and a shorter operation [8].
Nor does it erase the complication shared by all titanium meshes: exposure, when the gum opens and lets the metal show. In the literature it most often affects 20 to 30% of cases, and early exposure, in the first weeks, comes with more fibrous tissue and less bone formation [8]. The smooth edges and close fit of a printed mesh reduce pressure points on the gum; tension-free closure and stopping smoking remain decisive all the same. The clinical figures, what is done about an exposure and the treatment steps are presented on the Custom titanium mesh page.
Frequently asked questions
Is a printed mesh as strong as a conventional one?
Laser-melted titanium reaches, after suitable heat treatment, mechanical properties laid down by industrial standards. The real point lies elsewhere: a mesh rigid enough to hold the volume, and thin enough to let the gum cover it.
Is my mesh made at the practice?
No. The surgeon approves the design; laser fusion manufacturing falls to a specialist manufacturer with the machines and inspection required.
Why do some videos show a robotic arm depositing metal?
That is laser metal deposition (DED), an industrial process built for large parts. Dental meshes come from laser powder bed fusion, a far finer process.
Can the printed mesh be seen or felt once in place?
Not when all goes to plan: fully covered by the gum, it cannot be felt. If part of the metal becomes visible, that is an exposure, the complication described above.
Scientific sources (8)
- Elrefaei SA, Parma-Benfenati L, Dabaja R, Nava P, Wang HL, Saleh MHA. Customized 3D-Printed Scaffolds for Alveolar Ridge Augmentation: A Scoping Review of Workflows, Technology, and Materials. Medicina (Kaunas). 2025;61(7):1269. DOI
- Jacobs R, Salmon B, Codari M, Hassan B, Bornstein MM. Cone beam computed tomography in implant dentistry: recommendations for clinical use. BMC Oral Health. 2018;18:88. DOI
- ISO/ASTM 52900:2021. Additive manufacturing — General principles — Fundamentals and vocabulary. Genève : ISO ; 2021. cdn.standards.iteh.ai
- Zhang H, Tang X, Guo W, et al. A short review of the post-processing of titanium alloys processed by selective laser melting. Int J Adv Manuf Technol. 2025;138(9):4121-4136. DOI
- ASTM F3001-14(2021). Standard Specification for Additive Manufacturing Titanium-6 Aluminum-4 Vanadium ELI (Extra Low Interstitial) with Powder Bed Fusion. West Conshohocken (PA) : ASTM International ; 2021. store.astm.org
- Takahashi A, Inoue K, Imagawa-Fujimura N, et al. Clinical Study of 14 Cases of Bone Augmentation with Selective Laser Melting Titanium Mesh Plates. Materials (Basel). 2023;16(21):6842. DOI
- Zhang J, Chen Y, Tao X, Zhang K, Xu C, Yu D. In vitro evaluation of a self-positioning individualized titanium mesh for improved accuracy in guided bone regeneration. Front Bioeng Biotechnol. 2026;14:1718616. DOI
- Xie Y, Li S, Zhang T, Wang C, Cai X. Titanium mesh for bone augmentation in oral implantology: current application and progress. Int J Oral Sci. 2020;12:37. DOI
Related treatments
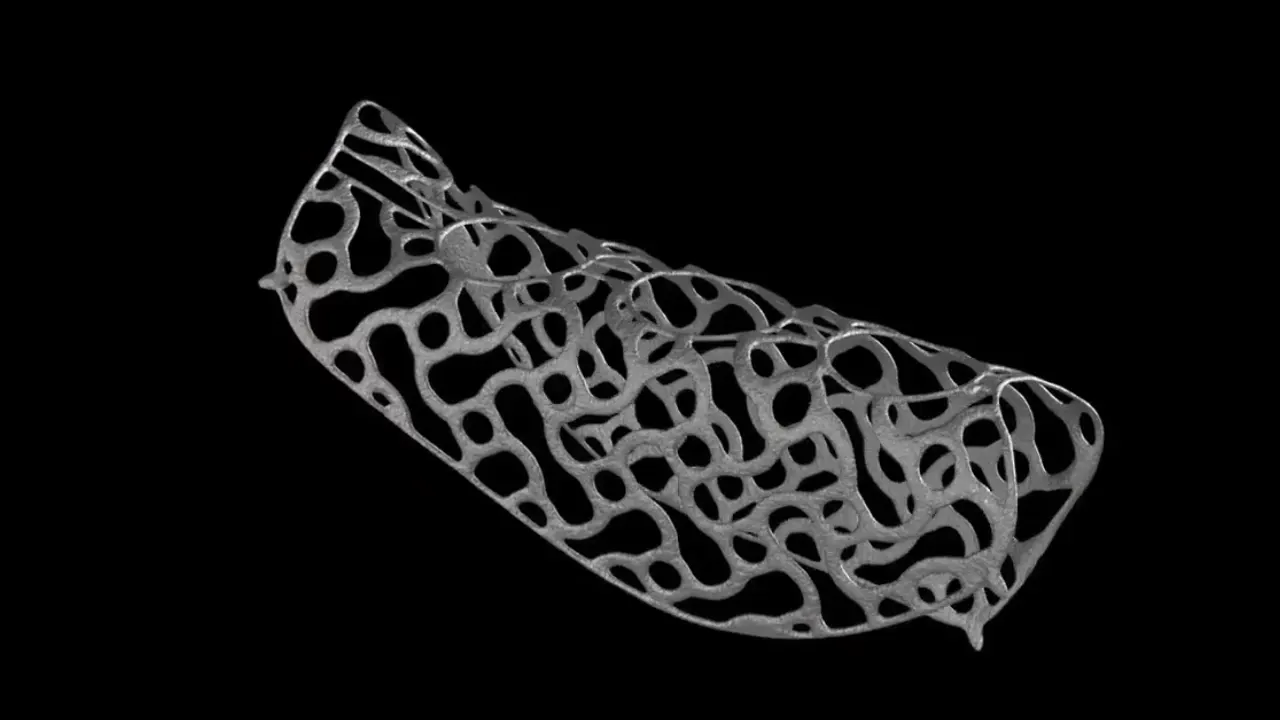
Custom titanium mesh: what it is for, and the principle of treatment
When bone is missing in height as well as width, the graft material needs to be held in shape while it heals. A custom titanium mesh does this job, like formwork: drawn…
Bone grafting before an implant: when it is needed, and which techniques
An implant only holds in bone, along its whole length. When that bone is missing, it can be rebuilt, and several techniques achieve this, each suited to a particular…
Read next
Why plan in 3D before a bone graft and an implant?
A conventional X-ray shows bone from the front, like a cast shadow, and says nothing about its width. Yet width is often what decides: will the implant hold on its own,…
Gum care around implants: preventing peri-implant mucositis and peri-implantitis
An implant cannot decay. But the gum and bone around it can become inflamed and break down, sometimes faster than around a tooth. The two diseases involved, peri-implant…
Patient pathway